
Daytrana
METHYLPHENIDATES · TRANSDERMAL SYSTEM (PATCH)
Key facts
- Drug class
- CNS Stimulant · Methylphenidates
- Active ingredient
- methylphenidate
- FDA-approved ages
- 6 to 17 years
- Form and strengths
- Transdermal system; 10, 15, 20, 30 mg per 9 hours (1.1, 1.6, 2.2, 3.3 mg/hr)
- Usual dose and maximum (label)
- Start with the 10 mg/9 h patch and increase weekly as needed (patch sizes up to 30 mg/9 h).
- Duration
- Patch worn up to 9 hours; benefit from 2 through 12 hours after application in studies.
- DEA schedule
- Schedule II controlled substance (CII)
- Generic
- Generic patches available (see Generic manufacturers)
- Label date
- Prescribing Information revised 09/2025 (DailyMed)
Label last checked: Oct 2026 — Prescribing Information revised 09/2025 (DailyMed) · Last medical review: November 12, 2026
Educational information only, not medical advice. Do not start, stop or change a medication without your prescriber. Medical disclaimer
What it is
Daytrana is a patch that delivers methylphenidate through the skin. A parent or caregiver usually applies it to the hip in the morning and removes it after up to 9 hours. Because the patch can be taken off early, the length of the effect can be adjusted. It helps with focus, staying on task, and reducing hyperactivity and impulsivity without swallowing a pill.
Methylphenidate transdermal system: 10, 15, 20, and 30 mg nominal delivery over 9 hours (1.1, 1.6, 2.2, 3.3 mg/hr; 12.5–37.5 cm²; 27.5–82.5 mg content), applied to the hip. On single dosing, d-methylphenidate is first detectable after ~2 h on average; peak plasma levels ~10 h after a single application and ~8 h with repeated use; d-methylphenidate half-life after removal ~4–5 h. l-Methylphenidate exposure is 46% (children) and 40% (adolescents) of d-methylphenidate exposure. Indicated for ADHD in pediatric patients 6–17 years (label revised 09/2025; Noven). Schedule II. Orange Book AB.
When considering this for a patient
The patch suits children and adolescents who cannot swallow oral medication or who benefit from adjustable duration (remove early if late-day effects are a problem). Skin reactions are common: most patients have some erythema, and contact sensitization and chemical leukoderma (persistent loss of skin pigmentation) have been reported. Avoid external heat over the patch, which significantly increases absorption; absorption is also increased on inflamed skin.
Patients converting from oral methylphenidate should follow the patch titration schedule starting at 10 mg. Because sources differ on whether brand Daytrana is still marketed (see Availability), confirm with the pharmacy whether the brand or a generic methylphenidate transdermal system can be dispensed. Schedule II with a boxed warning for abuse, misuse, and addiction; used patches should be folded in half (sticky sides together) and flushed or disposed of as directed in the labeling.
Patient profile and niche
Daytrana (or generic methylphenidate patches) may be particularly useful in the following situations:
- Children or adolescents who have difficulty swallowing pills or capsules.
- Need for flexible duration: the patch can be removed earlier if late-day side effects occur.
- Desire to avoid a midday dose or school administration.
- Patients who respond to methylphenidate but prefer or require a non-oral route.
When it is active
After the patch is applied, there is about a 2-hour delay before medicine appears in the blood. Levels rise while the patch is worn and peak about 8–10 hours after application. The patch is removed at 9 hours, and effects continue for a few more hours. In studies, benefit was significant from 2 hours through 12 hours after application.
Use the interactive tool below: enter the time the patch is applied. The curve assumes the full 9-hour wear time and is a schematic based on labeling data, not a prediction for any individual.
Enter the times that match your (or your child’s) typical day. The curve shows relative plasma level over clock time.
The curve shows relative plasma concentration (not guaranteed clinical effect). “TAKE” marks the time the patch is applied.
Removing the patch earlier shortens the effect. Average half-life after removal is about 4–5 hours.
Everyone is different. This is a general guide based on labeling data, not a prediction for any one person.
How it works
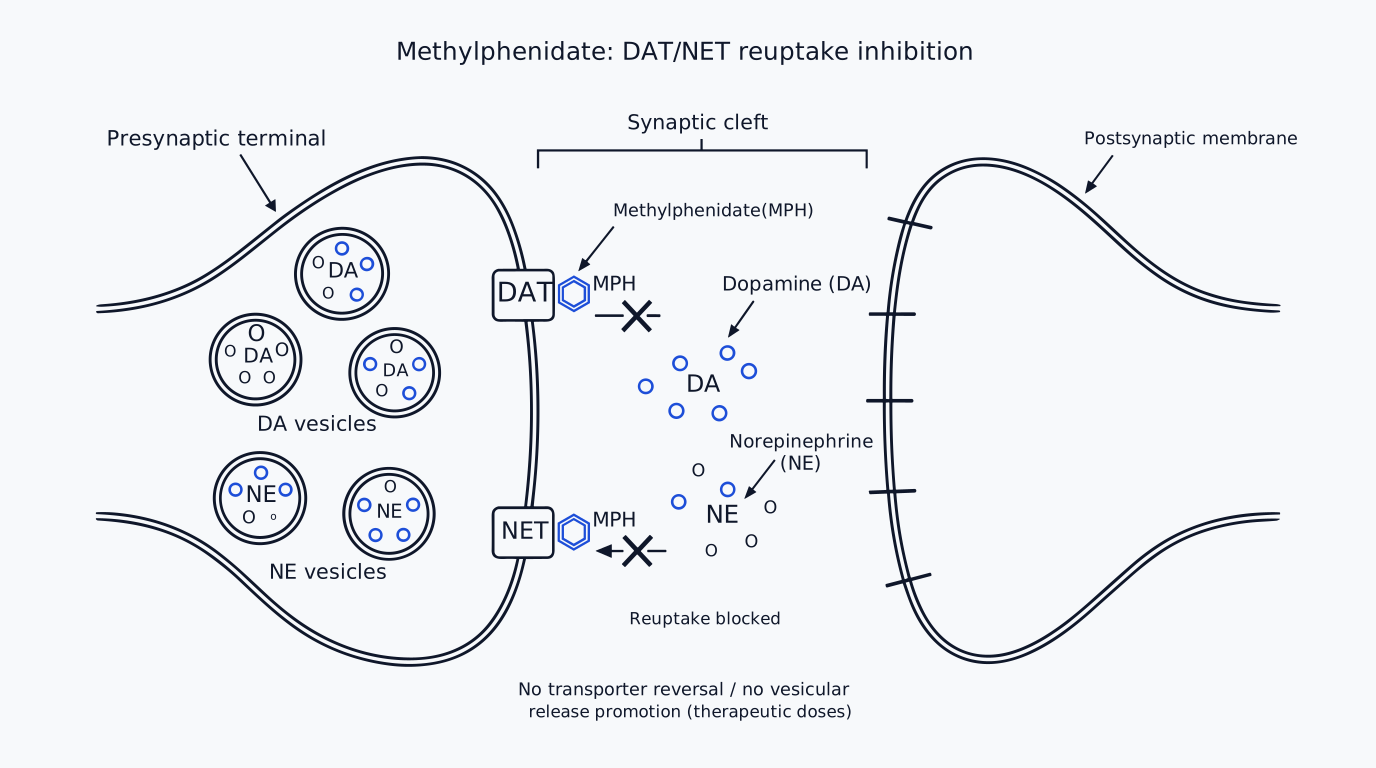
Methylphenidate blocks the transporters that normally remove dopamine and norepinephrine from the synapse, increasing their availability in brain areas involved in attention and impulse control. The patch delivers the medicine steadily through the skin instead of through the stomach.
Increases synaptic dopamine
Increases synaptic norepinephrine
About a 2-hour delay
Remove early to shorten effect
Per labeling, the mode of therapeutic action in ADHD is not known. Methylphenidate blocks the reuptake of norepinephrine and dopamine into the presynaptic neuron and increases the release of these monoamines into the extraneuronal space. Methylphenidate is racemic; the d-enantiomer is more active. With transdermal delivery, l-methylphenidate exposure is 40–46% of d-methylphenidate exposure, higher than after oral dosing.
Formulations and duration
Patch applied to the hip once daily, alternating hips, about 2 hours before the effect is needed, and removed after 9 hours (or earlier). Sources differ on whether brand Daytrana is still marketed (see Availability); ASHP lists generic methylphenidate transdermal systems as available.
| STRENGTHS | 10, 15, 20, 30 mg per 9 hours (1.1, 1.6, 2.2, 3.3 mg/hr) |
|---|---|
| APPROVED AGES | 6 to 17 years |
| ADMINISTRATION | Apply to hip ~2 h before effect needed; remove after 9 h; alternate hips; do not cut patches (apply only intact patches) |
| AVAILABILITY | Sources differ on brand status (checked Oct 29, 2026); Padagis and Mylan (Viatris) generic patches listed as available (ASHP) |
Appearance
Daytrana patches are thin, rectangular transdermal systems that increase in size with strength (FDA label):
- 10 mg/9 h — 12.5 cm²
- 15 mg/9 h — 18.75 cm²
- 20 mg/9 h — 25 cm²
- 30 mg/9 h — 37.5 cm²
Cartons contain 30 individually pouched patches. Generic patches may differ in appearance; check the pouch and carton label for strength and manufacturer.
Official package photos and pill identifiers:
Generic manufacturers
Generic methylphenidate transdermal systems rated AB to Daytrana are available, including an authorized generic distributed by Padagis.
| Manufacturer | Notes |
|---|---|
| Noven (distributed by Padagis) | Authorized generic; NDC 0574-2410/-2415/-2420/-2430; FDA lists all four as Available |
| Mylan (Viatris) | AB-rated ANDA; NDC 0378-8260 to -8263; ASHP lists as available |
Per the FDA Orange Book data files (October 2026), Daytrana (Noven) is still listed as RX/AB, and Mylan holds the AB-rated ANDA. ASHP identifies Padagis as the distributor of the Daytrana authorized generic.
Common side effects
Most side effects are mild. Common ones include decreased appetite, trouble sleeping, nausea, and weight loss. Most children also have some redness where the patch was worn. With long-term use, the label advises periodic blood counts.
| EFFECT | FREQUENCY | NOTES |
|---|---|---|
| Skin redness at the patch site | Very common | Usually mild; alternate hips |
| Decreased appetite / weight loss | Common | Weight and growth are checked |
| Trouble sleeping | Common | Remove the patch earlier if needed |
| Nausea or vomiting | Common | Tell your clinician if it persists |
| Tics | Common (ages 6–12) | Report new movements or sounds |
| Mood changes (affect lability) | Common | Report mood changes |
Most common (≥5% and twice placebo): ages 6–12 — appetite decreased, insomnia, nausea, vomiting, weight decreased, tic, affect lability, and anorexia; ages 13–17 — appetite decreased, nausea, insomnia, weight decreased, dizziness, abdominal pain, and anorexia. Most subjects had application-site erythema. Additional patch-specific warnings: contact sensitization, chemical leukoderma, and increased absorption with external heat. Boxed warning for abuse, misuse, and addiction; assess risk before prescribing and reassess during treatment. Warnings include risks to patients with serious cardiac disease, increased blood pressure and heart rate, psychiatric adverse reactions (screen for mania risk), priapism, peripheral vasculopathy including Raynaud’s phenomenon, long-term suppression of growth in pediatric patients, acute angle-closure glaucoma, increased intraocular pressure, and motor and verbal tics/worsening of Tourette’s syndrome. Contraindicated with MAOIs or within 14 days of stopping an MAOI. Monitor blood pressure, heart rate, height, and weight at baseline and periodically.
Hematologic monitoring (label 5.12): periodic CBC with differential and platelet counts are advised during prolonged therapy.
Interactions (label 7.3): methylphenidate may inhibit the metabolism of coumarin anticoagulants, anticonvulsants (e.g., phenobarbital, phenytoin, primidone), some tricyclic antidepressants (e.g., imipramine, clomipramine, desipramine) and SSRIs; their doses may need to be lowered, and drug levels (coagulation times for coumarins) monitored when methylphenidate is started or stopped. This interaction section is in the Daytrana label; current oral methylphenidate labels checked do not carry it.
Abuse and used patches: transdermal delivery has not been shown to lower abuse potential. The label carries the same boxed warning for abuse, misuse and addiction as oral methylphenidate, and states that residual methylphenidate remains in used systems (2.5); fold used patches adhesive sides together and discard as directed.
MRI: Daytrana labeling has no MRI statement. Ask patients to tell imaging staff about any transdermal system and follow the local MRI safety policy.
Misuse context (outside the label): in SAMHSA’s 2023 National Survey on Drug Use and Health, 1.4% of people aged 12 or older (about 3.9 million) misused a prescription stimulant in the past year; the rate was highest in adults aged 18 to 25 (3.1%). The survey counts all prescription stimulants (amphetamine and methylphenidate products, weight-loss stimulants and others), not this medicine alone (SAMHSA, 2023 NSDUH).
Contact sensitization (label 5.10): in an open-label study of 305 children using a 9-hour wear time, one child (0.3%) was confirmed by patch testing to be sensitized to methylphenidate (allergic contact dermatitis) and stopped treatment. Redness alone is common and is not by itself a sign of sensitization; suspect it when redness comes with a stronger local reaction (swelling, bumps or blisters) that does not clearly improve within 48 hours or spreads beyond the patch site, and stop Daytrana if it is suspected. Patients sensitized by the patch may develop systemic reactions if they later take methylphenidate by another route, such as by mouth.
Dosing considerations
Everyone starts with the smallest patch (10 mg), even if switching from another methylphenidate product, and the patch size is increased weekly if needed. A parent or caregiver usually applies and removes the patch and keeps track of the times.
Recommended starting dose for patients new to methylphenidate or converting from other methylphenidate formulations: 10 mg/9 h. Titrate weekly as needed:
Baseline ECG: The label’s pre-treatment cardiac assessment is a careful history, including family history of sudden death or ventricular arrhythmia, and a physical exam; it does not call for a routine ECG. NICE NG87 states that an ECG is not needed before starting stimulants unless a feature listed in 1.7.5 is present (e.g., congenital heart disease or previous cardiac surgery, sudden cardiac death in a first-degree relative under 40, exertional breathlessness or syncope, paroxysmal palpitations, cardiac-sounding chest pain, signs of heart failure, a murmur, or adult hypertension) or a co-existing condition is treated with a medicine that adds cardiac risk; those features call for a cardiology opinion (1.7.4–1.7.5). The AAP 2019 guideline asks for a history of cardiac symptoms and a family history of sudden death, WPW, hypertrophic cardiomyopathy and long QT, with further evaluation if any risk factor is present. A Canadian joint position statement (Warren 2009) and the European ADHD Guidelines Group (Graham 2011) do not recommend routine ECG screening; Graham notes that the American Heart Association’s 2008 statement first proposed an ECG as standard and then left it to clinician discretion. In one US screening series, 8.1% of ECGs were abnormal but heart disease was found in 0.3% (Mahle 2009).
| Week | Patch size | Nominal dose (mg/9 h) | Delivery rate |
|---|---|---|---|
| Week 1 | 12.5 cm² | 10 mg | 1.1 mg/hr |
| Week 2 | 18.75 cm² | 15 mg | 1.6 mg/hr |
| Week 3 | 25 cm² | 20 mg | 2.2 mg/hr |
| Week 4 | 37.5 cm² | 30 mg | 3.3 mg/hr |
Apply to the hip 2 hours before an effect is needed and remove 9 hours after application; may remove earlier for a shorter duration or if late-day adverse reactions occur. Alternate hips daily. Avoid exposing the application site to external heat sources.
Do not cut transdermal systems; apply only intact systems, and do not use one if the pouch seal is broken or the system looks damaged (label 2.3).
Planned breaks from medicine (weekends and holidays)
Some families leave out doses on weekends or during school holidays. This is sometimes called a medication holiday or treatment break. Plan any break with the prescriber instead of stopping on your own.
Breaks are usually considered for poor appetite, slow weight gain, trouble sleeping, slowed growth, or to see whether the medicine is still needed. The label says children who are not growing or gaining weight as expected may need to have treatment paused.
In studies, breaks helped appetite, sleep and weight gain. It is less clear that they help a child end up taller: one older study saw a height benefit only after two summers off, and a newer trial found that weekend breaks did not speed up height growth. ADHD symptoms can return on days off, so breaks tend to suit lower-pressure times. If you try one, watch how things go at home and with friends, and restart if problems come back.
Growth warning (label 5.8): monitor height and weight during treatment of pediatric patients; those not growing or gaining height or weight as expected may need treatment interrupted. NICE NG87 lists a planned break among options when weight loss is a concern (1.8.6), suggests considering a break over school holidays to allow catch-up growth when height is significantly affected (1.8.7), and advises periodic trial periods off medication or at a lower dose when the balance of benefit and harm suggests it (1.10.3). The AACAP 2007 practice parameter suggests considering a holiday when height or weight crosses two percentile lines, provided off-medication weekends or summers are not markedly impairing, and regards low-stress periods such as vacations (not the start of a school year) as a good time for a discontinuation trial.
Evidence (see Clinical evidence: Growth, below): in a 4-week RCT of twice-daily IR methylphenidate, weekend placebo reduced insomnia without a significant rise in weekend parent or Monday teacher ratings (Martins 2004, n=40). In children with stimulant-associated weight loss, school-days-only dosing increased weight velocity but not height velocity, and most families in that arm resumed after-school dosing because of symptoms (Waxmonsky 2020). Two summers off methylphenidate were followed by a height benefit; one summer was not (Klein 1988). A review of 22 studies found 25–70% of families use breaks (Ibrahim 2015). In the observational MTA follow-up, consistent long-term use was associated with about 2.4 cm lower adult height (Swanson 2017). Data in adults are sparse.
Pregnancy and breastfeeding
Tell your clinician if you are pregnant, plan to become pregnant, or are breastfeeding. There is not enough information to know whether methylphenidate raises the risk of birth defects, miscarriage, or other problems in pregnancy. Stimulant medicines can narrow blood vessels, which may reduce blood flow to the placenta.
Outside the label: in one very large study of US and Nordic pregnancy records, methylphenidate taken in the first 3 months of pregnancy was linked to a possible small increase in heart defects, while the overall rate of birth defects was not significantly higher. Absolute risks stayed low. See Clinical evidence from published studies (Pregnancy) below.
Small amounts of methylphenidate pass into breast milk. No harm to breastfed babies and no effect on milk supply have been reported, but long-term effects are not known. If you breastfeed while taking Daytrana, decide together with your clinician, and watch the baby for agitation, poor sleep, poor feeding, or slow weight gain.
A national pregnancy registry collects information about ADHD medicines used during pregnancy. You or your clinician can enroll by calling 1-866-961-2388.
Pregnancy (label 8.1): published studies and postmarketing reports on methylphenidate in pregnancy are insufficient to identify a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. The label adds that there are risks to the fetus from CNS stimulant use. Clinical considerations: CNS stimulants can cause vasoconstriction and thereby decrease placental perfusion; no fetal or neonatal adverse reactions have been reported with therapeutic doses of methylphenidate, but premature delivery and low birth weight have been reported in infants of amphetamine-dependent mothers. Animal data: no reproduction studies with transdermal methylphenidate; oral methylphenidate caused no morphological effects in rats and rabbits in the main studies, spina bifida in rabbits at 200 mg/kg/day in an earlier study, and reduced offspring growth and survival in rats at maternally toxic doses. Registry: National Pregnancy Registry for ADHD Medications (as named in the label), 1-866-961-2388.
Lactation (label 8.2): limited published data (milk sampling from five mothers) show methylphenidate in human milk at infant doses of 0.16% to 0.7% of the maternal weight-adjusted dose and a milk/plasma ratio of 1.1 to 2.7, with no reported adverse effects in breastfed infants and no effects on milk production; long-term neurodevelopmental effects are unknown. Weigh the benefits of breastfeeding against the mother’s clinical need for Daytrana and any potential effects on the infant. Monitor breastfed infants for agitation, insomnia, anorexia, and reduced weight gain.
Outside the label (InPreSS; Huybrechts 2018, JAMA Psychiatry; PubMed 29238795): first-trimester methylphenidate in a US Medicaid cohort of 1,813,894 pregnancies, adjusted RR for any congenital malformation 1.11 (95% CI 0.91–1.35), not significant; cardiac malformations 1.28 (0.94–1.74) in the US cohort and 1.28 (1.00–1.64) when pooled with a Nordic cohort of 2,560,069 pregnancies. Amphetamines showed no increase (any malformation 1.05, cardiac 0.96). These are observational findings; they do not change the label’s section 8.1 statement.
Outside the label: LactMed (NCBI Bookshelf, “Methylphenidate,” revised Aug 2025; NBK501310) says milk levels at prescribed doses appear very low and were not detectable in infant blood, that needing methylphenidate is not a reason to stop breastfeeding, and that large doses might reduce milk production, especially before lactation is well established. This is LactMed’s summary of published data, not FDA label content.
Availability and shortages
SOURCES DIFFER ON BRAND STATUS Sources disagree about whether brand Daytrana is still sold. As of Oct 29, 2026: ASHP reports that Noven discontinued brand Daytrana in early 2026; the FDA Orange Book still lists all four Daytrana patch sizes as active prescription products; DailyMed lists all four Daytrana packages as marketed, with no end date; and the FDA Drug Shortages database lists Noven’s patches distributed by Padagis (the authorized generic) as available. ASHP lists generic patches from Padagis and Mylan (Viatris) as available. We list what each source reports and do not decide between them.
Before a refill, ask your pharmacy which versions it can currently order, and talk with your prescriber before switching to a different product.
Sources rechecked Oct 29, 2026. They disagree, and none is treated here as definitive. Orange Book (web search rechecked Oct 29, 2026; data file dated Oct 9, 2026, unchanged): Daytrana (Noven, NDA 021514) 10, 15, 20 and 30 mg/9 h listed RX with TE code AB; Mylan Technologies (Viatris) ANDA 206497 listed RX/AB. FDA Drug Shortages (Methylphenidate Film, Extended Release, checked Oct 29, 2026): Currently in Shortage, first posted Feb 28, 2025; the only listing is Noven’s product distributed by Padagis (NDC 0574-2410, -2415, -2420, -2430), all four strengths Available (reverified Oct 16, 2026). Brand Daytrana’s own NDCs (68968-5552 to -5555) are not listed. ASHP (Methylphenidate Transdermal System, updated Mar 19, 2026; not on ASHP’s current-shortages list as of Oct 29, 2026): Noven discontinued Daytrana patches in early 2026; Mylan (Viatris) and Padagis (authorized-generic distributor) patches available. DailyMed (checked Oct 29, 2026): the Daytrana label (Noven, SPL version 29) lists all four NDCs as marketed since Apr 6, 2006 with no end date; the Padagis label lists its four NDCs as marketed with no end date; the Mylan label lists marketing end dates of Jan 31, 2027 (30 mg) and Apr 30, 2027 (10, 15 and 20 mg). These sources are maintained separately and updated on different schedules. Confirm what the dispensing pharmacy can obtain before prescribing or switching.
How Daytrana compares to other methylphenidates
Daytrana is one of several methylphenidate-family options. Effect windows below come from each product’s FDA labeling (clinical study time points), not head-to-head comparisons; individual duration varies.
| Medication | Studied effect window / dosing (label) | Release design | Key practical notes |
|---|---|---|---|
| Daytrana (transdermal patch) | Significant 2–12 h after application; worn up to 9 h | Transdermal delivery | Brand status: sources differ; generic patches listed as available (ASHP). |
| Quillivant XR (oral suspension) | Significant from 0.75 h through 12 h | ~20% immediate + ~80% extended release | Liquid 25 mg/5 mL after reconstitution; shake before each dose. |
| Cotempla XR-ODT (disintegrating tablet) | Significant 1–12 h after dosing | ~25% immediate + ~75% extended release | Dissolves in mouth; ages 6–17. Authorized generic exists. |
| Concerta (OROS tablet) | Effects maintained through 12 h after dosing | Osmotic tablet: drug overcoat + gradual osmotic delivery | Swallow whole. AB-rated generics. ER tablets on FDA shortage list (brand reported available). |
| Focalin XR (dexmethylphenidate beads) | Significant from 0.5 h through 12 h (pediatric studies) | 50% immediate + 50% delayed-release beads, d-isomer | Sprinkle allowed. AB generics; ER capsules on ASHP shortage list. |
| Jornay PM (delayed + extended release) | Evening dose; improvement 9 a.m.–7 p.m. next day | Delayed-release coat, then extended release | Taken 6:30–9:30 p.m. Not interchangeable mg-for-mg. |
Other methylphenidate-family pages: Concerta, Ritalin, Methylin, Ritalin LA, Metadate CD, Aptensio XR, Adhansia XR, Focalin, Focalin XR, Azstarys, Jornay PM, Cotempla XR-ODT, QuilliChew ER, Quillivant XR, Relexxii, Methylphenidate ER tablets (10/20 mg), Methylphenidate chewable tablets.
Clinical evidence from published studies
These findings come from published research, not from the FDA label. The FDA label is the official source for approved uses, doses and warnings. Results from studies may not apply to you. Uses marked off-label are not FDA-approved. Talk with your prescriber before making any change.
Items summarize peer-reviewed publications, checked against the PubMed abstract (or full text where stated); figures are reproduced only where the source states them. The FDA label governs approved indications and dosing. Off-label items are not FDA-approved uses. Industry funding or sponsor affiliation is noted where the PubMed record shows it; absence of a note does not mean no industry involvement.
Studies of this medicine (2 studies)
-
Daytrana (methylphenidate patch)
In a classroom study of 80 children, the methylphenidate patch worn for 9 hours improved attention and behavior from the first measurement after application through 12 hours.
Dose optimisation (10/16/20/27 mg patches, 9-h wear), then 80 randomised to 1-week MTS/placebo crossover. Significant improvement from first post-dose point through 12 h on all efficacy measures.
McGough JJ, Wigal SB, Abikoff H, et al. (2006). A randomized, double-blind, placebo-controlled, laboratory classroom assessment of methylphenidate transdermal system in children with ADHD. J Atten Disord 9(3):476-85. DOI · PubMed 16481664
-
Daytrana vs Concerta
In children and teens, methylphenidate levels built up over repeated days of patch use more than with Concerta.
Open-label PK (33 children, 31 adolescents). d-MPH accumulation with MTS: 34%/57% (children/adolescents) after 7 days, 76%/94% after 28 days; OROS MPH 16%/19% after 7 days.
Pierce D, Katic A, Buckwalter M, et al. (2010). Single- and multiple-dose pharmacokinetics of methylphenidate administered as methylphenidate transdermal system or osmotic-release oral system methylphenidate to children and adolescents with attention deficit hyperactivity disorder. J Clin Psychopharmacol 30(5):554-64. DOI · PubMed 20814325
How ADHD medicines compare (6 studies)
-
ADHD medicines (class)
A large analysis of 133 short-term trials found that every ADHD medicine studied worked better than placebo on clinician ratings in children and teens. Amphetamines had the largest average effect, and methylphenidate was the only medicine also shown to beat placebo on teacher ratings. Amphetamines and guanfacine led to more stopping for side effects than placebo in children. Weighing benefit and side effects, the authors favored methylphenidate first in children and amphetamines first in adults. There was too little data to judge effects beyond about 12 weeks.
Network meta-analysis of 133 double-blind RCTs (efficacy near 12 wk: 10,068 children/adolescents; 8,131 adults). Children, clinician-rated SMD vs placebo: amphetamines −1.02 (95% CI −1.19 to −0.85), methylphenidate −0.78 (−0.93 to −0.62), atomoxetine −0.56 (−0.66 to −0.45). Teacher-rated: only methylphenidate (−0.82, −1.16 to −0.48) and modafinil separated from placebo. Adults, clinician-rated: amphetamines −0.79 (−0.99 to −0.58), methylphenidate −0.49 (−0.64 to −0.35), atomoxetine −0.45 (−0.58 to −0.32). Discontinuation for adverse events vs placebo: amphetamines OR 2.30 (1.36–3.89) in children and 3.26 (1.54–6.92) in adults; guanfacine 2.64 (1.20–5.81) in children; atomoxetine 2.33 (1.28–4.25) and methylphenidate 2.39 (1.40–4.08) in adults only. Head-to-head clinician-rated efficacy favored amphetamines over methylphenidate, atomoxetine and modafinil. Insufficient data at 26 and 52 weeks.
Funding / affiliation: Non-industry (Stichting Eunethydis; UK NIHR Oxford Health BRC).
Cortese S, Adamo N, Del Giovane C, et al. (2018). Comparative efficacy and tolerability of medications for attention-deficit hyperactivity disorder in children, adolescents, and adults: a systematic review and network meta-analysis. Lancet Psychiatry 5(9):727-738. DOI · PubMed 30097390
-
ADHD treatments in children and teens (class)
Across 190 trials in children and teens, methylphenidate, amphetamine, atomoxetine, guanfacine and clonidine all worked better than placebo. Methylphenidate and amphetamine appeared more effective than atomoxetine and guanfacine. Behavioral therapy combined with a stimulant appeared better than either medicine type alone. Most effective medicines also caused harms such as reduced appetite, weight loss and sleep problems.
Bayesian network meta-analyses of 190 RCTs (52 interventions, 26,114 participants; ≥3 weeks follow-up). Medications more efficacious than placebo: methylphenidate, amphetamine, atomoxetine, guanfacine, clonidine. Methylphenidate and amphetamine more efficacious than atomoxetine and guanfacine; methylphenidate and clonidine better accepted (all-cause discontinuation) than placebo and atomoxetine. Behavioural therapy plus stimulants appeared superior to stimulants or nonstimulants alone. Harms included anorexia, weight loss and insomnia. Results expressed as ORs with credible intervals (not reproduced here).
Catalá-López F, Hutton B, Núñez-Beltrán A, et al. (2017). The pharmacological and non-pharmacological treatment of attention deficit hyperactivity disorder in children and adolescents: A systematic review with network meta-analyses of randomised trials. PLoS One 12(7):e0180355. DOI · PubMed 28700715
-
ADHD medicines (class): dose
An analysis of how benefit changes with dose (113 trials) found that, in children and teens, extra benefit stopped rising above about 45 mg/day of methylphenidate, 25 mg/day of amphetamines and 4 mg/day of guanfacine, although data at higher doses were thin. Stopping for side effects rose at higher amphetamine doses, and at methylphenidate doses above 50 mg/day in adults. No dose–benefit pattern was found for atomoxetine in fixed-dose studies.
Dose-effect NMA (Bayesian restricted cubic splines) of 113 double-blind RCTs: 68 pediatric (14,138 participants), 45 adult (11,016). Children/adolescents: median efficacy increased up to ~45 mg/day methylphenidate, ~25 mg/day amphetamines, ~4 mg/day guanfacine, with no evidence of added benefit above (wide credible intervals). Adults: amphetamines plateaued above ~50 mg/day; methylphenidate showed no plateau (sparse data). Dose-dependent AE-related discontinuation: amphetamines above 25 mg/day (children) and 50 mg/day (adults); methylphenidate above 50 mg/day in adults, no clear dose dependence in children. No dose-effect pattern for atomoxetine (fixed-dose studies) or modafinil. Needs full-text check: how amphetamine products were converted to a common dose scale is not stated in the abstract.
Funding / affiliation: Non-industry (UK NIHR).
Nourredine M, Jurek L, Hamza T, et al. (2026). Pharmacological interventions for ADHD: a systematic review and dose-effect network meta-analysis. Lancet Psychiatry 13(6):485-495. DOI · PubMed 42134365
-
Amphetamines vs methylphenidate (class)
A pooled analysis of 23 placebo-controlled trials in children and teens found that amphetamine products had somewhat larger average effects than methylphenidate products, even after adjusting for differences in study design. The trials did not compare the two directly.
Meta-analysis/meta-regression of 23 double-blind placebo-controlled trials (11 drugs, 19 outcome measures). Effect sizes for amphetamine products were significantly, though moderately, greater than for methylphenidate products after correcting for design features. Indirect comparison (no head-to-head trials).
Faraone SV, Buitelaar J (2010). Comparing the efficacy of stimulants for ADHD in children and adolescents using meta-analysis. Eur Child Adolesc Psychiatry 19(4):353-64. DOI · PubMed 19763664
-
Adult ADHD treatments (class)
In adults (113 trials), stimulants and atomoxetine were the only treatments that reduced core symptoms on both self-ratings and clinician ratings at 12 weeks. Several psychological approaches (such as CBT and mindfulness) helped only on clinician ratings. Atomoxetine and guanfacine were stopped more often than placebo.
Component NMA, 113 RCTs (14,887 adults). 12-week core symptoms: atomoxetine SMD −0.38 self-rated (−0.56 to −0.21), −0.51 clinician-rated (−0.64 to −0.37); stimulants about −0.39 self-rated (CI −0.52 to −0.26) and −0.61 clinician-rated (−0.71 to −0.51). CBT (−0.76), cognitive remediation, mindfulness, psychoeducation and tDCS beat placebo on clinician-rated measures only. Acceptability worse than placebo: atomoxetine OR 1.43 (1.14–1.80), guanfacine 3.70 (1.22–11.19).
Ostinelli EG, Schulze M, Zangani C, et al. (2025). Comparative efficacy and acceptability of pharmacological, psychological, and neurostimulatory interventions for ADHD in adults: a systematic review and component network meta-analysis. Lancet Psychiatry 12(1):32-43. DOI · PubMed 39701638
-
Methylphenidate vs atomoxetine (children)
Combining nine head-to-head trials (2,762 participants), methylphenidate and atomoxetine did not differ overall in effect or response rates. In a subgroup, long-acting OROS methylphenidate (the Concerta-type formulation) worked better than atomoxetine, while immediate-release methylphenidate did not.
Meta-analysis of 9 RCTs (n=2,762) comparing methylphenidate and atomoxetine. Overall SMD 0.09 (95% CI −0.08 to 0.26), NS; response RR 0.93 (0.76–1.14). Subgroup: OROS methylphenidate SMD 0.32 (0.12–0.53) favoring OROS; immediate-release methylphenidate −0.04 (−0.19 to 0.12). An update (Rezaei 2016, PMID 27390695; 11 studies, 2,772) reported the same pattern (OROS SMD 0.31, 0.16–0.47).
Hanwella R, Senanayake M, de Silva V (2011). Comparative efficacy and acceptability of methylphenidate and atomoxetine in treatment of attention deficit hyperactivity disorder in children and adolescents: a meta-analysis. BMC Psychiatry 11:176. DOI · PubMed 22074258
See also: Rezaei G, Hosseini SA, Akbari Sari A, et al. (2016). Med J Islam Repub Iran. PubMed 27390695
Long-term real-world outcomes (5 studies)
-
ADHD medicines (class): risk of death
In a Swedish national study of 148,578 people aged 6 to 64 newly diagnosed with ADHD, those who started ADHD medicine had a lower risk of dying over the next 2 years (39 vs 48 deaths per 10,000 people). The difference came mainly from fewer deaths from unnatural causes such as injuries, accidental poisonings and suicide; deaths from natural causes did not differ significantly. This is an observational study: it shows an association, not proof that the medicine caused the difference.
Target trial emulation, Swedish registers (diagnosis 2007–2018; 2-year follow-up); n=148,578, of whom 84,204 (56.7%) started medication within 3 months. 2-year mortality 39.1 vs 48.1 per 10,000 (risk difference −8.9; 95% CI −17.3 to −0.6). All-cause HR 0.79 (0.70–0.88); unnatural-cause HR 0.75 (0.66–0.86); natural-cause HR 0.86 (0.71–1.05), not significant. Class-level estimate (all ADHD medicines); the abstract does not report methylphenidate separately.
Li L, Zhu N, Zhang L, et al. (2024). ADHD Pharmacotherapy and Mortality in Individuals With ADHD. JAMA 331(10):850-860. DOI · PubMed 38470385
-
ADHD medicines (class; 88% started on methylphenidate)
Using the same Swedish registers (148,581 people aged 6 to 64 newly diagnosed with ADHD), starting ADHD medicine was linked over 2 years to fewer first episodes of suicidal behavior (about 17% fewer), substance misuse (15%), transport accidents (12%) and criminal offenses (13%). Accidental injuries were not significantly reduced for first events, but repeat events of all five kinds were lower. Methylphenidate was the first medicine for 88% of people who started treatment. Observational: an association, not proof.
Target trial emulation, Swedish registers 2007–2020; n=148,581; 84,282 (56.7%) initiated treatment, methylphenidate in 74,515 (88.4%). First events, adjusted IRR: suicidal behaviour 0.83 (95% CI 0.78–0.88); substance misuse 0.85 (0.83–0.87); transport accidents 0.88 (0.82–0.94); criminality 0.87 (0.83–0.90); accidental injuries 0.98 (0.96–1.01), not significant. Recurrent events: all five reduced (IRR 0.75–0.96). Class-level estimates.
Zhang L, Zhu N, Sjölander A, et al. (2025). ADHD drug treatment and risk of suicidal behaviours, substance misuse, accidental injuries, transport accidents, and criminality: emulation of target trials. BMJ 390:e083658. DOI · PubMed 40803836
-
ADHD medicines (class): changes over time
A Swedish study of 247,420 people who used ADHD medicine between 2006 and 2020 compared periods on and off medicine in the same people. Medicine periods were consistently linked to fewer self-harm events, unintentional injuries, traffic crashes and crimes. However, the links for injuries, crashes and crime became weaker over time as the share of people taking ADHD medicine rose from 0.6% to 2.8%.
Self-controlled case series, Swedish registers, ages 4–64, n=247,420; periods 2006–2010, 2011–2015 and 2016–2020 (medication prevalence 0.6% to 2.8%). Medicated vs non-medicated IRR ranges: self-harm 0.77 (0.73–0.81) to 0.85 (0.82–0.88); unintentional injury 0.87 (0.84–0.89) to 0.93 (0.91–0.95); traffic crashes 0.71 (0.67–0.77) to 0.87 (0.83–0.91); crime 0.73 (0.71–0.75) to 0.84 (0.82–0.85). Weakening over time for injury, crashes and crime (P for trend <.01), not fully explained by changes in age and sex mix.
Li L, Coghill D, Sjölander A, et al. (2025). Increased Prescribing of Attention-Deficit/Hyperactivity Disorder Medication and Real-World Outcomes Over Time. JAMA Psychiatry 82(8):830-837. DOI · PubMed 40560574
-
ADHD medicines (class): criminal convictions
Comparing the same 25,656 people with ADHD in Sweden during periods on and off medicine (2006–2009), criminal convictions were 32% lower in men and 41% lower in women while they were taking ADHD medicine. This links treatment with fewer crimes but cannot prove the medicine caused the drop.
Swedish registers 2006–2009, n=25,656; stratified (within-individual) Cox regression, medicated vs non-medicated periods. Criminality: men adjusted HR 0.68 (95% CI 0.63–0.73); women HR 0.59 (0.50–0.70). Reductions of 17% to 46% in male sensitivity analyses (including by drug type, stimulant vs nonstimulant, and type of crime). Class-level estimate.
Funding / affiliation: Non-industry (Swedish Research Council and others).
Lichtenstein P, Halldner L, Zetterqvist J, et al. (2012). Medication for attention deficit-hyperactivity disorder and criminality. N Engl J Med 367(21):2006-14. DOI · PubMed 23171097
-
ADHD medicines (class): serious transport accidents
Following 17,408 people with ADHD in Sweden from 2006 to 2009, men had 58% fewer serious transport accidents (emergency visits or deaths) during periods when they were taking ADHD medicine than when they were not. No significant difference was found in women.
Swedish registers 2006–2009, n=17,408. ADHD vs no ADHD, serious transport accidents: men adjusted HR 1.47 (95% CI 1.32–1.63), women 1.45 (1.24–1.71). Within-individual comparison of medicated vs non-medicated periods: men HR 0.42 (0.23–0.75); women not statistically significant. The authors estimated that 41% to 49% of accidents in men with ADHD might have been avoided with treatment throughout follow-up (a modelled estimate). Class-level estimate.
Chang Z, Lichtenstein P, D'Onofrio BM, et al. (2014). Serious transport accidents in adults with attention-deficit/hyperactivity disorder and the effect of medication: a population-based study. JAMA Psychiatry 71(3):319-25. DOI · PubMed 24477798
Heart and blood pressure (10 studies)
-
Methylphenidate, amphetamines, atomoxetine (children)
Pooling 18 trials in 5,837 children and teens, methylphenidate, amphetamines and atomoxetine all raised systolic blood pressure slightly on average. Amphetamines and atomoxetine also raised heart rate and diastolic pressure; methylphenidate did not. About 2% stopped because of heart-related effects. The authors advise regular heart rate and blood pressure checks.
Systematic review/meta-analysis, 18 trials (10 MPH, 5 AMP, 7 ATX), n=5,837, mean 28.7 weeks. Pre–post SBP SMD: MPH 0.25 (0.08–0.42), AMP 0.09 (0.03–0.15), ATX 0.16 (0.04–0.27). DBP: AMP 0.16 (0.03–0.29), ATX 0.22 (0.10–0.34); HR: AMP 0.37 (0.13–0.60), ATX 0.43 (0.26–0.60); MPH no pre–post effect on DBP or HR. No significant head-to-head differences. 2% discontinued for any cardiovascular effect.
Hennissen L, Bakker MJ, Banaschewski T, et al. (2017). Cardiovascular Effects of Stimulant and Non-Stimulant Medication for Children and Adolescents with ADHD: A Systematic Review and Meta-Analysis of Trials of Methylphenidate, Amphetamines and Atomoxetine. CNS Drugs 31(3):199-215. DOI · PubMed 28236285
-
ADHD medicines (class)
Pooling 102 short-term trials, most ADHD medicines raised blood pressure and pulse modestly, and stimulants did not raise them more than atomoxetine or viloxazine. Guanfacine lowered blood pressure and pulse. The authors advise monitoring blood pressure and pulse with any ADHD medicine, not just stimulants.
NMA of 102 RCTs (13,315 children/adolescents; 9,387 adults; median 7 weeks). Children, mean increase vs placebo: SBP 1.07 (atomoxetine) to 1.81 mm Hg (methylphenidate); DBP 1.93 (amphetamines) to 2.42 (methylphenidate); pulse 2.79 bpm (viloxazine) to 5.58 bpm (atomoxetine). Amphetamines, lisdexamfetamine and methylphenidate not associated with larger increments than atomoxetine or viloxazine. Guanfacine in children: SBP −2.83 (−3.8 to −1.85), DBP −2.08, pulse −4.06. Only four RCTs informed medium-term effects. CINeMA confidence mostly low to moderate in children, very low in adults.
Funding / affiliation: Non-industry (UK NIHR).
Farhat LC, Lannes A, Del Giovane C, et al. (2025). Comparative cardiovascular safety of medications for attention-deficit hyperactivity disorder in children, adolescents, and adults: a systematic review and network meta-analysis. Lancet Psychiatry 12(5):355-365. DOI · PubMed 40203844
-
Methylphenidate and atomoxetine
Pooling 22 studies (46,107 people), methylphenidate raised heart rate and systolic blood pressure compared with placebo in young people and adults; in children, atomoxetine raised them more than methylphenidate. Serious cardiac events did not differ.
Meta-analysis/meta-regression of 22 studies (n=46,107). MPH vs placebo: greater pre–post HR (p<0.001) and SBP (p<0.001) increases in youth and adults. Children/adolescents: ATX > MPH for HR (p=0.025) and SBP (p<0.001). Moderators: age, dose, duration. No difference in adverse cardiac events (MPH vs placebo or ATX). Effects reported as standardized differences, not bpm/mm Hg, in the abstract.
Liang EF, Lim SZ, Tam WW, et al. (2018). The Effect of Methylphenidate and Atomoxetine on Heart Rate and Systolic Blood Pressure in Young People and Adults with Attention-Deficit Hyperactivity Disorder (ADHD): Systematic Review, Meta-Analysis, and Meta-Regression. Int J Environ Res Public Health 15(8). DOI · PubMed 30127314
-
ADHD medicines (class), long-term use
In a Swedish registry study of 278,027 people with ADHD (ages 6–64), longer total use of ADHD medicine was linked to a higher risk of cardiovascular disease, about 4% more per year of use, mainly high blood pressure and arterial disease. This kind of study shows an association, not proof of cause.
Nested case-control (Swedish registers, 2007–2020): 10,388 CVD cases vs 51,672 matched controls. Cumulative use vs non-use: 3–≤5 y AOR 1.27 (1.17–1.39); >5 y 1.23 (1.12–1.36). Per year of use AOR 1.04 (1.03–1.05), steeper in first 3 years (1.08). Hypertension 3–≤5 y AOR 1.72 (1.51–1.97), >5 y 1.80 (1.55–2.08). Similar in under-25s and adults. Not broken down by individual drug in the abstract.
Zhang L, Li L, Andell P, et al. (2024). Attention-Deficit/Hyperactivity Disorder Medications and Long-Term Risk of Cardiovascular Diseases. JAMA Psychiatry 81(2):178-187. DOI · PubMed 37991787
-
Methylphenidate (all forms)
A South Korean study of 1,224 children and teens who had a heart-related event while on methylphenidate found a higher rate of heart rhythm problems during treatment periods, and a higher rate of heart attack in the first weeks after starting. Absolute risk is likely low. No increase was seen for high blood pressure, stroke or heart failure.
Nationwide self-controlled case series (2008–2011), 1,224 patients ≤17 y with an incident CV event and methylphenidate exposure. Arrhythmia IRR 1.61 (95% CI 1.48–1.74) across exposed periods, highest with congenital heart disease. Myocardial infarction 1.33 (0.90–1.98) overall, elevated in the early 8–56 day window. No significant increase for hypertension, ischaemic stroke or heart failure.
Shin JY, Roughead EE, Park BJ, et al. (2016). Cardiovascular safety of methylphenidate among children and young people with attention-deficit/hyperactivity disorder (ADHD): nationwide self controlled case series study. BMJ 353:i2550. DOI · PubMed 27245699
-
Methylphenidate (all forms)
In a large Taiwanese cohort of 224,732 people with ADHD, methylphenidate users did not have a higher risk of major cardiovascular events than non-users over the study period.
Propensity-matched cohort: 224,732 patients. Major CV events, MPH >7 days vs non-users HR 0.85 (0.72–0.99); >180 days 0.83 (0.69–1.00). Authors call for more evidence on long-term use.
Liao HC, Hsu CN, Lin FJ, et al. (2024). Association between methylphenidate use and long-term cardiovascular risk in paediatric patients with attention deficit and hyperactivity disorder. BMJ Paediatr Open 8(1). DOI · PubMed 39231572
-
Methylphenidate (all forms)
A Danish general-population study (median age 72 among cardiac arrest cases) found methylphenidate use was linked to higher odds of out-of-hospital cardiac arrest, especially in the first 6 months after starting. Few users were in the study, and most were much older than typical ADHD patients.
Nested case-control: 46,578 OHCA cases (median 72 y) vs 232,890 matched controls; MPH used by 80 cases, 166 controls. OR 1.78 (1.32–2.40); recent starters ≤180 days 2.59 (1.28–5.23). Persisted in those without hospital-diagnosed ADHD.
Eroglu TE, Halili A, Arulmurugananthavadivel A, et al. (2023). Use of methylphenidate is associated with increased risk of out-of-hospital cardiac arrest in the general population: a nationwide nested case-control study. Eur Heart J Cardiovasc Pharmacother 9(7):658-665. DOI · PubMed 37070942
-
Stimulants and nonstimulants (children and teens)
The 2019 American Academy of Pediatrics guideline says stimulants have not been shown to raise the risk of sudden death. Before starting, clinicians should ask about heart symptoms and a family history of sudden death or inherited heart rhythm or muscle conditions, and arrange further evaluation if any risk factor is present. It describes an ECG as part of that extra evaluation for nonstimulants when risk factors are present.
AAP clinical practice guideline (Wolraich 2019), full text: obtain history of specific cardiac symptoms and family history of sudden death, cardiovascular symptoms, WPW, HCM and long QT before stimulants; if risk factors are present, obtain additional evaluation. For nonstimulants with risk factors, the additional evaluation is described as an ECG, with pediatric cardiology referral if abnormal. No routine ECG is recommended for patients without risk factors.
Wolraich ML, Hagan JF Jr, Allan C, et al. (2019). Clinical Practice Guideline for the Diagnosis, Evaluation, and Treatment of Attention-Deficit/Hyperactivity Disorder in Children and Adolescents. Pediatrics 144(4). DOI · PubMed 31570648
-
ADHD medicines (class)
The European ADHD Guidelines Group found no evidence that a routine ECG before starting ADHD medicine adds benefit. It notes that the American Heart Association first suggested an ECG as standard in 2008 and then left it to the clinician’s judgment. A 2009 Canadian joint statement likewise recommends a careful history and examination, with an ECG or cardiology referral only when these suggest a problem.
European Guidelines Group (EUNETHYDIS) review of adverse effects, full text: “no current evidence to suggest an incremental benefit for routine ECG assessment” before medication; AHA in 2008 initially recommended ECG as standard, then changed this to clinician discretion; ECG screening not considered cost-effective for preventing sudden death in the general pediatric population. Canadian Paediatric Society / Canadian Cardiovascular Society / CACAP joint statement (Warren 2009, abstract): thorough history and physical examination; no routine ECG screening or cardiac subspecialist consultation unless indicated by history or examination.
Graham J, Banaschewski T, Buitelaar J, et al. (2011). European guidelines on managing adverse effects of medication for ADHD. Eur Child Adolesc Psychiatry 20(1):17-37. DOI · PubMed 21042924
See also: Warren AE, Hamilton RM, Bélanger SA, et al. (2009). Can J Cardiol. DOI · PubMed 19898693
-
Children with ADHD (screening ECG)
At one U.S. center, 1,470 children with ADHD had a screening ECG. About 8% were read as abnormal, but heart disease was found in only 5 children (0.3%), so most abnormal results were false alarms. Finding each true case cost about $17,000 in testing.
Retrospective review of screening ECGs in 1,470 patients <21 y with ADHD (Apr–Sep 2008): 119 abnormal (8.1%); follow-up included 63 echocardiograms, 5 stress tests, 9 Holters; cardiac disease in 5 (0.3%: ventricular pre-excitation 2, bicuspid aortic valve 2, secundum ASD 1); positive predictive value 4.2%; mean cost $58 per child and $17,162 per true positive. The authors note screening can find asymptomatic disease but with low PPV.
Mahle WT, Hebson C, Strieper MJ (2009). Electrocardiographic screening in children with attention-deficit hyperactivity disorder. Am J Cardiol 104(9):1296-9. DOI · PubMed 19840580
Growth (6 studies)
-
Methylphenidate (all forms)
In a German national health survey of 4,244 boys, methylphenidate use was linked to very low body-mass index in some age groups, but not to short stature or blood pressure changes. Numbers of treated boys were small.
KiGGS survey analysis: 4,244 boys (MPH <12 months n=65; ≥12 months n=53; ADHD controls 320; non-ADHD 3,806). BMI ≤3rd percentile more likely in pre-pubertal boys with <12 months of MPH and pubertal/post-pubertal boys with ≥12 months. No association with low height (≤3rd percentile) or BP changes.
McCarthy S, Neubert A, Man KKC, et al. (2018). Effects of long-term methylphenidate use on growth and blood pressure: results of the German Health Interview and Examination Survey for Children and Adolescents (KiGGS). BMC Psychiatry 18(1):327. DOI · PubMed 30305167
-
Stimulants (mostly OROS methylphenidate), children 5–12
Children whose weight dropped after starting a stimulant were randomly assigned to medicine on school days only (a planned break on weekends and holidays), a daily high-calorie snack, or monthly checks. All three helped weight gain, but none of them sped up growth in height. Most families in the school-days-only group went back to giving the medicine after school because symptoms got worse.
RCT, 230 children aged 5–12 starting stimulants (78%, mainly OROS-MPH) or behavioral treatment for 30 months; children with a BMI decline >0.5 z after 6 months (n=71) were randomized to monthly monitoring, drug holidays (medication limited to school days) or a 150-kcal daily supplement. Weight velocity rose after randomization across all arms (β=0.271, SE 0.027, p<.001); per actual use, supplementation (p<.01) and holidays (p<.05) increased weight velocity more than monitoring. No arm increased height velocity. Full text: parents gave medication on only 5% of weekend days in the holiday arm; 16 of 23 (70%) reverted to after-school dosing because of worsening symptoms.
Waxmonsky JG, Pelham WE 3rd, Campa A, et al. (2020). A Randomized Controlled Trial of Interventions for Growth Suppression in Children With Attention-Deficit/Hyperactivity Disorder Treated With Central Nervous System Stimulants. J Am Acad Child Adolesc Psychiatry 59(12):1330-1341. DOI · PubMed 31473291
-
Methylphenidate (immediate-release, twice daily)
In a 4-week trial in boys taking methylphenidate twice a day, swapping in a placebo on weekends led to less trouble sleeping and a trend toward better appetite. ADHD symptoms on weekends (parent ratings) and on the following Monday (teacher ratings) did not rise significantly. The study was small and short.
Double-blind RCT, 28 days, boys with ADHD: MPH b.i.d. 7 days/week (n=21) vs weekdays with weekend placebo (n=19). No significant group difference in parent weekend ratings (endpoint p=0.41, ES 0.26) or Monday teacher ratings (p=0.99, ES 0.002). Weekend placebo: less insomnia (F=3.96, p=0.05) and a trend to less appetite interference (F=3.18, p=0.08). Growth was not an outcome.
Martins S, Tramontina S, Polanczyk G, et al. (2004). Weekend holidays during methylphenidate use in ADHD children: a randomized clinical trial. J Child Adolesc Psychopharmacol 14(2):195-206. DOI · PubMed 15319017
-
Methylphenidate (long-term use)
Children on long-term methylphenidate were randomly assigned to stop or continue it over two summers. One summer off was followed by more weight gain but no height difference; two summers off had a significant positive effect on height. The study could not show whether this changes final adult height.
Controlled withdrawal study: hyperactive children on long-term MPH randomized to be off or remain on medication over two consecutive summers. After one summer: no height difference, higher weight in the off-medication group. After two summers: significant positive effect on height (not weight). Authors note the results do not address long-term effects on height. Needs full-text check: sample size and effect sizes are not in the abstract.
Klein RG, Landa B, Mattes JA, et al. (1988). Methylphenidate and growth in hyperactive children. A controlled withdrawal study. Arch Gen Psychiatry 45(12):1127-30. DOI · PubMed 3058088
-
ADHD medicines (mostly stimulants), children and teens
A review of 22 studies from 1972 to 2013 found that 25–70% of families take breaks from ADHD medicine, most often during school holidays. Breaks are used to check whether medicine is still needed and to manage side effects. Longer breaks were linked to better growth, and shorter breaks could reduce sleep problems and improve appetite.
Literature review (22 studies, 1972–2013) of drug holidays in children and adolescents. Prevalence 25–70% of families, more often in school holidays; purposes: testing ongoing need, managing adverse effects and tolerance. Positive impact on growth with longer breaks; shorter breaks could reduce insomnia and improve appetite. Study quality not graded in the abstract.
Ibrahim K, Donyai P (2015). Drug Holidays From ADHD Medication: International Experience Over the Past Four Decades. J Atten Disord 19(7):551-68. DOI · PubMed 25253684
-
Stimulants (MTA follow-up into adulthood)
In the long-term follow-up of the MTA study, young adults who had taken stimulants consistently through childhood were on average about 2.4 cm shorter than those who took them inconsistently, and treated groups were about 2.6 cm shorter than those who took little or none. Consistent long-term use was not linked to fewer adult ADHD symptoms. These groups were not randomized.
Observational follow-up of the MTA (579 randomized; 515 followed; 289 classmates as local norms), outcomes at ~25 years. Adult height: Consistent/Inconsistent users 2.55 ± 0.73 cm shorter than Negligible users (p<.0005); Consistent 2.36 ± 1.13 cm shorter than Inconsistent (p<.04). Naturalistic-subgroup comparisons for symptom severity were not significant. Full text: height was measured in 402 ADHD participants (Consistent subgroup n=33).
Swanson JM, Arnold LE, Molina BSG, et al. (2017). Young adult outcomes in the follow-up of the multimodal treatment study of attention-deficit/hyperactivity disorder: symptom persistence, source discrepancy, and height suppression. J Child Psychol Psychiatry 58(6):663-678. DOI · PubMed 28295312
Psychosis and mania (6 studies)
-
Amphetamine vs methylphenidate
In US insurance data on 221,846 adolescents and young adults (13–25) starting a stimulant, new psychosis treated with an antipsychotic occurred in about 1 in 660. It was about twice as common with amphetamine (0.21%) as with methylphenidate (0.10%).
Propensity-matched cohort (2 claims databases, 2004–2015): 110,923 MPH vs 110,923 amphetamine starters. 343 psychosis episodes: 106 (0.10%) MPH vs 237 (0.21%) amphetamine; HR 1.65 (95% CI 1.31–2.09) for amphetamine.
Funding / affiliation: Non-industry (NIMH and others).
Moran LV, Ongur D, Hsu J, et al. (2019). Psychosis with Methylphenidate or Amphetamine in Patients with ADHD. N Engl J Med 380(12):1128-1138. DOI · PubMed 30893533
-
Amphetamines (class)
Among young people hospitalized for psychiatric reasons, recent prescription amphetamine use was linked to higher odds of a first episode of psychosis or mania, and the link was strongest at higher doses (above 30 mg of dextroamphetamine-equivalent). Recent methylphenidate use was not linked. Because only hospitalized patients were compared, results may not apply to everyone.
Case-control (McLean Hospital EHR, 2005–2019): 1,374 cases (incident psychosis/mania, ages 16–35) vs 2,748 psychiatric controls. Past-month amphetamine aOR 2.68 (1.90–3.77); >30 mg dextroamphetamine equivalents ~5.28-fold. Methylphenidate aOR 0.91 (0.54–1.55). Selection bias acknowledged.
Moran LV, Skinner JP, Shinn AK, et al. (2024). Risk of Incident Psychosis and Mania With Prescription Amphetamines. Am J Psychiatry 181(10):901-909. DOI · PubMed 39262211
-
Methylphenidate (all forms)
A Cochrane-method review could not confirm or rule out that methylphenidate causes psychotic symptoms such as hallucinations in children. Such symptoms were reported in roughly 1 to 2.5 of every 100 children in the available studies, and families should know to report them.
Systematic review: 10 RCTs (1,103 participants), 17 non-randomised studies, 12 case reports/series. RCTs: 10/654 MPH vs 1/508 placebo, RR 2.07 (0.58–7.35), underpowered, 9/10 high risk of bias. Non-randomised pooled prevalence 1.2% (0.7–2.4). One comparative cohort RR 1.36 (1.17–1.57), critical risk of bias. Possible frequency 1.1–2.5%.
Ramstad E, Storebø OJ, Gerner T, et al. (2018). Hallucinations and other psychotic symptoms in response to methylphenidate in children and adolescents with attention-deficit/hyperactivity disorder: a Cochrane systematic review with meta-analysis and trial sequential analysis(). Scand J Child Adolesc Psychiatr Psychol 6(1):52-71. DOI · PubMed 33520751
-
Stimulants in ADHD (class): psychosis and bipolar disorder
Pooling 16 studies of about 391,000 people with ADHD, a 2025 review estimated that roughly 2% to 4% of people treated with stimulants later had psychotic symptoms, a psychotic disorder or bipolar disorder, although results varied widely between studies. Psychosis was more common with amphetamines than with methylphenidate. These studies cannot show that the medicine caused the problems, and the authors advise discussing these risks and watching for them during treatment.
Systematic review and meta-analysis (searches to Oct 1, 2024), 16 studies, N=391,043 (mean age 12.6 y). Pooled occurrence among stimulant-treated individuals: psychotic symptoms 2.76% (95% CI 0.73–9.88; k=10), psychotic disorder 2.29% (1.52–3.40; k=4), bipolar disorder 3.72% (0.77–16.05; k=4); heterogeneity I² >95%. Psychosis, amphetamines vs methylphenidate: OR 1.57 (1.15–2.16; k=3, n=231,325). Higher occurrence in North American studies, with longer follow-up, more female participants, smaller samples and higher stimulant doses. Observational data; causality not established.
Salazar de Pablo G, Aymerich C, Chart-Pascual JP, et al. (2025). Occurrence of Psychosis and Bipolar Disorder in Individuals With Attention-Deficit/Hyperactivity Disorder Treated With Stimulants: A Systematic Review and Meta-Analysis. JAMA Psychiatry 82(11):1103-1112. DOI · PubMed 40900605
-
Methylphenidate in adults with bipolar disorder
In Swedish national registers, 2,307 adults with bipolar disorder started methylphenidate. Those taking it without a mood stabilizer had a much higher rate of mania in the next 3 months, while those also taking a mood stabilizer did not; their rate was lower than before. The authors advise checking carefully for bipolar disorder before starting a stimulant on its own.
Linked Swedish registers, 2006–2014; n=2,307 adults with bipolar disorder starting methylphenidate. Within-individual Cox regression comparing mania (hospitalization or new mood-stabilizer dispensing) 0–3 months after start with untreated periods. Methylphenidate monotherapy: HR 6.7 (95% CI 2.0–22.4), similar for months 3–6. With a mood stabilizer: HR 0.6 (0.4–0.9). Similar results counting only hospitalizations for mania.
Viktorin A, Rydén E, Thase ME, et al. (2017). The Risk of Treatment-Emergent Mania With Methylphenidate in Bipolar Disorder. Am J Psychiatry 174(4):341-348. DOI · PubMed 27690517
-
Methylphenidate in adults with bipolar disorder (French replication)
A French national claims study tried to repeat the Swedish findings. In 3,526 adults with bipolar disorder who were taking a mood stabilizer, methylphenidate was not linked to more mania, except at doses above 30 mg. In 2,745 people not taking a mood stabilizer, mania was more common in the 3 months after starting, but that link disappeared in a stricter analysis, and the authors think it may reflect the natural course of the illness.
French national claims database (SNDS), 2008–2024; self-controlled survival analysis of manic relapse in the 6 months before vs after a new methylphenidate dispensation. No mood stabilizer (n=2,745): inpatient mania diagnoses significantly higher within 3 months, not significant in self-controlled case-crossover analyses. Continuous mood stabilizer (n=3,526): no significant change except at >30 mg methylphenidate. Using new antimanic therapy as the outcome gave outlier results. Effect sizes are not given in the abstract.
Vidal N, Frileux S, Younes N, et al. (2026). Methylphenidate and manic relapse in bipolar disorders: A replication study in a nationwide claims database. J Psychopharmacol 2698811261443684. DOI · PubMed 42132544
Other safety findings (3 studies)
-
Daytrana (methylphenidate patch)
In an open-label study of 305 patch users, about half had clear redness at the patch site, usually fading within a day. Severe reactions were uncommon, and only 1 person (0.3%) was confirmed allergic to methylphenidate on skin testing.
Multisite open-label dermal study. ~50% definite erythema, generally resolved within 24 h; 4 subjects (1%) DRS score 4; one discontinued and was patch-test positive (0.3% sensitisation); 2 resolved post-study and tolerated oral MPH. Total enrolled not stated in the abstract (needs full-text check).
Warshaw EM, Squires L, Li Y, et al. (2010). Methylphenidate transdermal system: a multisite, open-label study of dermal reactions in pediatric patients diagnosed with ADHD. Prim Care Companion J Clin Psychiatry 12(6). DOI · PubMed 21494336
-
Daytrana (methylphenidate patch)
An expert panel advised that mild to moderate redness is common and usually not a reason to stop the patch; rotating sites, moisturizing and a topical steroid can help irritation. Allergic reactions are rare, and the patch should be stopped if one is suspected.
Expert panel (dermatology) consensus using clinic experience and sponsor trial data: erythema common; irritant contact dermatitis managed with site alternation, moisturising, gentle care, topical corticosteroid; allergic contact dermatitis/urticaria rare; discontinue if ACD suspected. Expert opinion, not trial evidence.
Warshaw EM, Paller AS, Fowler JF, et al. (2008). Practical management of cutaneous reactions to the methylphenidate transdermal system: recommendations from a dermatology expert panel consensus meeting. Clin Ther 30(2):326-37. DOI · PubMed 18343271
-
Daytrana (methylphenidate patch)
FDA reports described 51 cases of skin color loss (chemical leukoderma) with the methylphenidate patch, starting 2 months to 4 years after first use. The loss was permanent in every case, and sometimes spread beyond the patch site.
FAERS case series: 51 cases; median age 11; 43 at/near application site only, 7 also elsewhere; onset 2 months–4 years; persistent in all; 3 spread after discontinuation; 19 diagnosed as vitiligo. Spontaneous reports cannot give incidence.
Cheng C, La Grenade L, Diak IL, et al. (2017). Chemical Leukoderma Associated with Methylphenidate Transdermal System: Data From the US Food and Drug Administration Adverse Event Reporting System. J Pediatr 180:241-246. DOI · PubMed 27745746
ADHD with other conditions (1 study)
-
ADHD with tic disorders
In children with ADHD and tics (9 trials), methylphenidate, alpha-2 agonists (clonidine, guanfacine) and atomoxetine improved ADHD symptoms. Alpha-2 agonists and atomoxetine also reduced tics, and methylphenidate did not worsen tics in the short term. Very high doses of dextroamphetamine were linked to worse tics.
Meta-analysis, 9 studies, 477 subjects. ADHD efficacy: MPH, α2 agonists, desipramine, ATX. Tic improvement: α2 agonists and ATX. No evidence MPH worsened tics short-term; supratherapeutic dextroamphetamine worsened tics. Authors: MPH gave the greatest and most immediate ADHD improvement.
Bloch MH, Panza KE, Landeros-Weisenberger A, et al. (2009). Meta-analysis: treatment of attention-deficit/hyperactivity disorder in children with comorbid tic disorders. J Am Acad Child Adolesc Psychiatry 48(9):884-893. DOI · PubMed 19625978
Pregnancy (5 studies)
These research findings do not replace the FDA label. For what the label says, see Pregnancy and breastfeeding above.
-
Methylphenidate and amphetamines
In very large US and Nordic pregnancy registries, first-trimester methylphenidate was linked to a small increase in heart defects (about 28% higher relative risk), while amphetamines were not linked to more birth defects. Absolute risks remained low.
Cohort: 1,813,894 US Medicaid pregnancies; Nordic replication 2,560,069. US adjusted RR, MPH: any malformation 1.11 (0.91–1.35), cardiac 1.28 (0.94–1.74); amphetamines: any 1.05 (0.93–1.19), cardiac 0.96 (0.78–1.19). Pooled US+Nordic MPH cardiac RR 1.28 (1.00–1.64). US cardiac risk per 1,000: 12.7 unexposed, 18.8 MPH, 15.4 amphetamines.
Huybrechts KF, Bröms G, Christensen LB, et al. (2018). Association Between Methylphenidate and Amphetamine Use in Pregnancy and Risk of Congenital Malformations: A Cohort Study From the International Pregnancy Safety Study Consortium. JAMA Psychiatry 75(2):167-175. DOI · PubMed 29238795
-
Stimulants and atomoxetine in pregnancy
A 2026 review of 25 studies found that, after accounting for differences between mothers, using stimulants or atomoxetine in pregnancy was not linked to more major birth defects or to most pregnancy and child-development problems. A small link with methylphenidate and heart defects, and with a low newborn Apgar score, could not be ruled out and needs more study.
Systematic review/meta-analysis (25 studies; 23 pooled). Major malformations: unadjusted RR 1.25 (1.14–1.37), adjusted 1.04 (0.97–1.12). Cardiovascular malformations aRR 1.20 (0.88–1.63); methylphenidate-specific aRR 1.33 (1.01–1.74). No adjusted association with miscarriage, preterm birth, low birth weight, SGA, NICU admission or offspring neurodevelopmental disorders. Low 5-min Apgar aRR 1.21 (1.03–1.42). Authors attribute crude associations largely to confounding.
Komargodski R, Tillawe A, Berlin M, et al. (2026). Pregnancy and Offspring Outcomes After Prenatal Stimulant or Atomoxetine Exposure: A Systematic Review and Meta-analysis. Am J Obstet Gynecol MFM 102165. DOI · PubMed 42887725
-
Methylphenidate (all forms)
A Danish registry study of 364,012 pregnancies found methylphenidate in early pregnancy was not linked to more birth defects overall, but there was a possible increase in heart defects (mostly holes between heart chambers).
Registry cohort (2007–2014) using prenatal and postnatal diagnoses. MPH adjusted PR: malformations overall 1.04 (0.70–1.55); any cardiac 1.65 (0.89–3.05; NNH 92); ventricular septal defect 2.74 (1.03–7.28); severe cardiac 2.59 (0.98–6.90).
Kolding L, Ehrenstein V, Pedersen L, et al. (2021). Associations Between ADHD Medication Use in Pregnancy and Severe Malformations Based on Prenatal and Postnatal Diagnoses: A Danish Registry-Based Study. J Clin Psychiatry 82(1). DOI · PubMed 33406323
-
Methylphenidate and atomoxetine in pregnancy
Pooling 10 observational studies, birth defects and miscarriage were not more common in babies of mothers who took methylphenidate or atomoxetine in pregnancy than in unexposed babies.
Meta-analysis of 10 observational studies. vs unexposed offspring of mothers with ADHD: congenital anomalies OR 1.14 (0.83–1.55), miscarriage 1.01 (0.70–1.47); vs general population: anomalies 1.19 (0.93–1.53; I² 74%), miscarriage 1.05 (0.81–1.37). Preterm birth and birth weight not reported as outcomes in the abstract.
di Giacomo E, Confalonieri V, Tofani F, et al. (2024). Methylphenidate and Atomoxetine in Pregnancy and Possible Adverse Fetal Outcomes: A Systematic Review and Meta-Analysis. JAMA Netw Open 7(11):e2443648. DOI · PubMed 39504019
-
ADHD medicines in pregnancy (class)
Pooling 8 cohort studies, ADHD medicine during pregnancy was linked to more newborn intensive-care admissions but not to other maternal or newborn problems; methylphenidate showed a borderline link with heart defects.
Meta-analysis of 8 cohorts. NICU admission RR 1.88 (1.7–2.08) vs never exposed; 1.38 (1.23–1.54) vs exposure before/after pregnancy only. MPH and cardiac malformation RR 1.27 (0.99–1.63; p=0.065). No association with other outcomes; limited confounder adjustment.
Jiang HY, Zhang X, Jiang CM, et al. (2019). Maternal and neonatal outcomes after exposure to ADHD medication during pregnancy: A systematic review and meta-analysis. Pharmacoepidemiol Drug Saf 28(3):288-295. DOI · PubMed 30585374
Frequently asked questions
Where do you put the Daytrana patch?
On the hip, alternating sides each day, about 2 hours before the effect is needed. Follow the application instructions in the Medication Guide.
Can a Daytrana patch be cut to give a smaller dose?
No. The label says not to cut the patch. Use only whole, undamaged patches, and do not use one if its pouch is torn or the patch looks damaged. Your clinician can prescribe a smaller patch size instead.
How long is the patch worn?
Up to 9 hours. It can be removed earlier if a shorter effect is wanted or if late-day side effects appear. Effects continue for a few hours after removal.
Is there a generic version of Daytrana?
Yes. Generic methylphenidate transdermal systems rated AB to Daytrana are available, including an authorized generic distributed by Padagis.
How long does the effect last?
In studies, benefit was seen from 2 hours through 12 hours after the patch was applied, when worn for 9 hours.
Is Daytrana discontinued?
Sources disagree. ASHP reports that Noven discontinued brand Daytrana in early 2026, but as of Oct 29, 2026 the FDA Orange Book still lists Daytrana as an active prescription product and DailyMed lists all four Daytrana patch sizes as marketed. The FDA Drug Shortages database lists the Padagis-distributed patches made by Noven as available, and ASHP lists generic patches from Padagis and Mylan (Viatris) as available. Ask your pharmacy which versions it can currently order.
Can heat affect the patch?
Yes. Heat over the patch (such as heating pads) makes much more medicine absorb. Avoid direct heat on the patch.
What skin problems can the patch cause?
Redness at the site is common and usually mild. Some people develop an allergic skin reaction, and some have a lasting loss of skin color (chemical leukoderma). Tell your clinician about any skin changes.
If my child takes oral methylphenidate, what patch dose should they use?
The label says to start with the 10 mg patch and increase weekly as needed, even when switching from another methylphenidate product.
How should used patches be thrown away?
Fold the used patch in half so the sticky sides stick together, then flush it or dispose of it as directed in the patient instructions, out of reach of children and pets.
Does Daytrana interact with other medicines?
Yes. Do not use it with an MAOI antidepressant or within 14 days of stopping one. Tell your clinician if you take a blood thinner such as warfarin, seizure medicines (such as phenobarbital, phenytoin or primidone), or certain antidepressants (tricyclics or SSRIs): methylphenidate can raise their levels, so their doses may need to be lowered and checked when the patch is started or stopped.
Is the patch less likely to be misused than pills?
Not according to the label. Daytrana carries the same warning about misuse and addiction as methylphenidate pills, and used patches still contain medicine. Fold each used patch in half with the sticky sides together and throw it away as directed, out of reach of children and pets.
Do I need to take the patch off for an MRI?
The Daytrana label does not mention MRI. Always tell the MRI team about any skin patch you are wearing, and follow their instructions.
How quickly does Daytrana start working?
The patch is applied 2 hours before an effect is needed (label section 2.2). In the label’s classroom studies, benefit was significant from 2 hours through 12 hours after the patch was applied (label section 14).
Does food affect Daytrana?
Daytrana is a skin patch, so there are no meal instructions. The label says food effects have not been studied, but because the medicine is absorbed through the skin, no food effect is expected (label section 12.3).
Does Daytrana cause a crash or rebound as it wears off?
The Daytrana label does not describe a “crash” or rebound effect. Blood levels generally start to fall when the patch is removed, although absorption may continue for several hours, and the patch may be removed earlier than 9 hours if a shorter effect is wanted or late-day side effects appear (label section 2.5). If ADHD symptoms, irritability or tiredness come back as a dose wears off, tell your prescriber; the timing or dose may need adjusting.
Daytrana vs Concerta — what’s the difference?
Both contain methylphenidate. Daytrana is a patch worn on the hip for up to 9 hours, with benefit from 2 to 12 hours after application in its studies, and it can be removed early to shorten the effect; it can also cause skin reactions where it is applied. Concerta is an osmotic tablet swallowed whole in the morning, with effects maintained through 12 hours. See the Concerta page and the comparison table above.
What should I do if I forget to apply Daytrana?
The Medication Guide says you may apply the patch later in the day, but remove it at the usual time of day to lower the chance of side effects later in the day.
What are the most common side effects of Daytrana?
In children 6 to 12, the Medication Guide lists decreased appetite, trouble sleeping, nausea, vomiting, weight loss, tics, mood changes and trouble eating. In teens 13 to 17, it lists decreased appetite, nausea, trouble sleeping, weight loss, dizziness, stomach pain and trouble eating. Daytrana can also cause redness, small bumps or itching where it is applied. These are not all the possible side effects; call your prescriber for advice about side effects that bother you.
Is an ECG (heart tracing) needed before starting?
Usually not. Before prescribing, the clinician should ask about fainting, chest pain, a racing heartbeat, known heart problems, and any family history of sudden death or heart rhythm problems, and do a physical exam. An ECG or a visit to a heart specialist is used when any of these raise concern. UK, Canadian and European guidance does not call for a routine ECG when there are no such warning signs.
Can my child take breaks from the medicine on weekends or over the summer?
Sometimes, but plan it with the prescriber. Breaks can help with appetite, weight gain and sleep, and the label says children who are not growing or gaining weight as expected may need treatment paused. Breaks have not been shown to reliably make children taller, and ADHD symptoms can come back on days off, so it depends on how much your child struggles without the medicine. A break can also show whether the medicine is still needed.
Can I take Daytrana while pregnant or breastfeeding?
Tell your clinician if you are pregnant or planning a pregnancy. There is not enough information to know whether methylphenidate raises the risk of birth defects, miscarriage, or other problems in pregnancy. The Daytrana label says small amounts of methylphenidate pass into breast milk; if you breastfeed, decide together with your clinician and watch the baby for agitation, poor sleep, poor feeding, or slow weight gain. A pregnancy registry for ADHD medicines can be reached at 1-866-961-2388.
Prescribing guidelines
Methylphenidate-class extended-release formulations are first-line pharmacologic options for school-age children and adolescents per major guidelines when medication is indicated.
Resources
Sources
- Noven Therapeutics, LLC. Daytrana (methylphenidate transdermal system), CII. Prescribing Information, revised 09/2025. DailyMed (accessed Oct 2026).
- Padagis US LLC. Methylphenidate transdermal system SPL. DailyMed.
- Mylan Pharmaceuticals Inc. Methylphenidate patch SPL. DailyMed.
- U.S. Food and Drug Administration. Approved Drug Products with Therapeutic Equivalence Evaluations (Orange Book), data files dated October 2026 (products file dated Oct 9, 2026; rechecked with the Orange Book web search Oct 29, 2026). FDA; Orange Book search.
- National Library of Medicine. DailyMed product marketing information: Daytrana (Noven, SPL version 29), Padagis and Mylan methylphenidate transdermal system labels; accessed Oct 29, 2026. Daytrana; Mylan.
- U.S. Food and Drug Administration. Drug Shortages database: Methylphenidate Film, Extended Release, accessed Oct 29, 2026. FDA.
- American Society of Health-System Pharmacists. Drug Shortage Detail: Methylphenidate Transdermal System. Updated Mar 19, 2026 (not on the current-shortages list as of Oct 29, 2026; accessed Oct 29, 2026). ASHP.
- Wolraich ML, Hagan JF Jr, Allan C, et al.; American Academy of Pediatrics Subcommittee on Children and Adolescents with ADHD. Clinical Practice Guideline for the Diagnosis, Evaluation, and Treatment of Attention-Deficit/Hyperactivity Disorder in Children and Adolescents. Pediatrics. 2019;144(4):e20192528. AAP.
- Centers for Disease Control and Prevention. Clinical Care of ADHD in Children (summary of the AAP guideline; updated Oct 21, 2026). CDC (accessed 2026).
- Drugs and Lactation Database (LactMed). Methylphenidate. National Institute of Child Health and Human Development; revised Aug 2025. NCBI Bookshelf NBK501310.
- National Institute for Health and Care Excellence. Attention deficit hyperactivity disorder: diagnosis and management (NG87), 2018, updated 2019; recommendations 1.7.3–1.7.5, 1.7.20–1.7.22, 1.8.6–1.8.7 and 1.10.3. NICE (accessed Oct 2026).
- Pliszka S, AACAP Work Group on Quality Issues. Practice parameter for the assessment and treatment of children and adolescents with attention-deficit/hyperactivity disorder. J Am Acad Child Adolesc Psychiatry. 2007;46(7):894-921. PubMed 17581453.
- Substance Abuse and Mental Health Services Administration. Key Substance Use and Mental Health Indicators in the United States: Results from the 2023 National Survey on Drug Use and Health (HHS Publication No. PEP24-07-021, NSDUH Series H-59), 2024. SAMHSA (accessed Nov 9, 2026).