
Vyvanse
AMPHETAMINES · LISDEXAMFETAMINE · PRODRUG, ONCE DAILY
Key facts
- Drug class
- CNS Stimulant · Amphetamines
- Active ingredient
- lisdexamfetamine dimesylate
- FDA-approved ages
- ADHD: 6 years and older; BED: adults
- Form and strengths
- Capsule; chewable tablet; Capsules: 10, 20, 30, 40, 50, 60, 70 mg
Chewable tablets: 10, 20, 30, 40, 50, 60 mg - Usual dose and maximum (label)
- Start 30 mg once daily in the morning; maximum 70 mg/day.
- Duration
- Benefit through 12–13 hours in children and up to 14 hours in adults in label studies.
- DEA schedule
- Schedule II controlled substance (CII)
- Generic
- Generic available (see Generic manufacturers)
- Label date
- Prescribing Information revised 04/2026 (DailyMed)
Label last checked: Oct 2026 — Prescribing Information revised 04/2026 (DailyMed) · Last medical review: November 12, 2026
Educational information only, not medical advice. Do not start, stop or change a medication without your prescriber. Medical disclaimer
What it is
Vyvanse is a long-acting stimulant that the body converts into active medicine (dextroamphetamine). One morning dose usually covers the school or work day.
Lisdexamfetamine dimesylate is a pharmacologically inactive prodrug (it does not bind dopamine or norepinephrine reuptake sites in vitro) converted to d-amphetamine and l-lysine, mainly in the blood (red blood cells). Capsule Tmax ~1 h for lisdexamfetamine and ~3.5 h for d-amphetamine (children, fasted); food delays the d-amphetamine Tmax by about 1 hour (3.8 h fasted vs 4.7 h after a high-fat meal). Lisdexamfetamine t½ <1 h; d-amphetamine t½ ~8.6–9.5 h in children and ~10–11.3 h in adults. Indicated for ADHD (6 years and older) and moderate to severe BED in adults; not for weight loss. Label revised 04/2026. Schedule II.
When considering this for a patient
Vyvanse fits patients who need reliable once-daily amphetamine coverage for a long day, including adults; label studies showed improvement from 2 hours (not at 1 hour) through 12–13 hours in children and at each time point through 14 hours in adults. Capsule contents can be mixed with yogurt, water, or orange juice, and a chewable tablet is available, which helps patients who cannot swallow capsules.
Lisdexamfetamine is the only amphetamine product indicated for BED in adults (not for obesity or weight loss). Lisdexamfetamine doses are not equivalent mg-for-mg to other amphetamine products. Schedule II with the class boxed warning; the prodrug design does not remove abuse risk. Severe renal impairment and ESRD have maximum doses. Monitor appetite, sleep, growth, blood pressure, and heart rate.
Patient profile and niche
Vyvanse may be particularly useful in the following situations:
- Patients who need long once-daily coverage, including adults with long work days (adult study: improvement at each time point to 14 hours).
- Patients who cannot swallow capsules: contents can be mixed with yogurt, water, or orange juice, or a chewable tablet used.
- Adults with moderate to severe binge-eating disorder (the only labeled amphetamine for BED).
- When an AB-rated generic is preferred for cost, recognizing that some generic manufacturers report limited supply.
Less suited for children under 6, for patients who need flexible mid-day dosing, or as a weight-loss medication (not approved for obesity). A liquid form of lisdexamfetamine is available as Arynta.
When it is active
Lisdexamfetamine must first be converted to dextroamphetamine. In a pediatric label classroom study the effect was significant from 2 hours (not at 1 hour) through 12 hours after the dose, another pediatric study showed benefit averaged across 1.5 to 13 hours, and adults improved at each time point measured from 2 to 14 hours. Active d-amphetamine levels peak about 3.5 hours after a capsule (about an hour later with a high-fat meal, and about 4.4 hours after a chewable tablet).
Use the interactive tool below to align the typical Vyvanse profile with your schedule. The curve is a schematic based on labeling data, not a prediction for any individual.
Enter the times that match your (or your child’s) typical day. The curve shows relative plasma level over clock time.
The curve shows relative plasma concentration of active d-amphetamine (not guaranteed clinical effect).
Everyone is different. This is a general guide based on labeling data, not a prediction for any one person.
How it works
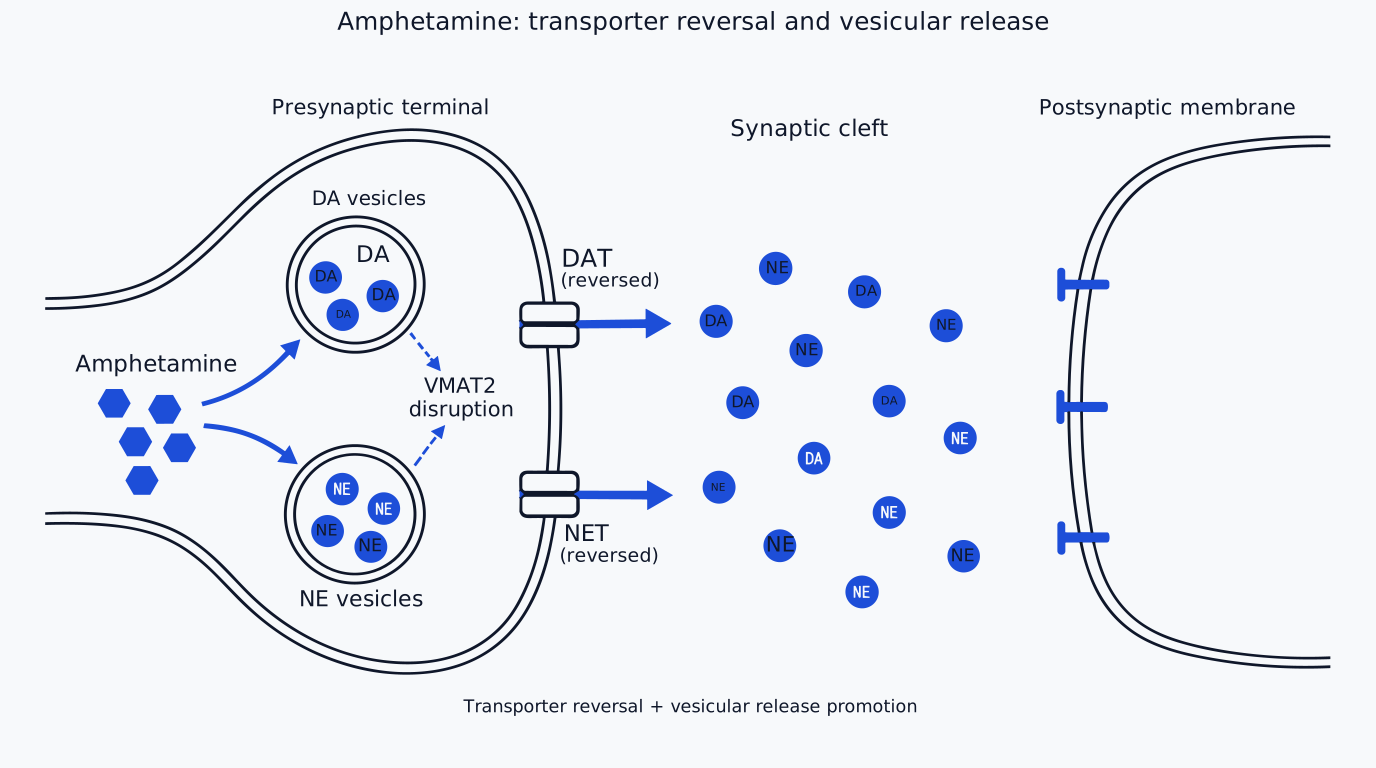
Lisdexamfetamine itself is inactive. After it is absorbed, it is split in the blood into dextroamphetamine and the amino acid lysine. Dextroamphetamine increases dopamine and norepinephrine between nerve cells by blocking their reuptake and promoting their release.
More synaptic dopamine
More synaptic norepinephrine
Per the label (sections 12.1–12.2), lisdexamfetamine is a prodrug of dextroamphetamine, and the exact mode of therapeutic action in ADHD and binge-eating disorder is not known. Amphetamines block the reuptake of norepinephrine and dopamine into the presynaptic neuron and increase the release of these monoamines into the extraneuronal space. The parent drug, lisdexamfetamine, does not bind to the sites responsible for the reuptake of norepinephrine and dopamine in vitro.
Pharmacokinetic consistency (label 12.3): after lisdexamfetamine, dextroamphetamine exposure in adults showed low inter-subject (<25%) and intra-subject (<8%) variability, was linear from 30 to 70 mg in children 6–12, and did not accumulate at steady state (Vyvanse label).
Formulations and duration
Once-daily capsule or chewable tablet taken in the morning, with or without food.
| STRENGTHS | Capsules: 10, 20, 30, 40, 50, 60, 70 mg Chewable tablets: 10, 20, 30, 40, 50, 60 mg |
|---|---|
| APPROVED AGES | ADHD: 6 years and older; BED: adults |
| ADMINISTRATION | Morning; capsule whole or contents mixed with yogurt, water, or orange juice (take immediately); chewables chewed thoroughly; avoid afternoon doses |
| RELATED | Lisdexamfetamine oral solution: Arynta (Azurity, approved 2025) |
| AVAILABILITY | Brand listed available; lisdexamfetamine on FDA shortage list |
Appearance
Brand Vyvanse capsules are imprinted “S489” and the strength (FDA label):
- 10 mg — pink body/pink cap
- 20 mg — ivory body/ivory cap
- 30 mg — white body/orange cap
- 40 mg — white body/blue-green cap
- 50 mg — white body/blue cap
- 60 mg — aqua blue body/aqua blue cap
- 70 mg — blue body/orange cap
Chewable tablets are white to off-white and debossed with the strength and “S489”; the shape differs by strength: 10 mg round, 20 mg hexagonal, 30 mg arc-triangular, 40 mg capsule-shaped, 50 mg arc-square, 60 mg arc-diamond.
Generic lisdexamfetamine products differ in color and imprint. Check the bottle label for the strength.
Official package photos and pill identifiers:
Generic manufacturers
Many companies make AB-rated generic lisdexamfetamine capsules, and several make chewable tablets. Some generic manufacturers report limited supply.
| Product | AB-rated ANDA holders (Orange Book, October 2026) |
|---|---|
| Capsules | Actavis, Alkem, Amneal, Apotex, Ascent, Elite, Granules, Hikma, Lannett, Mylan, Norwich, Prinston, Rhodes, Sandoz, SpecGx, Sun |
| Chewable tablets | Ascent, Granules, MSN, SpecGx, Sun, Teva |
| Supply | FDA lists lisdexamfetamine capsules and chewables as currently in shortage; ASHP (Aug 28, 2026) lists Apotex, Hikma, Solco, and Sun products as limited |
Generics launched in 2023. The table lists Orange Book ANDA holders with TE code AB. Distributor names on bottles may differ from ANDA holders.
Common side effects
Common side effects include decreased appetite, trouble sleeping, dry mouth, stomach ache, irritability, anxiety, nausea or vomiting, dizziness, and weight loss.
| EFFECT | FREQUENCY | NOTES |
|---|---|---|
| Decreased appetite / weight loss | Among the most common in label studies | Weight and growth are checked |
| Trouble sleeping | Among the most common in label studies | Take in the morning; avoid afternoon doses |
| Dry mouth | Among the most common in label studies | Usually mild |
| Stomach ache, nausea, vomiting, or diarrhea | Among the most common in label studies | Tell your clinician if it persists |
| Irritability or anxiety | Among the most common in label studies | Report mood changes |
| Dizziness | Among the most common in label studies | Tell your clinician if it persists |
| Faster heart rate | Among the most common in label studies (adults with binge-eating disorder) | Heart rate and blood pressure are checked |
Most common (≥5% and at least twice placebo) in pediatric and/or adult ADHD: anorexia, anxiety, decreased appetite, decreased weight, diarrhea, dizziness, dry mouth, irritability, insomnia, nausea, upper abdominal pain, and vomiting. In adults with BED: dry mouth, insomnia, decreased appetite, increased heart rate, constipation, feeling jittery, and anxiety. Boxed warning for abuse, misuse, and addiction; assess risk before prescribing and reassess during treatment. Warnings include risks to patients with serious cardiac disease, increased blood pressure and heart rate, psychiatric adverse reactions (screen for bipolar disorder risk), long-term suppression of growth in pediatric patients, peripheral vasculopathy including Raynaud’s phenomenon, seizures, serotonin syndrome with serotonergic drugs, and motor and verbal tics/worsening of Tourette’s syndrome. Contraindicated in patients with known hypersensitivity to amphetamine products or other ingredients (anaphylaxis, Stevens-Johnson syndrome, angioedema, and urticaria have been reported after marketing), and with MAOIs, during use or within 14 days of stopping, including linezolid or intravenous methylene blue, because of the risk of hypertensive crisis. Acidifying agents (e.g., ascorbic acid) decrease and alkalinizing agents (e.g., sodium bicarbonate) increase amphetamine blood levels; adjust the dose based on response (label 2 and 7.1).
Insomnia in the label’s 4-week ADHD trials (Tables 1–3): 22% vs 3% placebo (ages 6–12), 13% vs 4% (ages 13–17) and 27% vs 8% (adults); decreased appetite 39%, 34% and 27% respectively (Vyvanse label).
Dosing considerations
Most people start at 30 mg each morning, adjusted by 10–20 mg about weekly up to 70 mg. Lower maximums apply in severe kidney disease.
In label studies of children, teens and adults who were already doing well, those who kept taking the medicine were much less likely to have their symptoms come back over the following weeks than those switched to a placebo (about 1 in 6 or fewer, vs about 2 in 3 or more).
Before starting, your clinician should ask about heart problems, including any family history of sudden death or irregular heart rhythm, do a physical exam, and ask about tics or Tourette’s syndrome in you or your family.
Outside the label: large studies of health records in children, young adults and adults have not found a higher rate of heart attack, stroke or sudden cardiac death during ADHD medicine use. The label’s heart warnings and the checks above still apply.
ADHD (6 years and older): start 30 mg once daily in the morning; adjust in increments of 10 or 20 mg at approximately weekly intervals; maximum 70 mg/day. BED (adults): start 30 mg, titrate by 20 mg weekly to a target of 50–70 mg; maximum 70 mg; discontinue if binge eating does not improve. Severe renal impairment (GFR 15 to <30): maximum 50 mg/day; ESRD (GFR <15): maximum 30 mg/day. Lisdexamfetamine and d-amphetamine are not dialyzable. Vyvanse capsules can be substituted with chewable tablets on a unit-per-unit/mg-per-mg basis. Lisdexamfetamine dimesylate doses are not equivalent to mixed-salt or amphetamine-base doses, so other amphetamine products are not swapped mg-for-mg.
Maintenance of effect (label 14.1, Studies 6 and 9): in a randomized-withdrawal study in patients aged 6–17 (N=276 enrolled; 157 responders randomized after ≥26 weeks open-label), treatment failure over 6 weeks occurred in 15.8% on continued Vyvanse vs 67.5% switched to placebo; in adults aged 18–55 (N=123) it occurred in 9% vs 75% (Vyvanse label).
Pre-treatment screening (label 2.1): assess for cardiac disease with a careful history, family history of sudden death or ventricular arrhythmia, and physical exam; assess the family history and clinically evaluate for motor or verbal tics or Tourette’s syndrome.
Baseline ECG: The label’s pre-treatment cardiac assessment (above) is history, family history and examination; it does not call for a routine ECG. NICE NG87 states that an ECG is not needed before starting stimulants unless a feature listed in 1.7.5 is present (e.g., congenital heart disease or previous cardiac surgery, sudden cardiac death in a first-degree relative under 40, exertional breathlessness or syncope, paroxysmal palpitations, cardiac-sounding chest pain, signs of heart failure, a murmur, or adult hypertension) or a co-existing condition is treated with a medicine that adds cardiac risk; those features call for a cardiology opinion (1.7.4–1.7.5). The AAP 2019 guideline asks for a history of cardiac symptoms and a family history of sudden death, WPW, hypertrophic cardiomyopathy and long QT, with further evaluation if any risk factor is present. A Canadian joint position statement (Warren 2009) and the European ADHD Guidelines Group (Graham 2011) do not recommend routine ECG screening; Graham notes that the American Heart Association’s 2008 statement first proposed an ECG as standard and then left it to clinician discretion. In one US screening series, 8.1% of ECGs were abnormal but heart disease was found in 0.3% (Mahle 2009).
Outside the label (class-level cohorts; see Clinical evidence from published studies, Heart and blood pressure): current ADHD-medicine use was not associated with serious cardiovascular events in 1,200,438 people aged 2–24 (aHR 0.75, 95% CI 0.31–1.85; a doubling of risk could not be ruled out; Cooper 2011, PubMed 22043968) or in 150,359 adult users aged 25–64 (current vs remote use RR 1.03, 0.86–1.24; Habel 2011, PubMed 22161946). In FDA Sentinel (2,012,948 initiators of amphetamine products, methylphenidate or atomoxetine), new heart failure/cardiomyopathy was <50 per 10,000 person-years under age 45 (Mosholder 2018, PubMed 30102629).
Abuse potential: what the label shows
Vyvanse is a Schedule II stimulant with a boxed warning for abuse, misuse, and addiction. Its prodrug design does not prevent misuse, and it should be stored securely and never shared.
In a crossover abuse-liability study in 38 people with a history of drug abuse, lisdexamfetamine 100 mg produced significantly less “drug liking” than immediate-release d-amphetamine 40 mg, while 150 mg produced drug liking similar to d-amphetamine 40 mg and diethylpropion 200 mg. Intravenous lisdexamfetamine 50 mg produced positive subjective responses that were greater than placebo but less than an equivalent intravenous d-amphetamine dose (20 mg). (Vyvanse label, Section 9.2.) The previous “lower-moderate” relative ranking on this page was not label-based and has been replaced with these study data.
Planned breaks from medicine (weekends and holidays)
Some families leave out doses on weekends or during school holidays. This is sometimes called a medication holiday or treatment break. Plan any break with the prescriber instead of stopping on your own.
Breaks are usually considered for poor appetite, slow weight gain, trouble sleeping, slowed growth, or to see whether the medicine is still needed. The label says children who are not growing or gaining weight as expected may need to have treatment paused.
In studies, breaks helped appetite, sleep and weight gain. It is less clear that they help a child end up taller: one older study saw a height benefit only after two summers off, and a newer trial found that weekend breaks did not speed up height growth. ADHD symptoms can return on days off, so breaks tend to suit lower-pressure times. If you try one, watch how things go at home and with friends, and restart if problems come back.
Growth warning (label 5.5): monitor height and weight during treatment of pediatric patients; those not growing or gaining height or weight as expected may need treatment interrupted. NICE NG87 lists a planned break among options when weight loss is a concern (1.8.6), suggests considering a break over school holidays to allow catch-up growth when height is significantly affected (1.8.7), and advises periodic trial periods off medication or at a lower dose when the balance of benefit and harm suggests it (1.10.3). The AACAP 2007 practice parameter suggests considering a holiday when height or weight crosses two percentile lines, provided off-medication weekends or summers are not markedly impairing, and regards low-stress periods such as vacations (not the start of a school year) as a good time for a discontinuation trial.
Evidence (see Clinical evidence: Growth, below): in a 4-week RCT of twice-daily IR methylphenidate, weekend placebo reduced insomnia without a significant rise in weekend parent or Monday teacher ratings (Martins 2004, n=40). In children with stimulant-associated weight loss, school-days-only dosing increased weight velocity but not height velocity, and most families in that arm resumed after-school dosing because of symptoms (Waxmonsky 2020). Two summers off methylphenidate were followed by a height benefit; one summer was not (Klein 1988). A review of 22 studies found 25–70% of families use breaks (Ibrahim 2015). In the observational MTA follow-up, consistent long-term use was associated with about 2.4 cm lower adult height (Swanson 2017). Data in adults are sparse.
Pregnancy and breastfeeding
Tell your clinician if you are pregnant, plan to become pregnant, or are breastfeeding. Premature birth and low birth weight have been seen in babies whose mothers were dependent on amphetamines. Newborns exposed to amphetamines before birth should be watched for withdrawal symptoms such as feeding problems, irritability, agitation, or unusual sleepiness.
Outside the label: large studies of US and Swedish health records did not find that children exposed to amphetamines before birth were more likely to be diagnosed with autism or ADHD once the parent’s own health was taken into account. Some studies found a small increase in preeclampsia (high blood pressure in pregnancy) and in early (preterm) birth, mostly when a stimulant was continued after the first 3 months. Absolute risks stayed low. Decisions about continuing treatment are best made with your clinician. See Clinical evidence from published studies (Pregnancy) below. Few of these studies reported lisdexamfetamine separately; most grouped amphetamine products together.
Breastfeeding is not recommended while taking Vyvanse, because the medicine passes into breast milk.
A national pregnancy registry collects information about ADHD medicines used during pregnancy. You or your clinician can enroll by calling 1-866-961-2388.
Pregnancy (label 8.1): the limited published and postmarketing data are not sufficient to inform a drug-associated risk of major birth defects or miscarriage. Premature delivery and low birth weight have been reported in infants of amphetamine-dependent mothers. Amphetamines cause vasoconstriction that may reduce placental perfusion and can stimulate uterine contractions; monitor exposed infants for withdrawal (feeding difficulties, irritability, agitation, excessive drowsiness). Animal data: lisdexamfetamine had no effects on embryo-fetal morphology or survival in rats and rabbits; amphetamine (3:1 d:l) given to pregnant rats during gestation and lactation decreased pup survival and body weight, with delayed developmental landmarks; rodent literature reports long-term neurochemical and behavioral effects at doses similar to clinical use. Registry: National Pregnancy Registry for Psychostimulants (as named in the label), 1-866-961-2388.
Lactation (label 8.2): lisdexamfetamine is a prodrug of dextroamphetamine; limited case reports show amphetamine in human milk (relative infant dose 2% to 13.8%; milk/plasma ratio 1.9 to 7.5), with no reported adverse effects in breastfed infants. Long-term neurodevelopmental effects are unknown, and large doses might interfere with milk production. The label cites potential serious infant reactions, including cardiovascular effects, blood pressure and heart rate increases, growth suppression, and peripheral vasculopathy. The label advises that breastfeeding is not recommended during treatment.
Outside the label (observational cohorts; see Clinical evidence from published studies, Pregnancy): second-half-of-pregnancy amphetamine/dextroamphetamine exposure was not associated with child autism (aHR 0.80, 95% CI 0.56–1.14) or ADHD (aHR 1.07, 0.89–1.28) in US Medicaid (4,693 exposed) and commercial (2,372 exposed) cohorts (Suarez 2024; PubMed 38265792); a Swedish cohort of 861,650 children meta-analysed with Danish data gave a pooled HR for any neurodevelopmental disorder of 1.00 (0.83–1.20) (Bang Madsen 2025; PubMed 40148550). Stimulant use in early pregnancy (amphetamine-dextroamphetamine n=3,331) was associated with preeclampsia (aRR 1.29, 1.11–1.49), and continuation after 20 weeks with preterm birth (aRR 1.30, 1.10–1.55), with small absolute increases (Cohen 2017; PubMed 29112657). In 10,265 matched US patients, continuation into the 2nd/3rd trimester was associated with pre-eclampsia (RR 1.42, 1.19–1.69) and preterm birth (RR 1.34, 1.12–1.62), but first-trimester-only exposure was not (preterm RR 0.75) (Hasan 2026; PubMed 41400021). First-trimester malformation data remain limited (MGH registry, mixed amphetamine salts n=173, lisdexamfetamine n=40: OR 0.39, 0.09–1.61; Szpunar 2023; PubMed 37235505). These findings do not change the label’s section 8.1 statement.
Outside the label: LactMed (NCBI Bookshelf, “Lisdexamfetamine,” revised Apr 2026; NBK501741) notes that lisdexamfetamine is converted to dextroamphetamine and says some evidence suggests prescribed doses might not harm breastfed infants, but effects on infant neurodevelopment have not been well studied and large doses might reduce milk supply, especially before lactation is well established; it notes that most manufacturers advise against breastfeeding, while some experts consider prescribed doses acceptable if the infant is watched for irritability, poor sleep and feeding problems; breastfeeding is generally discouraged during active amphetamine misuse. This is LactMed’s summary of published data, not FDA label content.
Availability and shortages
FDA SHORTAGE LISTED · BRAND AVAILABLE Lisdexamfetamine capsules and chewable tablets are listed as currently in shortage by the FDA. Brand Vyvanse is listed as available, while some generic manufacturers report limited supply.
If a generic is unavailable, ask the pharmacy to check other manufacturers or the brand.
FDA Drug Shortages (lisdexamfetamine capsule and chewable tablet, Currently in Shortage; first posted Jul 14, 2023): Takeda reverified Oct 15, 2026 with Vyvanse capsules 10–70 mg (NDC 59417-101 to -107) available. ASHP (updated Aug 28, 2026): Vyvanse available; Apotex, Hikma, Solco, and Sun limited. FDA capsule listing · FDA chewable listing · ASHP bulletin.
How Vyvanse compares to other amphetamine products
Vyvanse is one of several amphetamine-family options. Effect windows below come from each product’s FDA labeling (clinical study time points or dosing intervals), not head-to-head comparisons; amphetamine products are not interchangeable milligram for milligram.
| Medication | Studied effect window / dosing (label) | Release design | Key practical notes |
|---|---|---|---|
| Vyvanse (lisdexamfetamine) | Significant 2–12 h (children, Study 2); at each time point to 14 h (adults) | Prodrug converted to dextroamphetamine in blood | Capsule (open and mix) or chewable. AB generics; lisdexamfetamine on FDA shortage list, brand listed available. |
| Arynta (lisdexamfetamine solution) | Once daily; bridged from Vyvanse studies (2–12 h children; to 14 h adults) | Prodrug in oral solution, 10 mg/mL | Liquid Vyvanse alternative (505(b)(2)); discard 30 days after opening; no generic. |
| Adderall XR (beaded capsule) | Once daily; morning and afternoon improvement (pediatric study); Tmax ~7 h | Immediate- + delayed-release beads; 3:1 d:l | Sprinkle allowed. AB1 generics; generics on ASHP shortage list, brand listed available. |
| Mydayis (triple-bead capsule) | Significant from 2 or 4 h to 16 h post-dose | One immediate- + two delayed-release bead types; 3:1 d:l | Ages 13+ only. AB2 generics; ASHP lists brand available. |
| Xelstrym (dextroamphetamine patch) | Apply 2 h before effect needed; wear up to 9 h | Transdermal delivery | Brand only; Noven reports API-driven supply disruption; on ASHP shortage list. |
| Dyanavel XR (suspension / tablet) | Significant at every time point 1–13 h (suspension study) | Immediate + extended release (resin complex); 3.2:1 d:l | Liquid or chewable/swallowable tablet; brand only; ASHP lists available. |
Other amphetamine-family pages: Adderall, Adderall XR, Adzenys XR-ODT, Arynta, Desoxyn, Dexedrine Spansule, Dyanavel XR, Evekeo, Evekeo ODT, Mydayis, ProCentra, Xelstrym, Zenzedi.
Clinical evidence from published studies
These findings come from published research, not from the FDA label. The FDA label is the official source for approved uses, doses and warnings. Results from studies may not apply to you. Uses marked off-label are not FDA-approved. Talk with your prescriber before making any change.
Items summarize peer-reviewed publications, checked against the PubMed abstract (or full text where stated); figures are reproduced only where the source states them. The FDA label governs approved indications and dosing. Off-label items are not FDA-approved uses. Industry funding or sponsor affiliation is noted where the PubMed record shows it; absence of a note does not mean no industry involvement.
Studies of this medicine (13 studies)
-
Lisdexamfetamine (Vyvanse)
In a 13-hour classroom study of 117 children aged 6–12, lisdexamfetamine improved attention, behavior and math performance at every check from 1.5 to 13 hours after the dose.
Phase IIIb dose-optimised crossover: 117 randomised, 111 completed. SKAMP and PERMP significant at each time point 1.5–13.0 h (P<.005). Dose-optimisation AEs: decreased appetite 47%, insomnia 27%, headache 17%.
Wigal SB, Kollins SH, Childress AC, et al. (2009). A 13-hour laboratory school study of lisdexamfetamine dimesylate in school-aged children with attention-deficit/hyperactivity disorder. Child Adolesc Psychiatry Ment Health 3(1):17. DOI · PubMed 19508731
-
Lisdexamfetamine (Vyvanse), adults
In an adult simulated-workplace study, lisdexamfetamine improved performance compared with placebo from 2 to 14 hours after the dose.
Crossover: 127 randomised, 105 ITT, 103 completed. PERMP LSMD 23.4 (15.6–31.2); significant at all points 2–14 h. ADHD-RS-IV LSMD −11.5 (−14.2 to −8.9).
Wigal T, Brams M, Gasior M, et al. (2010). Randomized, double-blind, placebo-controlled, crossover study of the efficacy and safety of lisdexamfetamine dimesylate in adults with attention-deficit/hyperactivity disorder: novel findings using a simulated adult workplace environment design. Behav Brain Funct 6:34. DOI · PubMed 20576091
-
Lisdexamfetamine (Vyvanse)
In a classroom crossover study of 52 children aged 6–12, lisdexamfetamine improved attention, behavior and math performance compared with placebo, with side effects similar to Adderall XR.
Phase 2 crossover, n=52: LDX 30/50/70 mg vs placebo, MAS XR reference. SKAMP-D/A, PERMP and CGI-I improved; AEs similar for both actives.
Biederman J, Boellner SW, Childress A, et al. (2007). Lisdexamfetamine dimesylate and mixed amphetamine salts extended-release in children with ADHD: a double-blind, placebo-controlled, crossover analog classroom study. Biol Psychiatry 62(9):970-6. DOI · PubMed 17631866
-
Lisdexamfetamine vs placebo (OROS-MPH reference arm)
In a 7-week European trial of 336 children and teens, lisdexamfetamine reduced symptoms much more than placebo. Concerta-type OROS methylphenidate, included as a reference, also beat placebo.
Phase 3 RCT, n=336 (6–17 y), dose-optimised LDX 30–70 mg, OROS-MPH 18–54 mg, placebo. ADHD-RS-IV difference vs placebo: LDX −18.6 (−21.5 to −15.7; ES 1.80); OROS-MPH −13.0 (−15.9 to −10.2; ES 1.26). CGI-I improved: 78%, 61%, 14%. Not powered for LDX vs OROS comparison.
Coghill D, Banaschewski T, Lecendreux M, et al. (2013). European, randomized, phase 3 study of lisdexamfetamine dimesylate in children and adolescents with attention-deficit/hyperactivity disorder. Eur Neuropsychopharmacol 23(10):1208-18. DOI · PubMed 23332456
-
Lisdexamfetamine (Vyvanse)
In 18 children, blood levels of the active medicine (d-amphetamine) peaked about 3.5 hours after a lisdexamfetamine dose and rose in proportion to dose.
Pediatric PK, n=18 (6–12 y): d-amphetamine Cmax 53.2, 93.3, 134.0 ng/mL at 30/50/70 mg; Tmax ~3.5 h; AUC dose-proportional.
Boellner SW, Stark JG, Krishnan S, et al. (2010). Pharmacokinetics of lisdexamfetamine dimesylate and its active metabolite, d-amphetamine, with increasing oral doses of lisdexamfetamine dimesylate in children with attention-deficit/hyperactivity disorder: a single-dose, randomized, open-label, crossover study. Clin Ther 32(2):252-64. DOI · PubMed 20206783
-
Lisdexamfetamine (Vyvanse)
In a 2-year open-label study of 314 children and teens, side effects were common (mostly reduced appetite, weight loss and trouble sleeping, usually in the first 4–12 weeks) and led about 1 in 8 to stop. Serious psychiatric events were infrequent.
104-week open-label safety study, n=314 (191 completed). TEAEs 89.8%; discontinuation for TEAEs 12.4%; serious 8.9%. Related TEAEs: decreased appetite 49.4%, weight decrease 18.2%, insomnia 13.1%. Psychiatric: psychosis/mania n=1; suicidal ideation n=2, attempt n=1; aggression n=14.
Funding / affiliation: Funded by Shire Development LLC (manufacturer) per PubMed record.
Coghill DR, Banaschewski T, Nagy P, et al. (2017). Long-Term Safety and Efficacy of Lisdexamfetamine Dimesylate in Children and Adolescents with ADHD: A Phase IV, 2-Year, Open-Label Study in Europe. CNS Drugs 31(7):625-638. DOI · PubMed 28667569
-
Lisdexamfetamine in binge-eating disorder (FDA-approved for adults)
In two 12-week trials (383 and 390 adults with moderate to severe binge-eating disorder), lisdexamfetamine 50–70 mg reduced binge-eating days by about 1.3 to 1.7 more days per week than placebo.
Two pivotal RCTs (1:1, dose-optimised 50/70 mg). LSMD in binge days/week at wk 11–12: −1.35 (−1.70 to −1.01) and −1.66 (−2.04 to −1.28); both P<0.001. TEAEs ≥10%: dry mouth, insomnia, headache. Pulse +4.41–6.31 bpm.
Funding / affiliation: Authors affiliated with Shire (manufacturer) per PubMed record.
McElroy SL, Hudson J, Ferreira-Cornwell MC, et al. (2016). Lisdexamfetamine Dimesylate for Adults with Moderate to Severe Binge Eating Disorder: Results of Two Pivotal Phase 3 Randomized Controlled Trials. Neuropsychopharmacology 41(5):1251-60. DOI · PubMed 26346638
-
Lisdexamfetamine in binge-eating disorder (FDA-approved for adults)
Adults whose binge eating improved on lisdexamfetamine were much less likely to relapse over 6 months if they stayed on it (3.7%) than if switched to placebo (32.1%).
Randomised withdrawal: 275 responders (LDX 137, placebo 138). Relapse 3.7% (5/136) vs 32.1% (42/131); HR 0.09 (0.04–0.23).
Funding / affiliation: Industry: some authors employed by or consulting for Shire (manufacturer) per PubMed record.
Hudson JI, McElroy SL, Ferreira-Cornwell MC, et al. (2017). Efficacy of Lisdexamfetamine in Adults With Moderate to Severe Binge-Eating Disorder: A Randomized Clinical Trial. JAMA Psychiatry 74(9):903-910. DOI · PubMed 28700805
-
Lisdexamfetamine in binge-eating disorder
In a smaller independent maintenance trial, continuing lisdexamfetamine after a good response did not reduce binge-eating relapse compared with placebo (10.0% vs 17.9%, not significant), though it was linked to weight loss.
12-week maintenance RCT after acute response: relapse LDX 10.0% (3/30) vs placebo 17.9% (5/28); binge remission 59.4% vs 65.5%; no significant binge-eating difference. LDX −2.3% weight vs placebo +2.2%.
Grilo CM, Ivezaj V, Yurkow S, et al. (2024). Lisdexamfetamine maintenance treatment for binge-eating disorder following successful treatments: randomized double-blind placebo-controlled trial. Psychol Med 54(12):3334-3344. DOI · PubMed 39258475
-
Lisdexamfetamine in binge-eating disorder
In a trial comparing cognitive behavioral therapy (CBT), lisdexamfetamine, and both together, the combination worked best: 70% stopped binge eating with CBT plus lisdexamfetamine vs 45% with CBT alone and 40% with lisdexamfetamine alone.
RCT, CBT vs LDX vs CBT+LDX. ITT binge-eating remission: CBT+LDX 70.2%, CBT 44.7%, LDX 40.4%; CBT+LDX significantly outperformed both; CBT ≈ LDX. ≥5% weight loss: LDX 53.2%, CBT+LDX 42.6%, CBT 4.3%. Sample size not stated in the abstract (needs full-text check).
Grilo CM, Ivezaj V, Tek C, et al. (2025). Cognitive Behavioral Therapy and Lisdexamfetamine, Alone and Combined, for Binge-Eating Disorder With Obesity: A Randomized Controlled Trial. Am J Psychiatry 182(2):209-218. DOI · PubMed 39659158
-
Lisdexamfetamine in adolescents (13–17)
In a 4-week trial in 314 teenagers aged 13 to 17, all three lisdexamfetamine doses (30, 50 and 70 mg) reduced ADHD symptoms more than placebo from the first week. About 69% of teens on lisdexamfetamine were rated much or very much improved, compared with about 40% on placebo. Common side effects were less appetite, headache, trouble sleeping, weight loss and irritability.
Randomized, double-blind, placebo-controlled, 4-week forced-dose titration; N=314 randomized (309 in efficacy analyses); 49 withdrew (11 for TEAEs). LS mean change in ADHD-RS-IV at endpoint: −18.3, −21.1 and −20.7 (30, 50, 70 mg/day) vs −12.8 placebo (p ≤ .0056 each). CGI-I much/very much improved 69.1% (all doses) vs 39.5% (p < .0001). YQOL-R not significantly different. Small mean increases in pulse and blood pressure; no clinically meaningful ECG trends. NCT00735371.
Findling RL, Childress AC, Cutler AJ, et al. (2011). Efficacy and safety of lisdexamfetamine dimesylate in adolescents with attention-deficit/hyperactivity disorder. J Am Acad Child Adolesc Psychiatry 50(4):395-405. DOI · PubMed 21421179
-
Lisdexamfetamine in adults (18–55)
In a 4-week trial in 420 adults aged 18 to 55, each lisdexamfetamine dose (30, 50 and 70 mg) reduced ADHD symptoms more than placebo, starting in the first week, with no clear difference between doses. About 57% to 62% of adults on lisdexamfetamine were rated improved, compared with 29% on placebo. Side effects were mostly mild, such as dry mouth, less appetite and trouble sleeping.
Randomized, double-blind, placebo-controlled, 4 weeks; N=420 (30 mg 119, 50 mg 117, 70 mg 122, placebo 62); forced titration in the 50 and 70 mg arms. ADHD-RS change at endpoint: −16.2, −17.4, −18.6 vs −8.2 placebo (all p < .0001), no differences between doses. CGI-I ≤2: 57%, 62%, 61% vs 29% (all p < .01). Separation from placebo from week 1.
Adler LA, Goodman DW, Kollins SH, et al. (2008). Double-blind, placebo-controlled study of the efficacy and safety of lisdexamfetamine dimesylate in adults with attention-deficit/hyperactivity disorder. J Clin Psychiatry 69(9):1364-73. DOI · PubMed 19012818
-
Lisdexamfetamine vs immediate-release d-amphetamine (healthy adults)
In 24 healthy adults, a single 100 mg dose of lisdexamfetamine and 40 mg of immediate-release d-amphetamine (the same amount of active drug) produced the same peak blood level and total exposure, but lisdexamfetamine peaked about an hour later. Peak “drug liking” and “high” ratings, heart rate and blood pressure rises were similar. The authors concluded that the risk of misuse by mouth is likely similar. This does not cover snorting or injecting, which the label discusses separately.
Randomized, double-blind, placebo-controlled crossover; n=24 healthy subjects; equimolar d-amphetamine 40 mg vs lisdexamfetamine 100 mg. Amphetamine lag time 0.6 ± 0.6 h longer and Tmax 1.1 ± 1.5 h later after lisdexamfetamine; no differences in Cmax or AUC. No differences in peak abuse-related subjective effects (drug liking, high, stimulation) or peak cardiovascular effects. Single doses above the labeled maximum, in healthy volunteers. NCT02668926.
Dolder PC, Strajhar P, Vizeli P, et al. (2017). Pharmacokinetics and Pharmacodynamics of Lisdexamfetamine Compared with D-Amphetamine in Healthy Subjects. Front Pharmacol 8:617. DOI · PubMed 28936175
How ADHD medicines compare (16 studies)
-
Lisdexamfetamine vs OROS methylphenidate
A later analysis of that same European trial found lisdexamfetamine reduced symptoms more than OROS methylphenidate (the Concerta-type formulation). This was a post hoc comparison the trial was not designed for.
Post hoc analysis of Coghill 2013 (336 randomised; 317 full analysis set). ADHD-RS-IV LS mean change: LDX −24.3, OROS-MPH −18.7, placebo −5.7; LDX vs OROS −5.6 (−8.4 to −2.7; p<0.001). CGI-I improved difference 17.4% (NNT 6).
Soutullo C, Banaschewski T, Lecendreux M, et al. (2013). A post hoc comparison of the effects of lisdexamfetamine dimesylate and osmotic-release oral system methylphenidate on symptoms of attention-deficit hyperactivity disorder in children and adolescents. CNS Drugs 27(9):743-51. DOI · PubMed 23801529
-
Lisdexamfetamine vs OROS methylphenidate (adolescents)
In two adolescent trials comparing lisdexamfetamine and OROS methylphenidate directly, lisdexamfetamine was better in the fixed-dose trial but not in the flexible-dose trial.
Two 8-week RCTs (13–17 y). Forced-dose: LDX vs OROS-MPH −3.4 (p=0.0013; ES −0.33); flexible-dose: −2.1 (p=0.0717; ES −0.20). CGI-I improved: 81.4% vs 71.3% (forced, p=0.0188); 83.1% vs 81.0% (flexible, NS).
Funding / affiliation: Funded by Shire Development LLC (lisdexamfetamine manufacturer) per PubMed record.
Newcorn JH, Nagy P, Childress AC, et al. (2017). Randomized, Double-Blind, Placebo-Controlled Acute Comparator Trials of Lisdexamfetamine and Extended-Release Methylphenidate in Adolescents With Attention-Deficit/Hyperactivity Disorder. CNS Drugs 31(11):999-1014. DOI · PubMed 28980198
-
Lisdexamfetamine vs atomoxetine
In a 9-week head-to-head trial of 267 children and teens who had not done well on methylphenidate, lisdexamfetamine worked faster and reduced symptoms more than atomoxetine. Response by week 9 was 82% vs 64%.
Head-to-head RCT, n=267 (LDX 133, ATX 134). Median time to response 12.0 vs 21.0 days (p=0.001); week-9 response 81.7% vs 63.6%; ADHD-RS-IV difference −6.5 (−9.3 to −3.6; ES 0.56). TEAEs 71.9% vs 70.9%. Companion analysis (PMID 25038977): ≥30% reduction 88.1% vs 73.7%.
Dittmann RW, Cardo E, Nagy P, et al. (2013). Efficacy and safety of lisdexamfetamine dimesylate and atomoxetine in the treatment of attention-deficit/hyperactivity disorder: a head-to-head, randomized, double-blind, phase IIIb study. CNS Drugs 27(12):1081-92. DOI · PubMed 23959815
See also: Dittmann RW, Cardo E, Nagy P, et al. (2014). CNS Drugs. DOI · PubMed 25038977
-
Stimulants in adults (class)
Pooling 20 adult trials, lisdexamfetamine showed the largest average effect versus placebo, with mixed amphetamine salts and methylphenidate showing moderate effects. These comparisons are indirect.
Meta-analysis of 20 double-blind placebo-controlled parallel-group adult RCTs. SMD vs placebo: lisdexamfetamine −0.89 (−1.09 to −0.70), mixed amphetamine salts −0.64 (−0.83 to −0.45), methylphenidate −0.50 (−0.58 to −0.41); modafinil 0.08 (NS).
Stuhec M, Lukić P, Locatelli I (2019). Efficacy, Acceptability, and Tolerability of Lisdexamfetamine, Mixed Amphetamine Salts, Methylphenidate, and Modafinil in the Treatment of Attention-Deficit Hyperactivity Disorder in Adults: A Systematic Review and Meta-analysis. Ann Pharmacother 53(2):121-133. DOI · PubMed 30117329
-
ADHD medicines in children (class)
An industry-funded network analysis of 36 trials ranked placebo-adjusted symptom improvement as largest for lisdexamfetamine, then extended-release methylphenidate, then guanfacine ER, then atomoxetine. These are indirect comparisons.
Bayesian NMA of 36 RCTs (6–17 y). ADHD-RS-IV change vs placebo: lisdexamfetamine −14.98 (95% CrI −17.14 to −12.80), MPH ER −9.33 (−11.63 to −7.04), guanfacine ER −8.68 (−10.63 to −6.72), atomoxetine −6.88 (−8.22 to −5.49).
Funding / affiliation: Authors affiliated with Shire (guanfacine ER and lisdexamfetamine manufacturer) per PubMed record.
Joseph A, Ayyagari R, Xie M, et al. (2017). Comparative efficacy and safety of attention-deficit/hyperactivity disorder pharmacotherapies, including guanfacine extended release: a mixed treatment comparison. Eur Child Adolesc Psychiatry 26(8):875-897. DOI · PubMed 28258319
-
Long-acting stimulants (class)
A review of 15 classroom-style trials found that long-acting stimulants kept working for about 8 hours (some long-acting methylphenidate products) up to 14 hours (lisdexamfetamine) after one morning dose, with most lasting about 12 hours. Most studies stopped measuring at 12 hours, and the products were not compared head to head.
Systematic literature review (PubMed, BIOSYS, EMBASE to June 2009) of analog-classroom trials using PERMP; 15 trials (all pediatric except one adult). Duration of efficacy vs placebo ranged from 8 h (long-acting MPH) to 14 h (lisdexamfetamine); most formulations ~12 h. Limits: observation mostly ended at 12 h; cross-study comparisons; non-equivalent doses. Short-acting, nonoral and nonstimulant products excluded.
Brams M, Moon E, Pucci M, et al. (2010). Duration of effect of oral long-acting stimulant medications for ADHD throughout the day. Curr Med Res Opin 26(8):1809-25. DOI · PubMed 20491612
-
ADHD medicines (class)
A large analysis of 133 short-term trials found that every ADHD medicine studied worked better than placebo on clinician ratings in children and teens. Amphetamines had the largest average effect, and methylphenidate was the only medicine also shown to beat placebo on teacher ratings. Amphetamines and guanfacine led to more stopping for side effects than placebo in children. Weighing benefit and side effects, the authors favored methylphenidate first in children and amphetamines first in adults. There was too little data to judge effects beyond about 12 weeks.
Network meta-analysis of 133 double-blind RCTs (efficacy near 12 wk: 10,068 children/adolescents; 8,131 adults). Children, clinician-rated SMD vs placebo: amphetamines −1.02 (95% CI −1.19 to −0.85), methylphenidate −0.78 (−0.93 to −0.62), atomoxetine −0.56 (−0.66 to −0.45). Teacher-rated: only methylphenidate (−0.82, −1.16 to −0.48) and modafinil separated from placebo. Adults, clinician-rated: amphetamines −0.79 (−0.99 to −0.58), methylphenidate −0.49 (−0.64 to −0.35), atomoxetine −0.45 (−0.58 to −0.32). Discontinuation for adverse events vs placebo: amphetamines OR 2.30 (1.36–3.89) in children and 3.26 (1.54–6.92) in adults; guanfacine 2.64 (1.20–5.81) in children; atomoxetine 2.33 (1.28–4.25) and methylphenidate 2.39 (1.40–4.08) in adults only. Head-to-head clinician-rated efficacy favored amphetamines over methylphenidate, atomoxetine and modafinil. Insufficient data at 26 and 52 weeks.
Funding / affiliation: Non-industry (Stichting Eunethydis; UK NIHR Oxford Health BRC).
Cortese S, Adamo N, Del Giovane C, et al. (2018). Comparative efficacy and tolerability of medications for attention-deficit hyperactivity disorder in children, adolescents, and adults: a systematic review and network meta-analysis. Lancet Psychiatry 5(9):727-738. DOI · PubMed 30097390
-
ADHD treatments in children and teens (class)
Across 190 trials in children and teens, methylphenidate, amphetamine, atomoxetine, guanfacine and clonidine all worked better than placebo. Methylphenidate and amphetamine appeared more effective than atomoxetine and guanfacine. Behavioral therapy combined with a stimulant appeared better than either medicine type alone. Most effective medicines also caused harms such as reduced appetite, weight loss and sleep problems.
Bayesian network meta-analyses of 190 RCTs (52 interventions, 26,114 participants; ≥3 weeks follow-up). Medications more efficacious than placebo: methylphenidate, amphetamine, atomoxetine, guanfacine, clonidine. Methylphenidate and amphetamine more efficacious than atomoxetine and guanfacine; methylphenidate and clonidine better accepted (all-cause discontinuation) than placebo and atomoxetine. Behavioural therapy plus stimulants appeared superior to stimulants or nonstimulants alone. Harms included anorexia, weight loss and insomnia. Results expressed as ORs with credible intervals (not reproduced here).
Catalá-López F, Hutton B, Núñez-Beltrán A, et al. (2017). The pharmacological and non-pharmacological treatment of attention deficit hyperactivity disorder in children and adolescents: A systematic review with network meta-analyses of randomised trials. PLoS One 12(7):e0180355. DOI · PubMed 28700715
-
ADHD medicines (class): dose
An analysis of how benefit changes with dose (113 trials) found that, in children and teens, extra benefit stopped rising above about 45 mg/day of methylphenidate, 25 mg/day of amphetamines and 4 mg/day of guanfacine, although data at higher doses were thin. Stopping for side effects rose at higher amphetamine doses, and at methylphenidate doses above 50 mg/day in adults. No dose–benefit pattern was found for atomoxetine in fixed-dose studies.
Dose-effect NMA (Bayesian restricted cubic splines) of 113 double-blind RCTs: 68 pediatric (14,138 participants), 45 adult (11,016). Children/adolescents: median efficacy increased up to ~45 mg/day methylphenidate, ~25 mg/day amphetamines, ~4 mg/day guanfacine, with no evidence of added benefit above (wide credible intervals). Adults: amphetamines plateaued above ~50 mg/day; methylphenidate showed no plateau (sparse data). Dose-dependent AE-related discontinuation: amphetamines above 25 mg/day (children) and 50 mg/day (adults); methylphenidate above 50 mg/day in adults, no clear dose dependence in children. No dose-effect pattern for atomoxetine (fixed-dose studies) or modafinil. Needs full-text check: how amphetamine products were converted to a common dose scale is not stated in the abstract.
Funding / affiliation: Non-industry (UK NIHR).
Nourredine M, Jurek L, Hamza T, et al. (2026). Pharmacological interventions for ADHD: a systematic review and dose-effect network meta-analysis. Lancet Psychiatry 13(6):485-495. DOI · PubMed 42134365
-
Amphetamines vs methylphenidate (class)
A pooled analysis of 23 placebo-controlled trials in children and teens found that amphetamine products had somewhat larger average effects than methylphenidate products, even after adjusting for differences in study design. The trials did not compare the two directly.
Meta-analysis/meta-regression of 23 double-blind placebo-controlled trials (11 drugs, 19 outcome measures). Effect sizes for amphetamine products were significantly, though moderately, greater than for methylphenidate products after correcting for design features. Indirect comparison (no head-to-head trials).
Faraone SV, Buitelaar J (2010). Comparing the efficacy of stimulants for ADHD in children and adolescents using meta-analysis. Eur Child Adolesc Psychiatry 19(4):353-64. DOI · PubMed 19763664
-
Adult ADHD treatments (class)
In adults (113 trials), stimulants and atomoxetine were the only treatments that reduced core symptoms on both self-ratings and clinician ratings at 12 weeks. Several psychological approaches (such as CBT and mindfulness) helped only on clinician ratings. Atomoxetine and guanfacine were stopped more often than placebo.
Component NMA, 113 RCTs (14,887 adults). 12-week core symptoms: atomoxetine SMD −0.38 self-rated (−0.56 to −0.21), −0.51 clinician-rated (−0.64 to −0.37); stimulants about −0.39 self-rated (CI −0.52 to −0.26) and −0.61 clinician-rated (−0.71 to −0.51). CBT (−0.76), cognitive remediation, mindfulness, psychoeducation and tDCS beat placebo on clinician-rated measures only. Acceptability worse than placebo: atomoxetine OR 1.43 (1.14–1.80), guanfacine 3.70 (1.22–11.19).
Ostinelli EG, Schulze M, Zangani C, et al. (2025). Comparative efficacy and acceptability of pharmacological, psychological, and neurostimulatory interventions for ADHD in adults: a systematic review and component network meta-analysis. Lancet Psychiatry 12(1):32-43. DOI · PubMed 39701638
-
Amphetamines in adults (Cochrane review)
A Cochrane review of 19 short trials in 2,521 adults found that amphetamines reduced ADHD symptoms compared with placebo but did not keep more people in treatment, and more people stopped because of side effects. Lisdexamfetamine and mixed amphetamine salts each reduced clinician-rated symptoms; the one small dextroamphetamine trial did not show a clear effect. The reviewers rated the evidence low or very low quality; 16 of the 19 studies were industry funded.
Cochrane systematic review (searches to Aug 2017): 19 RCTs, N=2,521 adults, mean study length 5.3 weeks. Clinician-rated severity: amphetamines SMD −0.90 (95% CI −1.04 to −0.75; 13 studies, 2,028; low to very low quality). By type: lisdexamfetamine −1.06 (−1.26 to −0.85; 7 studies, 896), MAS −0.80 (−0.93 to −0.66; 5 studies, 1,083), dexamphetamine −0.24 (−0.80 to 0.32; 1 study, 49; very low). Retention RR 1.06 (0.99–1.13); withdrawal for adverse events RR 2.69 (1.63–4.45). No dose–response or IR vs ER difference. 16 industry funded, 1 public, 2 not reported; none at low risk of bias in all domains.
Funding / affiliation: 16 of the 19 included trials were funded by the pharmaceutical industry (1 publicly funded, 2 not reported).
Castells X, Blanco-Silvente L, Cunill R (2018). Amphetamines for attention deficit hyperactivity disorder (ADHD) in adults. Cochrane Database Syst Rev 8(8):CD007813. DOI · PubMed 30091808
-
Amphetamines in children and adolescents (Cochrane review)
A Cochrane review of 23 short-term trials in 2,675 children and teens aged 3 to 17 found that amphetamines reduced ADHD symptoms compared with placebo, as rated by parents, teachers and clinicians, and about three times as many children were rated as responders. Appetite loss, trouble sleeping and stomach pain were more common. The reviewers rated the evidence low to very low quality and found no evidence favoring one amphetamine product over another, or long-acting over short-acting forms.
Cochrane systematic review (searches to Aug 2015): 23 RCTs (8 parallel, 15 crossover), N=2,675, ages 3–17, all placebo-controlled. Parent-rated SMD −0.57 (95% CI −0.86 to −0.27; very low quality); teacher −0.55 (−0.83 to −0.27; low); clinician −0.84 (−1.32 to −0.36; very low). CGI-I responders RR 3.36 (2.48–4.55; 9 studies, 2,207; very low). Decreased appetite RR 6.31 (2.58–15.46); insomnia RR 3.80 (2.12–6.83); abdominal pain RR 1.44 (1.03–2.00). 11 studies high risk of bias, 12 unclear. No difference between amphetamine preparations or release formulations.
Punja S, Shamseer L, Hartling L, et al. (2016). Amphetamines for attention deficit hyperactivity disorder (ADHD) in children and adolescents. Cochrane Database Syst Rev 2(2):CD009996. DOI · PubMed 26844979
-
Stimulant dose and dosing strategy in children and adolescents
Pooling 65 trials in 7,877 children and teens, higher stimulant doses brought more symptom improvement but also more stopping because of side effects in fixed-dose trials, and the added benefit got smaller above about 20 mg a day of amphetamine (30 mg of methylphenidate). In trials where doses were adjusted to each child, benefit kept rising across the FDA-approved dose range without more dropouts. The authors favor adjusting the dose to response and side effects.
Dose-response meta-analysis, 65 RCTs, n=7,877 children/adolescents; MPH and AMP analysed separately (doses converted to MPH- or AMP-equivalents); fixed-dose and flexible-dose trials stratified. Fixed-dose: efficacy and AE-related discontinuation both increased with dose; incremental efficacy decreased beyond 30 mg MPH or 20 mg AMP. Flexible-dose: efficacy increased and all-cause discontinuation decreased with dose; incremental benefit constant across the FDA-licensed range. Group-level estimates; long-term effects of high doses not addressed.
Farhat LC, Flores JM, Behling E, et al. (2022). The effects of stimulant dose and dosing strategy on treatment outcomes in attention-deficit/hyperactivity disorder in children and adolescents: a meta-analysis. Mol Psychiatry 27(3):1562-1572. DOI · PubMed 35027679
-
Trying both dextroamphetamine and methylphenidate (children 9–14)
In a small crossover trial, 36 children aged 9 to 14 who had never taken ADHD medicine each tried methylphenidate, dextroamphetamine and placebo for 2 weeks apiece. Each stimulant worked well for 26 children (72%), but many children responded differently to the two. Trying both raised the number with a good response from 26 to 33 (92%).
Randomized, counterbalanced crossover (2 weeks each of methylphenidate, dextroamphetamine and placebo); n=36 medication-naive children aged 9–14. Outcomes: QbTest and parent/teacher ADHD questionnaire. Group effects similar for both stimulants; each produced a favourable response in 26 children; including both increased favourable responders from 26 (72%) to 33 (92%). Shifting from the inferior to the best drug increased overall response strength by 64% (mean). NCT01220440.
Ramtvedt BE, Røinås E, Aabech HS, et al. (2013). Clinical gains from including both dextroamphetamine and methylphenidate in stimulant trials. J Child Adolesc Psychopharmacol 23(9):597-604. DOI · PubMed 23659360
-
Switching stimulant family in adults starting treatment
In a clinic study of 49 adults starting their first stimulant, 41% needed to switch to the other stimulant family (methylphenidate to amphetamine or the reverse) within 90 days because of side effects. Switching was more common after starting methylphenidate. Baseline features did not predict who would need to switch.
Naturalistic clinical cohort; n=49 medication-naive adults aged 18–45 with DSM-5 ADHD; 67% started a methylphenidate product, 33% an amphetamine product. 41% switched stimulant family within 90 days because of poor tolerability; switching rate higher with initial methylphenidate; formulation changes or added anxiety/depression treatment more frequent with amphetamine. Switching not adequately predicted by baseline characteristics. Small, single-site.
Biederman J, DiSalvo M, Green A, et al. (2021). How Frequent Is Switching From an Initial Stimulant Family to the Alternative One in the Clinical Setting?: A Pilot Study of 49 Consecutively Referred Medication-Naive Adults With Attention-Deficit/Hyperactivity Disorder. J Clin Psychopharmacol 41(3):310-314. DOI · PubMed 33657069
Long-term real-world outcomes (8 studies)
-
Specific ADHD medicines in adolescents and adults (Sweden)
In 221,714 Swedish adolescents and adults with ADHD followed for about 7 years, periods on amphetamine, lisdexamfetamine, dexamphetamine or methylphenidate were linked to fewer psychiatric hospital stays than periods off medicine in the same people. Lisdexamfetamine, dexamphetamine and methylphenidate periods were also linked to less suicidal behavior. Only atomoxetine was linked to less work disability. Observational: an association, not proof.
Nationwide register cohort, Sweden 2006–2021, ages 16–65, n=221,714 (methylphenidate users 151,837; lisdexamphetamine 78,106); within-individual stratified Cox models, mean follow-up 7.0 y. Psychiatric hospitalization aHR: amphetamine 0.74 (95% CI 0.61–0.90), lisdexamphetamine 0.80 (0.78–0.82), dexamphetamine 0.88 (0.83–0.94), methylphenidate 0.93 (0.92–0.95); no association for modafinil, atomoxetine, clonidine, guanfacine. Suicidal behaviour aHR: dexamphetamine 0.69 (0.53–0.89), lisdexamphetamine 0.76 (0.68–0.84), methylphenidate 0.92 (0.86–0.98). Work disability: atomoxetine only, 0.89 (0.82–0.97).
Taipale H, Bergström J, Gèmes K, et al. (2024). Attention-Deficit/Hyperactivity Disorder Medications and Work Disability and Mental Health Outcomes. JAMA Netw Open 7(3):e242859. DOI · PubMed 38506810
-
ADHD medicines (class): criminal convictions
Comparing the same 25,656 people with ADHD in Sweden during periods on and off medicine (2006–2009), criminal convictions were 32% lower in men and 41% lower in women while they were taking ADHD medicine. This links treatment with fewer crimes but cannot prove the medicine caused the drop.
This study looked at ADHD medicines as a group; the abstract does not report amphetamine products separately.
Swedish registers 2006–2009, n=25,656; stratified (within-individual) Cox regression, medicated vs non-medicated periods. Criminality: men adjusted HR 0.68 (95% CI 0.63–0.73); women HR 0.59 (0.50–0.70). Reductions of 17% to 46% in male sensitivity analyses (including by drug type, stimulant vs nonstimulant, and type of crime). Class-level estimate.
Funding / affiliation: Non-industry (Swedish Research Council and others).
Lichtenstein P, Halldner L, Zetterqvist J, et al. (2012). Medication for attention deficit-hyperactivity disorder and criminality. N Engl J Med 367(21):2006-14. DOI · PubMed 23171097
-
ADHD medicines (class): risk of death
In a Swedish national study of 148,578 people aged 6 to 64 newly diagnosed with ADHD, those who started ADHD medicine had a lower risk of dying over the next 2 years (39 vs 48 deaths per 10,000 people). The difference came mainly from fewer deaths from unnatural causes such as injuries, accidental poisonings and suicide; deaths from natural causes did not differ significantly. This is an observational study: it shows an association, not proof that the medicine caused the difference.
This study looked at ADHD medicines as a group; the abstract does not report amphetamine products separately.
Target trial emulation, Swedish registers (diagnosis 2007–2018; 2-year follow-up); n=148,578, of whom 84,204 (56.7%) started medication within 3 months. 2-year mortality 39.1 vs 48.1 per 10,000 (risk difference −8.9; 95% CI −17.3 to −0.6). All-cause HR 0.79 (0.70–0.88); unnatural-cause HR 0.75 (0.66–0.86); natural-cause HR 0.86 (0.71–1.05), not significant. Class-level estimate (all ADHD medicines); the abstract does not report methylphenidate separately.
Li L, Zhu N, Zhang L, et al. (2024). ADHD Pharmacotherapy and Mortality in Individuals With ADHD. JAMA 331(10):850-860. DOI · PubMed 38470385
-
ADHD medicines (class; 88% started on methylphenidate)
Using the same Swedish registers (148,581 people aged 6 to 64 newly diagnosed with ADHD), starting ADHD medicine was linked over 2 years to fewer first episodes of suicidal behavior (about 17% fewer), substance misuse (15%), transport accidents (12%) and criminal offenses (13%). Accidental injuries were not significantly reduced for first events, but repeat events of all five kinds were lower. Methylphenidate was the first medicine for 88% of people who started treatment. Observational: an association, not proof.
This study looked at ADHD medicines as a group; the abstract does not report amphetamine products separately.
Target trial emulation, Swedish registers 2007–2020; n=148,581; 84,282 (56.7%) initiated treatment, methylphenidate in 74,515 (88.4%). First events, adjusted IRR: suicidal behaviour 0.83 (95% CI 0.78–0.88); substance misuse 0.85 (0.83–0.87); transport accidents 0.88 (0.82–0.94); criminality 0.87 (0.83–0.90); accidental injuries 0.98 (0.96–1.01), not significant. Recurrent events: all five reduced (IRR 0.75–0.96). Class-level estimates.
Zhang L, Zhu N, Sjölander A, et al. (2025). ADHD drug treatment and risk of suicidal behaviours, substance misuse, accidental injuries, transport accidents, and criminality: emulation of target trials. BMJ 390:e083658. DOI · PubMed 40803836
-
ADHD medicines (class): changes over time
A Swedish study of 247,420 people who used ADHD medicine between 2006 and 2020 compared periods on and off medicine in the same people. Medicine periods were consistently linked to fewer self-harm events, unintentional injuries, traffic crashes and crimes. However, the links for injuries, crashes and crime became weaker over time as the share of people taking ADHD medicine rose from 0.6% to 2.8%.
This study looked at ADHD medicines as a group; the abstract does not report amphetamine products separately.
Self-controlled case series, Swedish registers, ages 4–64, n=247,420; periods 2006–2010, 2011–2015 and 2016–2020 (medication prevalence 0.6% to 2.8%). Medicated vs non-medicated IRR ranges: self-harm 0.77 (0.73–0.81) to 0.85 (0.82–0.88); unintentional injury 0.87 (0.84–0.89) to 0.93 (0.91–0.95); traffic crashes 0.71 (0.67–0.77) to 0.87 (0.83–0.91); crime 0.73 (0.71–0.75) to 0.84 (0.82–0.85). Weakening over time for injury, crashes and crime (P for trend <.01), not fully explained by changes in age and sex mix.
Li L, Coghill D, Sjölander A, et al. (2025). Increased Prescribing of Attention-Deficit/Hyperactivity Disorder Medication and Real-World Outcomes Over Time. JAMA Psychiatry 82(8):830-837. DOI · PubMed 40560574
-
ADHD medicines (class): motor vehicle crashes (US)
In US insurance claims for about 2.3 million people with ADHD, emergency visits for car crashes were 38% lower in men and 42% lower in women during months when they were taking ADHD medicine than in months when they were not. Observational: an association, not proof that the medicine caused the difference.
This study looked at ADHD medicines as a group; the abstract does not report amphetamine products separately.
US commercial claims 2005–2014, n=2,319,450 (mean age 32.5; 51.7% female); within-individual comparison of medicated vs unmedicated months. ED visits for MVCs: men OR 0.62 (95% CI 0.56–0.67), women OR 0.58 (0.53–0.62); similar across age groups and sensitivity analyses. Population-attributable fraction up to 22.1% (modelled). Class-level estimate.
Chang Z, Quinn PD, Hur K, et al. (2017). Association Between Medication Use for Attention-Deficit/Hyperactivity Disorder and Risk of Motor Vehicle Crashes. JAMA Psychiatry 74(6):597-603. DOI · PubMed 28492937
-
ADHD medicines (class): substance-related emergencies (US)
In US insurance claims for almost 3 million teens and adults with ADHD, emergency visits related to substance use were about a third lower during months on ADHD medicine than months off it, and somewhat lower 2 years later in men. This does not support the worry that treatment raises later substance problems, though it cannot prove cause.
This study looked at ADHD medicines as a group; the abstract does not report amphetamine products separately.
US commercial claims 2005–2014, n=2,993,887 adolescents and adults (47.2% female); within-individual analyses of stimulant or atomoxetine treatment months. Concurrent substance-related ED visits: men OR 0.65 (95% CI 0.64–0.67), women 0.69 (0.67–0.71). Two years after medication periods: men 0.81 (0.78–0.85), women 0.86 (0.82–0.91); long-term results less consistent in women. Class-level estimate.
Quinn PD, Chang Z, Hur K, et al. (2017). ADHD Medication and Substance-Related Problems. Am J Psychiatry 174(9):877-885. DOI · PubMed 28659039
-
ADHD medicines (class): suicidal behavior (Sweden)
In 37,936 Swedish patients with ADHD followed from 2006 to 2009, comparing the same people on and off treatment, periods on stimulant medicine were linked to fewer suicide attempts and suicides. At the population level, treated people had more events, which reflects who gets treated rather than an effect of the medicine.
This study looked at ADHD medicines as a group; the abstract does not report amphetamine products separately.
Swedish registers, n=37,936, 2006–2009; 7,019 suicide-related events in 150,721 person-years. Population-level HR 1.31 (95% CI 1.19–1.44); within-patient HR 0.89 (0.79–1.00); stimulant users within-patient 0.81 (0.70–0.94); non-stimulant/mixed 0.96 (0.72–1.30). Class-level estimate.
Chen Q, Sjölander A, Runeson B, et al. (2014). Drug treatment for attention-deficit/hyperactivity disorder and suicidal behaviour: register based study. BMJ 348:g3769. DOI · PubMed 24942388
Heart and blood pressure (9 studies)
-
Methylphenidate, amphetamines, atomoxetine (children)
Pooling 18 trials in 5,837 children and teens, methylphenidate, amphetamines and atomoxetine all raised systolic blood pressure slightly on average. Amphetamines and atomoxetine also raised heart rate and diastolic pressure; methylphenidate did not. About 2% stopped because of heart-related effects. The authors advise regular heart rate and blood pressure checks.
Systematic review/meta-analysis, 18 trials (10 MPH, 5 AMP, 7 ATX), n=5,837, mean 28.7 weeks. Pre–post SBP SMD: MPH 0.25 (0.08–0.42), AMP 0.09 (0.03–0.15), ATX 0.16 (0.04–0.27). DBP: AMP 0.16 (0.03–0.29), ATX 0.22 (0.10–0.34); HR: AMP 0.37 (0.13–0.60), ATX 0.43 (0.26–0.60); MPH no pre–post effect on DBP or HR. No significant head-to-head differences. 2% discontinued for any cardiovascular effect.
Hennissen L, Bakker MJ, Banaschewski T, et al. (2017). Cardiovascular Effects of Stimulant and Non-Stimulant Medication for Children and Adolescents with ADHD: A Systematic Review and Meta-Analysis of Trials of Methylphenidate, Amphetamines and Atomoxetine. CNS Drugs 31(3):199-215. DOI · PubMed 28236285
-
ADHD medicines (class)
Pooling 102 short-term trials, most ADHD medicines raised blood pressure and pulse modestly, and stimulants did not raise them more than atomoxetine or viloxazine. Guanfacine lowered blood pressure and pulse. The authors advise monitoring blood pressure and pulse with any ADHD medicine, not just stimulants.
NMA of 102 RCTs (13,315 children/adolescents; 9,387 adults; median 7 weeks). Children, mean increase vs placebo: SBP 1.07 (atomoxetine) to 1.81 mm Hg (methylphenidate); DBP 1.93 (amphetamines) to 2.42 (methylphenidate); pulse 2.79 bpm (viloxazine) to 5.58 bpm (atomoxetine). Amphetamines, lisdexamfetamine and methylphenidate not associated with larger increments than atomoxetine or viloxazine. Guanfacine in children: SBP −2.83 (−3.8 to −1.85), DBP −2.08, pulse −4.06. Only four RCTs informed medium-term effects. CINeMA confidence mostly low to moderate in children, very low in adults.
Funding / affiliation: Non-industry (UK NIHR).
Farhat LC, Lannes A, Del Giovane C, et al. (2025). Comparative cardiovascular safety of medications for attention-deficit hyperactivity disorder in children, adolescents, and adults: a systematic review and network meta-analysis. Lancet Psychiatry 12(5):355-365. DOI · PubMed 40203844
-
ADHD medicines (class), long-term use
In a Swedish registry study of 278,027 people with ADHD (ages 6–64), longer total use of ADHD medicine was linked to a higher risk of cardiovascular disease, about 4% more per year of use, mainly high blood pressure and arterial disease. This kind of study shows an association, not proof of cause.
Nested case-control (Swedish registers, 2007–2020): 10,388 CVD cases vs 51,672 matched controls. Cumulative use vs non-use: 3–≤5 y AOR 1.27 (1.17–1.39); >5 y 1.23 (1.12–1.36). Per year of use AOR 1.04 (1.03–1.05), steeper in first 3 years (1.08). Hypertension 3–≤5 y AOR 1.72 (1.51–1.97), >5 y 1.80 (1.55–2.08). Similar in under-25s and adults. Not broken down by individual drug in the abstract.
Zhang L, Li L, Andell P, et al. (2024). Attention-Deficit/Hyperactivity Disorder Medications and Long-Term Risk of Cardiovascular Diseases. JAMA Psychiatry 81(2):178-187. DOI · PubMed 37991787
-
Stimulants and nonstimulants (children and teens)
The 2019 American Academy of Pediatrics guideline says stimulants have not been shown to raise the risk of sudden death. Before starting, clinicians should ask about heart symptoms and a family history of sudden death or inherited heart rhythm or muscle conditions, and arrange further evaluation if any risk factor is present. It describes an ECG as part of that extra evaluation for nonstimulants when risk factors are present.
AAP clinical practice guideline (Wolraich 2019), full text: obtain history of specific cardiac symptoms and family history of sudden death, cardiovascular symptoms, WPW, HCM and long QT before stimulants; if risk factors are present, obtain additional evaluation. For nonstimulants with risk factors, the additional evaluation is described as an ECG, with pediatric cardiology referral if abnormal. No routine ECG is recommended for patients without risk factors.
Wolraich ML, Hagan JF Jr, Allan C, et al. (2019). Clinical Practice Guideline for the Diagnosis, Evaluation, and Treatment of Attention-Deficit/Hyperactivity Disorder in Children and Adolescents. Pediatrics 144(4). DOI · PubMed 31570648
-
ADHD medicines (class)
The European ADHD Guidelines Group found no evidence that a routine ECG before starting ADHD medicine adds benefit. It notes that the American Heart Association first suggested an ECG as standard in 2008 and then left it to the clinician’s judgment. A 2009 Canadian joint statement likewise recommends a careful history and examination, with an ECG or cardiology referral only when these suggest a problem.
European Guidelines Group (EUNETHYDIS) review of adverse effects, full text: “no current evidence to suggest an incremental benefit for routine ECG assessment” before medication; AHA in 2008 initially recommended ECG as standard, then changed this to clinician discretion; ECG screening not considered cost-effective for preventing sudden death in the general pediatric population. Canadian Paediatric Society / Canadian Cardiovascular Society / CACAP joint statement (Warren 2009, abstract): thorough history and physical examination; no routine ECG screening or cardiac subspecialist consultation unless indicated by history or examination.
Graham J, Banaschewski T, Buitelaar J, et al. (2011). European guidelines on managing adverse effects of medication for ADHD. Eur Child Adolesc Psychiatry 20(1):17-37. DOI · PubMed 21042924
See also: Warren AE, Hamilton RM, Bélanger SA, et al. (2009). Can J Cardiol. DOI · PubMed 19898693
-
Children with ADHD (screening ECG)
At one U.S. center, 1,470 children with ADHD had a screening ECG. About 8% were read as abnormal, but heart disease was found in only 5 children (0.3%), so most abnormal results were false alarms. Finding each true case cost about $17,000 in testing.
Retrospective review of screening ECGs in 1,470 patients <21 y with ADHD (Apr–Sep 2008): 119 abnormal (8.1%); follow-up included 63 echocardiograms, 5 stress tests, 9 Holters; cardiac disease in 5 (0.3%: ventricular pre-excitation 2, bicuspid aortic valve 2, secundum ASD 1); positive predictive value 4.2%; mean cost $58 per child and $17,162 per true positive. The authors note screening can find asymptomatic disease but with low PPV.
Mahle WT, Hebson C, Strieper MJ (2009). Electrocardiographic screening in children with attention-deficit hyperactivity disorder. Am J Cardiol 104(9):1296-9. DOI · PubMed 19840580
-
ADHD medicines (class): new heart failure or cardiomyopathy (FDA Sentinel)
Among about 2 million people starting amphetamine products (including lisdexamfetamine), methylphenidate or atomoxetine in the FDA Sentinel database, new heart failure or cardiomyopathy was uncommon under age 45 (fewer than 50 cases per 10,000 person-years) and did not rise with longer use. Rates were highest in people 65 and older soon after starting, which may reflect existing heart risk.
FDA Sentinel distributed database; 2,012,948 initiators of amphetamine products (incl. lisdexamfetamine), methylphenidate or atomoxetine (44.6% female; 54.1% <22 y). Heart failure/cardiomyopathy <50 per 10,000 person-years in ages <22 and 22–44, without trend by duration of use (up to 1,095 days). Highest rate in ≥65 y in days 0–90 (950 per 10,000 person-years). No comparison group.
Mosholder AD, Taylor L, Mannheim G, et al. (2018). Incidence of Heart Failure and Cardiomyopathy Following Initiation of Medications for Attention-Deficit/Hyperactivity Disorder: A Descriptive Study. J Clin Psychopharmacol 38(5):505-508. DOI · PubMed 30102629
-
ADHD medicines (class): serious heart events in children and young adults
In US health-plan records for 1.2 million children and young adults aged 2 to 24, current use of ADHD medicine was not linked to more sudden cardiac death, heart attack or stroke. Such events were rare (3 per 100,000 person-years). The study could not rule out a small increase, but any extra risk in absolute terms would be low.
This study looked at ADHD medicines as a group; the abstract does not report amphetamine products separately.
Retrospective cohort, 4 US health plans; 1,200,438 aged 2–24 y, 2,579,104 person-years (373,667 current use). 81 serious cardiovascular events (3.1 per 100,000 person-years). Current users vs nonusers: adjusted HR 0.75 (95% CI 0.31–1.85); current vs former 0.70 (0.29–1.72). Upper CI limit means a doubling could not be ruled out. Class-level (not reported by drug).
Funding / affiliation: Funded by the Agency for Healthcare Research and Quality and the FDA.
Cooper WO, Habel LA, Sox CM, et al. (2011). ADHD drugs and serious cardiovascular events in children and young adults. N Engl J Med 365(20):1896-904. DOI · PubMed 22043968
-
ADHD medicines (class): serious heart events in adults 25–64
In US health-plan records for 150,359 adults aged 25 to 64 taking methylphenidate, amphetamine or atomoxetine, each matched with two non-users, current or new use was not linked to more heart attacks, sudden cardiac deaths or strokes. The apparent lower risk in users most likely reflects that healthier people were prescribed the medicines.
This study looked at ADHD medicines as a group; the abstract does not report amphetamine products separately.
Retrospective cohort, 4 US sites; 150,359 users matched 1:2 to nonusers (443,198 total); 806,182 person-years (median 1.3 y). Current use vs nonuse adjusted RR 0.83 (95% CI 0.72–0.96); new users 0.77 (0.63–0.94); current vs remote use 1.03 (0.86–1.24); new vs remote 1.02 (0.82–1.28). Apparent protective associations attributed to healthy-user bias. Class-level.
Habel LA, Cooper WO, Sox CM, et al. (2011). ADHD medications and risk of serious cardiovascular events in young and middle-aged adults. JAMA 306(24):2673-83. DOI · PubMed 22161946
Growth (6 studies)
-
Lisdexamfetamine
Over 2 years of open-label lisdexamfetamine in 314 children and teens, height and weight still increased, but growth relative to peers slowed during the first 36 weeks and then levelled off. Most participants progressed through puberty as expected.
2-year open-label safety study (N=314; 191 completed). Mean change: weight +2.1 kg, height +6.1 cm, BMI −0.5 kg/m². z-scores declined through week 36 then stabilised; final changes weight −0.51, height −0.24, BMI −0.59 (nominal p<0.0001). Weight decrease TEAE 20.1%. No control group.
Funding / affiliation: Funded by Shire Development LLC (lisdexamfetamine manufacturer) per PubMed record.
Banaschewski T, Johnson M, Nagy P, et al. (2018). Growth and Puberty in a 2-Year Open-Label Study of Lisdexamfetamine Dimesylate in Children and Adolescents with Attention-Deficit/Hyperactivity Disorder. CNS Drugs 32(5):455-467. DOI · PubMed 29790103
-
Stimulants (mostly OROS methylphenidate), children 5–12
Children whose weight dropped after starting a stimulant were randomly assigned to medicine on school days only (a planned break on weekends and holidays), a daily high-calorie snack, or monthly checks. All three helped weight gain, but none of them sped up growth in height. Most families in the school-days-only group went back to giving the medicine after school because symptoms got worse.
RCT, 230 children aged 5–12 starting stimulants (78%, mainly OROS-MPH) or behavioral treatment for 30 months; children with a BMI decline >0.5 z after 6 months (n=71) were randomized to monthly monitoring, drug holidays (medication limited to school days) or a 150-kcal daily supplement. Weight velocity rose after randomization across all arms (β=0.271, SE 0.027, p<.001); per actual use, supplementation (p<.01) and holidays (p<.05) increased weight velocity more than monitoring. No arm increased height velocity. Full text: parents gave medication on only 5% of weekend days in the holiday arm; 16 of 23 (70%) reverted to after-school dosing because of worsening symptoms.
Waxmonsky JG, Pelham WE 3rd, Campa A, et al. (2020). A Randomized Controlled Trial of Interventions for Growth Suppression in Children With Attention-Deficit/Hyperactivity Disorder Treated With Central Nervous System Stimulants. J Am Acad Child Adolesc Psychiatry 59(12):1330-1341. DOI · PubMed 31473291
-
Methylphenidate (immediate-release, twice daily)
In a 4-week trial in boys taking methylphenidate twice a day, swapping in a placebo on weekends led to less trouble sleeping and a trend toward better appetite. ADHD symptoms on weekends (parent ratings) and on the following Monday (teacher ratings) did not rise significantly. The study was small and short.
Double-blind RCT, 28 days, boys with ADHD: MPH b.i.d. 7 days/week (n=21) vs weekdays with weekend placebo (n=19). No significant group difference in parent weekend ratings (endpoint p=0.41, ES 0.26) or Monday teacher ratings (p=0.99, ES 0.002). Weekend placebo: less insomnia (F=3.96, p=0.05) and a trend to less appetite interference (F=3.18, p=0.08). Growth was not an outcome.
Martins S, Tramontina S, Polanczyk G, et al. (2004). Weekend holidays during methylphenidate use in ADHD children: a randomized clinical trial. J Child Adolesc Psychopharmacol 14(2):195-206. DOI · PubMed 15319017
-
Methylphenidate (long-term use)
Children on long-term methylphenidate were randomly assigned to stop or continue it over two summers. One summer off was followed by more weight gain but no height difference; two summers off had a significant positive effect on height. The study could not show whether this changes final adult height.
Controlled withdrawal study: hyperactive children on long-term MPH randomized to be off or remain on medication over two consecutive summers. After one summer: no height difference, higher weight in the off-medication group. After two summers: significant positive effect on height (not weight). Authors note the results do not address long-term effects on height. Needs full-text check: sample size and effect sizes are not in the abstract.
Klein RG, Landa B, Mattes JA, et al. (1988). Methylphenidate and growth in hyperactive children. A controlled withdrawal study. Arch Gen Psychiatry 45(12):1127-30. DOI · PubMed 3058088
-
ADHD medicines (mostly stimulants), children and teens
A review of 22 studies from 1972 to 2013 found that 25–70% of families take breaks from ADHD medicine, most often during school holidays. Breaks are used to check whether medicine is still needed and to manage side effects. Longer breaks were linked to better growth, and shorter breaks could reduce sleep problems and improve appetite.
Literature review (22 studies, 1972–2013) of drug holidays in children and adolescents. Prevalence 25–70% of families, more often in school holidays; purposes: testing ongoing need, managing adverse effects and tolerance. Positive impact on growth with longer breaks; shorter breaks could reduce insomnia and improve appetite. Study quality not graded in the abstract.
Ibrahim K, Donyai P (2015). Drug Holidays From ADHD Medication: International Experience Over the Past Four Decades. J Atten Disord 19(7):551-68. DOI · PubMed 25253684
-
Stimulants (MTA follow-up into adulthood)
In the long-term follow-up of the MTA study, young adults who had taken stimulants consistently through childhood were on average about 2.4 cm shorter than those who took them inconsistently, and treated groups were about 2.6 cm shorter than those who took little or none. Consistent long-term use was not linked to fewer adult ADHD symptoms. These groups were not randomized.
Observational follow-up of the MTA (579 randomized; 515 followed; 289 classmates as local norms), outcomes at ~25 years. Adult height: Consistent/Inconsistent users 2.55 ± 0.73 cm shorter than Negligible users (p<.0005); Consistent 2.36 ± 1.13 cm shorter than Inconsistent (p<.04). Naturalistic-subgroup comparisons for symptom severity were not significant. Full text: height was measured in 402 ADHD participants (Consistent subgroup n=33).
Swanson JM, Arnold LE, Molina BSG, et al. (2017). Young adult outcomes in the follow-up of the multimodal treatment study of attention-deficit/hyperactivity disorder: symptom persistence, source discrepancy, and height suppression. J Child Psychol Psychiatry 58(6):663-678. DOI · PubMed 28295312
Psychosis and mania (3 studies)
-
Amphetamine vs methylphenidate
In US insurance data on 221,846 adolescents and young adults (13–25) starting a stimulant, new psychosis treated with an antipsychotic occurred in about 1 in 660. It was about twice as common with amphetamine (0.21%) as with methylphenidate (0.10%).
Propensity-matched cohort (2 claims databases, 2004–2015): 110,923 MPH vs 110,923 amphetamine starters. 343 psychosis episodes: 106 (0.10%) MPH vs 237 (0.21%) amphetamine; HR 1.65 (95% CI 1.31–2.09) for amphetamine.
Funding / affiliation: Non-industry (NIMH and others).
Moran LV, Ongur D, Hsu J, et al. (2019). Psychosis with Methylphenidate or Amphetamine in Patients with ADHD. N Engl J Med 380(12):1128-1138. DOI · PubMed 30893533
-
Amphetamines (class)
Among young people hospitalized for psychiatric reasons, recent prescription amphetamine use was linked to higher odds of a first episode of psychosis or mania, and the link was strongest at higher doses (above 30 mg of dextroamphetamine-equivalent). Recent methylphenidate use was not linked. Because only hospitalized patients were compared, results may not apply to everyone.
Case-control (McLean Hospital EHR, 2005–2019): 1,374 cases (incident psychosis/mania, ages 16–35) vs 2,748 psychiatric controls. Past-month amphetamine aOR 2.68 (1.90–3.77); >30 mg dextroamphetamine equivalents ~5.28-fold. Methylphenidate aOR 0.91 (0.54–1.55). Selection bias acknowledged.
Moran LV, Skinner JP, Shinn AK, et al. (2024). Risk of Incident Psychosis and Mania With Prescription Amphetamines. Am J Psychiatry 181(10):901-909. DOI · PubMed 39262211
-
Stimulants in ADHD (class): psychosis and bipolar disorder
Pooling 16 studies of about 391,000 people with ADHD, a 2025 review estimated that roughly 2% to 4% of people treated with stimulants later had psychotic symptoms, a psychotic disorder or bipolar disorder, although results varied widely between studies. Psychosis was more common with amphetamines than with methylphenidate. These studies cannot show that the medicine caused the problems, and the authors advise discussing these risks and watching for them during treatment.
Systematic review and meta-analysis (searches to Oct 1, 2024), 16 studies, N=391,043 (mean age 12.6 y). Pooled occurrence among stimulant-treated individuals: psychotic symptoms 2.76% (95% CI 0.73–9.88; k=10), psychotic disorder 2.29% (1.52–3.40; k=4), bipolar disorder 3.72% (0.77–16.05; k=4); heterogeneity I² >95%. Psychosis, amphetamines vs methylphenidate: OR 1.57 (1.15–2.16; k=3, n=231,325). Higher occurrence in North American studies, with longer follow-up, more female participants, smaller samples and higher stimulant doses. Observational data; causality not established.
Salazar de Pablo G, Aymerich C, Chart-Pascual JP, et al. (2025). Occurrence of Psychosis and Bipolar Disorder in Individuals With Attention-Deficit/Hyperactivity Disorder Treated With Stimulants: A Systematic Review and Meta-Analysis. JAMA Psychiatry 82(11):1103-1112. DOI · PubMed 40900605
Other safety findings (1 study)
-
Stimulants and tics (children)
Pooling 22 placebo-controlled trials in 2,385 children with ADHD, new or worse tics were reported about as often on stimulants (5.7%) as on placebo (6.5%). Type of stimulant, dose and treatment length made no difference. The authors suggest that tics appearing during treatment are often coincidental and that retrying the stimulant may be reasonable.
This study looked at ADHD medicines as a group; the abstract does not report amphetamine products separately.
Meta-analysis of 22 double-blind, randomized, placebo-controlled trials; n=2,385 children with ADHD. Tic event rate 5.7% (95% CI 3.7–8.6%) on psychostimulants vs 6.5% (4.4–9.5%) on placebo; RR 0.99 (0.78–1.27; p = .962). No effect of stimulant type, dose, duration, recorder or age; crossover designs showed higher measured risk than parallel-group trials.
Cohen SC, Mulqueen JM, Ferracioli-Oda E, et al. (2015). Meta-Analysis: Risk of Tics Associated With Psychostimulant Use in Randomized, Placebo-Controlled Trials. J Am Acad Child Adolesc Psychiatry 54(9):728-36. DOI · PubMed 26299294
ADHD with other conditions (4 studies)
-
ADHD with tic disorders
In children with ADHD and tics (9 trials), methylphenidate, alpha-2 agonists (clonidine, guanfacine) and atomoxetine improved ADHD symptoms. Alpha-2 agonists and atomoxetine also reduced tics, and methylphenidate did not worsen tics in the short term. Very high doses of dextroamphetamine were linked to worse tics.
Meta-analysis, 9 studies, 477 subjects. ADHD efficacy: MPH, α2 agonists, desipramine, ATX. Tic improvement: α2 agonists and ATX. No evidence MPH worsened tics short-term; supratherapeutic dextroamphetamine worsened tics. Authors: MPH gave the greatest and most immediate ADHD improvement.
Bloch MH, Panza KE, Landeros-Weisenberger A, et al. (2009). Meta-analysis: treatment of attention-deficit/hyperactivity disorder in children with comorbid tic disorders. J Am Acad Child Adolesc Psychiatry 48(9):884-893. DOI · PubMed 19625978
-
ADHD with tic disorder or Tourette syndrome (children)
A network meta-analysis of 8 trials in 575 children and teens with both ADHD and a tic disorder found that stimulants improved ADHD symptoms and did not make tics worse. Alpha-2 agonists (guanfacine or clonidine), alone or with a stimulant, improved both ADHD and tics. The evidence was rated low to very low certainty.
Network meta-analysis of double-blind RCTs (searches to Sep 2023): 8 RCTs, n=575 with TD + ADHD. Stimulants vs placebo: ADHD SMD −0.54 (95% CI −1.05 to −0.03); tics −0.22 (−0.49 to 0.05), not worsened. α2 agonists: ADHD −0.72 (−1.13 to −0.31), tics −0.70 (−0.96 to −0.45). Stimulants + α2 agonists: ADHD −0.84 (−1.54 to −0.13), tics −0.60 (−1.04 to −0.17). Low to very low certainty (CINeMA).
Farhat LC, Behling E, Landeros-Weisenberger A, et al. (2024). Pharmacological Interventions for Attention-Deficit/Hyperactivity Disorder in Children and Adolescents with Tourette Disorder: A Systematic Review and Network Meta-Analysis. J Child Adolesc Psychopharmacol 34(9):373-382. DOI · PubMed 39320340
-
ADHD medicines in bipolar disorder (ISBD task force review)
A systematic review by an international bipolar disorder task force (17 studies, 2,136 people with bipolar disorder) found that methylphenidate or mixed amphetamine salts may improve ADHD symptoms, with limited evidence on thinking skills. When used together with mood stabilizers, the medicines were not linked to more mania or hypomania.
ISBD Targeting Cognition Task Force systematic review (searches to Jun 2023): 17 studies, N=2,136 (armodafinil k=4, methylphenidate k=4, bupropion k=4, clonidine k=1, lisdexamphetamine k=1 n=25, mixed amphetamine salts k=1 n=30, modafinil k=2). Three studies found ADHD-symptom reduction (two methylphenidate, one amphetamine salts). No increased (hypo)mania risk observed alongside mood stabilizers. Risk of bias low in 5, moderate in 11, serious in 1.
Miskowiak KW, Obel ZK, Guglielmo R, et al. (2024). Efficacy and safety of established and off-label ADHD drug therapies for cognitive impairment or attention-deficit hyperactivity disorder symptoms in bipolar disorder: A systematic review by the ISBD Targeting Cognition Task Force. Bipolar Disord 26(3):216-239. DOI · PubMed 38433530
-
ADHD medicines (class) in people with epilepsy or a seizure history
In 21,557 Swedish people with a history of seizures, periods on ADHD medicine were linked to fewer emergency seizure visits than periods off medicine in the same people, and starting medicine was not followed by more seizures. The authors conclude that epilepsy should not automatically rule out ADHD medicine. Observational and class-level.
This study looked at ADHD medicines as a group; the abstract does not report amphetamine products separately.
Swedish registers, n=21,557 with a seizure history (born 1987–2003), incl. 6,773 youth with epilepsy; 2006–2013. Among 995 initiators, no significant change in seizure rate in the 24 weeks before vs after initiation. Medication periods vs non-medication periods (within-individual): HR 0.73 (95% CI 0.57–0.94); similar in youth with epilepsy and continuous antiepileptic treatment. Not reported by drug.
Brikell I, Chen Q, Kuja-Halkola R, et al. (2019). Medication treatment for attention-deficit/hyperactivity disorder and the risk of acute seizures in individuals with epilepsy. Epilepsia 60(2):284-293. DOI · PubMed 30682219
Pregnancy (9 studies)
These research findings do not replace the FDA label. For what the label says, see Pregnancy and breastfeeding above.
-
Methylphenidate and amphetamines
In very large US and Nordic pregnancy registries, first-trimester methylphenidate was linked to a small increase in heart defects (about 28% higher relative risk), while amphetamines were not linked to more birth defects. Absolute risks remained low.
Cohort: 1,813,894 US Medicaid pregnancies; Nordic replication 2,560,069. US adjusted RR, MPH: any malformation 1.11 (0.91–1.35), cardiac 1.28 (0.94–1.74); amphetamines: any 1.05 (0.93–1.19), cardiac 0.96 (0.78–1.19). Pooled US+Nordic MPH cardiac RR 1.28 (1.00–1.64). US cardiac risk per 1,000: 12.7 unexposed, 18.8 MPH, 15.4 amphetamines.
Huybrechts KF, Bröms G, Christensen LB, et al. (2018). Association Between Methylphenidate and Amphetamine Use in Pregnancy and Risk of Congenital Malformations: A Cohort Study From the International Pregnancy Safety Study Consortium. JAMA Psychiatry 75(2):167-175. DOI · PubMed 29238795
-
Stimulants and atomoxetine in pregnancy
A 2026 review of 25 studies found that, after accounting for differences between mothers, using stimulants or atomoxetine in pregnancy was not linked to more major birth defects or to most pregnancy and child-development problems. A small link with methylphenidate and heart defects, and with a low newborn Apgar score, could not be ruled out and needs more study.
Systematic review/meta-analysis (25 studies; 23 pooled). Major malformations: unadjusted RR 1.25 (1.14–1.37), adjusted 1.04 (0.97–1.12). Cardiovascular malformations aRR 1.20 (0.88–1.63); methylphenidate-specific aRR 1.33 (1.01–1.74). No adjusted association with miscarriage, preterm birth, low birth weight, SGA, NICU admission or offspring neurodevelopmental disorders. Low 5-min Apgar aRR 1.21 (1.03–1.42). Authors attribute crude associations largely to confounding.
Komargodski R, Tillawe A, Berlin M, et al. (2026). Pregnancy and Offspring Outcomes After Prenatal Stimulant or Atomoxetine Exposure: A Systematic Review and Meta-analysis. Am J Obstet Gynecol MFM 102165. DOI · PubMed 42887725
-
ADHD medicines in pregnancy (class)
Pooling 8 cohort studies, ADHD medicine during pregnancy was linked to more newborn intensive-care admissions but not to other maternal or newborn problems; methylphenidate showed a borderline link with heart defects.
Meta-analysis of 8 cohorts. NICU admission RR 1.88 (1.7–2.08) vs never exposed; 1.38 (1.23–1.54) vs exposure before/after pregnancy only. MPH and cardiac malformation RR 1.27 (0.99–1.63; p=0.065). No association with other outcomes; limited confounder adjustment.
Jiang HY, Zhang X, Jiang CM, et al. (2019). Maternal and neonatal outcomes after exposure to ADHD medication during pregnancy: A systematic review and meta-analysis. Pharmacoepidemiol Drug Saf 28(3):288-295. DOI · PubMed 30585374
-
Amphetamine/dextroamphetamine in the second half of pregnancy: child neurodevelopment
In US Medicaid and private insurance records for more than 4 million pregnancies, children whose mothers took amphetamine/dextroamphetamine in the second half of pregnancy were not more likely to be diagnosed with autism, ADHD or other developmental disorders once other factors, including the mother’s own conditions, were taken into account. Unadjusted numbers were 2 to 3 times higher, which shows how much those other factors matter.
US cohorts: Medicaid 2000–2018 (2,496,771 unexposed; 4,693 amphetamine/dextroamphetamine-exposed; 786 methylphenidate) and MarketScan 2003–2020 (1,773,501; 2,372; 337). Exposure: dispensing in the second half of pregnancy. Adjusted HRs for amphetamine/dextroamphetamine: autism 0.80 (95% CI 0.56–1.14), ADHD 1.07 (0.89–1.28), any neurodevelopmental disorder 0.91 (0.81–1.28). Methylphenidate: ADHD 1.43 (1.12–1.82), not robust to stricter control for maternal ADHD. Published in JAMA Psychiatry 2024.
Suarez EA, Bateman BT, Hernandez-Diaz S, et al. (2024). Prescription Stimulant Use During Pregnancy and Risk of Neurodevelopmental Disorders in Children. JAMA Psychiatry 81(5):477-488. DOI · PubMed 38265792
-
ADHD medicines in pregnancy (incl. amphetamines): child neurodevelopment
A Swedish study of 861,650 children, combined with an earlier Danish study, found no higher risk of autism, ADHD or other developmental disorders in children exposed before birth to methylphenidate, amphetamines or atomoxetine, compared with children whose mothers stopped their medicine before pregnancy. Results were similar when siblings were compared.
Swedish population cohort 2008–2017: 861,650 children of 572,731 mothers; comparator = maternal discontinuation before conception. Adjusted HR: any NDD 0.95 (95% CI 0.82–1.11), ADHD 0.92 (0.78–1.08), ASD 0.86 (0.63–1.18); consistent by medication type, timing, duration and in sibling comparisons. Meta-analysis with a Danish study: pooled HR any NDD 1.00 (0.83–1.20).
Bang Madsen K, Larsson H, Skoglund C, et al. (2025). In utero exposure to methylphenidate, amphetamines and atomoxetine and offspring neurodevelopmental disorders - a population-based cohort study and meta-analysis. Mol Psychiatry 30(9):3885-3894. DOI · PubMed 40148550
-
Stimulants in pregnancy (mostly amphetamine-dextroamphetamine): placental complications
In US Medicaid records, stimulant use in early pregnancy (mostly amphetamine-dextroamphetamine) was linked to a small rise in preeclampsia, a pregnancy blood-pressure problem (about 29% higher in relative terms; the baseline risk was about 3.7 in 100 pregnancies). Continuing a stimulant after 20 weeks was linked to a small rise in preterm birth. The authors say the absolute increases are small and should not by themselves lead women with significant ADHD to stop treatment.
US Medicaid 2000–2010: amphetamine-dextroamphetamine (n=3,331), methylphenidate (1,515) and atomoxetine (453, negative control) monotherapy in the first half of pregnancy vs 1,461,493 unexposed. Baseline risks: preeclampsia 3.7%, abruption 1.4%, SGA 2.9%, preterm birth 11.2%. Stimulant aRR: preeclampsia 1.29 (95% CI 1.11–1.49), abruption 1.13 (0.88–1.44), SGA 0.91 (0.77–1.07), preterm 1.06 (0.97–1.16). Continuation after 20 weeks (n=1,319) vs discontinuation (3,527): preterm birth 1.30 (1.10–1.55), preeclampsia 1.26 (0.94–1.67). Atomoxetine not associated.
Cohen JM, Hernández-Díaz S, Bateman BT, et al. (2017). Placental Complications Associated With Psychostimulant Use in Pregnancy. Obstet Gynecol 130(6):1192-1201. DOI · PubMed 29112657
-
Stimulants in pregnancy: first trimester only vs continued
In US commercial insurance records (10,265 matched patients), stimulant use only in the first 3 months of pregnancy was not linked to more complications. Continuing into the second or third trimester was linked to more preeclampsia, high blood pressure in pregnancy, placental abruption and preterm birth than in unexposed pregnancies. Results were similar for amphetamine and methylphenidate products. Observational.
US commercial claims 2013–2021; 1:1 propensity-matched, n=10,265. First-trimester-only exposure vs none: live birth RR 1.08 (95% CI 1.06–1.10), spontaneous abortion 0.69 (0.64–0.76), preterm birth 0.75 (0.62–0.90). Continued into 2nd/3rd trimester vs none: placental abruption 1.63 (1.03–2.57), pre-eclampsia 1.42 (1.19–1.69), gestational hypertension 1.37 (1.16–1.61), preterm birth 1.34 (1.12–1.62); stillbirth 1.42 (0.76–2.67), not significant. Directionally consistent for amphetamine- and methylphenidate-containing products. J Atten Disord 2026 (epub Dec 2025).
Hasan SA, Murugappan M, Westberg S, et al. (2026). Prescription Stimulant Continuation in Pregnancy and Birth Outcomes. J Atten Disord 30(3):315-328. DOI · PubMed 41400021
-
Stimulants in the first trimester: major malformations (US registry)
In the Massachusetts General Hospital pregnancy registry (1,988 women), babies exposed to a prescription stimulant in the first trimester (mostly mixed amphetamine salts or lisdexamfetamine) did not have more major birth defects than unexposed babies. The study was small, so it can only rule out large risks.
MGH National Pregnancy Registry for Psychiatric Medications; N=1,988 (mixed amphetamine salts 173, lisdexamfetamine 40, methylphenidate 45, dexmethylphenidate 3; controls 1,755). Major malformations reviewed by a blinded dysmorphologist. OR for any first-trimester stimulant 0.39 (95% CI 0.09–1.61). No major malformations among lisdexamfetamine-, methylphenidate- or dexmethylphenidate-exposed infants. Preliminary. NCT01246765.
Szpunar MJ, Freeman MP, Kobylski LA, et al. (2023). Risk of Major Malformations in Infants After First-Trimester Exposure to Stimulants: Results From the Massachusetts General Hospital National Pregnancy Registry for Psychiatric Medications. J Clin Psychopharmacol 43(4):326-332. DOI · PubMed 37235505
-
Stimulants in pregnancy: perinatal outcomes (Canada and Australia)
In about 554,000 pregnancies in Ontario and 139,000 in New South Wales, pregnancies exposed to prescription stimulants had more complications in raw numbers, but most of these links faded after accounting for other differences between the groups. The authors think stimulants are not a major cause of most of these outcomes. Results for preeclampsia were unclear, and they suggest closer monitoring.
Population cohorts: Ontario 2002–2017 (N=554,272; 1,360 exposed, 0.25%) and NSW 2003–2011 (N=139,229; 146 exposed, 0.10%); amphetamine, methylphenidate, dextroamphetamine or lisdexamfetamine. IPTW: nearly all associations attenuated. Pre-eclampsia weighted OR 2.02 (95% CI 1.42–2.88) Ontario; 1.50 (0.77–2.94) NSW; 1.24 (0.64–2.40) restricted to social-security beneficiaries. Residual confounding likely.
Camacho X, Zoega H, Gomes T, et al. (2023). The association between psychostimulant use in pregnancy and adverse maternal and neonatal outcomes: results from a distributed analysis in two similar jurisdictions. Int J Epidemiol 52(1):190-202. DOI · PubMed 36135973
Off-label uses (not FDA-approved) (5 studies)
-
Lisdexamfetamine added to an antidepressant (off-label)
Not an FDA-approved use. In 143 adults whose depression was mild or in remission but who still had executive-function problems, adding lisdexamfetamine to their antidepressant improved self-rated executive function. Depression scores also fell slightly more than with placebo (about 2 points, at the edge of significance).
RCT, 143 randomized (119 completed), LDX 20–70 mg/day × 9 weeks. BRIEF-A GEC LSMD −8.0 (−12.7 to −3.3; P=0.0009); MADRS −1.9 (−3.7 to 0.0; P=0.0465). TEAEs 78.9% vs 73.6%.
Funding / affiliation: Lead author affiliated with Shire (manufacturer) per PubMed record.
Madhoo M, Keefe RS, Roth RM, et al. (2014). Lisdexamfetamine dimesylate augmentation in adults with persistent executive dysfunction after partial or full remission of major depressive disorder. Neuropsychopharmacology 39(6):1388-98. DOI · PubMed 24309905
-
Psychostimulants for depression (off-label)
Not an FDA-approved use. A pooled analysis of placebo-controlled trials in depression found results varied by drug. Dextroamphetamine had a positive but very imprecise result. Lisdexamfetamine and methylphenidate were not significantly better than placebo. The authors said these medicines are insufficiently studied for mood disorders.
MA of RCTs in MDD/bipolar depression. By agent (response): dextroamphetamine OR 7.11 (1.09–46.44); lisdexamfetamine OR 1.21 (0.94–1.56; NS); methylphenidate OR 1.49 (0.88–2.54; NS); armodafinil/modafinil OR 1.47 (1.20–1.81).
McIntyre RS, Lee Y, Zhou AJ, et al. (2017). The Efficacy of Psychostimulants in Major Depressive Episodes: A Systematic Review and Meta-Analysis. J Clin Psychopharmacol 37(4):412-418. DOI · PubMed 28590365
-
Lisdexamfetamine in children aged 4–5 (preschool)
Not an FDA-approved use: lisdexamfetamine is approved for ADHD from age 6. In a 6-week trial in 199 children aged 4 to 5, lisdexamfetamine reduced ADHD symptoms more than placebo, but the effect was smaller than in studies of older children, and the share rated much improved (42% vs 24%) was not significantly different. Side effects (47% vs 42%) were mostly less appetite and irritability.
Phase 3, double-blind, fixed-dose RCT; N=199 aged 4–5, randomized 5:5:5:5:6 to LDX 5, 10, 20, 30 mg or placebo for 6 weeks. Pooled LDX (10–30 mg) vs placebo, ADHD-RS-IV-PS: −5.9 (95% CI −11.01 to −0.78; p = .0242; ES −0.43). CGI-I improved 41.7% vs 24.3% (p = .0857); CGI-I score difference −0.6 (p = .0074). TEAEs 46.6% vs 42.2%; decreased appetite 13.7% vs 8.9%, irritability 9.6% vs 0%; discontinuation for TEAEs 5.5% vs 4.4%. Effect size smaller than in older children. NCT03260205.
Funding / affiliation: Authors from Takeda (Shire) per the PubMed record.
Childress AC, Lloyd E, Jacobsen L, et al. (2022). Efficacy and Safety of Lisdexamfetamine in Preschool Children With Attention-Deficit/Hyperactivity Disorder. J Am Acad Child Adolesc Psychiatry 61(12):1423-1434. DOI · PubMed 35577034
-
Adjunctive mixed amphetamine salts or lisdexamfetamine in bipolar depression (adults)
Not an FDA-approved use. Pooling two small 8-week placebo-controlled trials in 57 adults with bipolar depression, adding mixed amphetamine salts or lisdexamfetamine to existing treatment improved depression more than placebo (response 66% vs 17%), without more mania. Patients were carefully selected, and larger studies are needed.
Pooled analysis of two 8-week RCTs of adjunctive MAS and LDX; N=57 (BD-I 23, BD-II 34; mean age 40.1). MADRS mean % reduction 54.6% vs 25.6% (p = 0.005); response 65.7% vs 16.7% (p < 0.001); remission 48.8% vs 15.3% (p = 0.007); CGI-BP improvement 65.0% vs 23.5%. No between-group YMRS difference (p ≥ 0.36). Carefully selected patients.
Frye MA, Sanchez-Ruiz JA, Ali DN, et al. (2026). Pooled analysis assessing the efficacy and safety of amphetamine derivative adjunctive therapy for bipolar depression. J Affect Disord 414:122257. DOI · PubMed 42442671
-
Stimulant doses above the FDA-labeled range (adults)
Not an FDA-approved use: doses above the label’s range are unlicensed. Pooling 47 trials in 7,714 adults, methylphenidate doses above the labeled range reduced symptoms only slightly more than labeled doses (very low certainty evidence), while stopping because of side effects about doubled. For amphetamines, higher doses gave no added benefit. The authors say higher doses may be tried cautiously if needed and tolerated, but large gains are unlikely.
Dose-response meta-analyses and network meta-analyses of 47 double-blind placebo-controlled RCTs in adults (n=7,714; mean age 35). Methylphenidate: progressively smaller symptom gains with higher doses and continued rise in adverse-event dropouts; unlicensed vs licensed doses SMD −0.23 (95% CI −0.44 to −0.02; very low certainty); adverse-event dropout OR 2.02 (1.19–3.43; moderate certainty). Amphetamines: curve approached a plateau; unlicensed vs licensed SMD −0.08 (−0.24 to 0.08; very low certainty). Based on group averages.
Farhat LC, Flores JM, Avila-Quintero VJ, et al. (2024). Treatment Outcomes With Licensed and Unlicensed Stimulant Doses for Adults With Attention-Deficit/Hyperactivity Disorder: A Systematic Review and Meta-Analysis. JAMA Psychiatry 81(2):157-166. DOI · PubMed 37878348
Frequently asked questions
How long does Vyvanse last?
In label classroom studies, children improved from 2 hours (not at 1 hour) through 12–13 hours after a morning dose, and adults improved at every time point measured from 2 to 14 hours. Individual response varies.
How long does it take for Vyvanse to start working?
In a pediatric label classroom study the effect was significant from 2 hours after the dose but not at 1 hour, because lisdexamfetamine must first be converted to dextroamphetamine. Individual response varies.
Can the Vyvanse capsule be opened?
Yes. Empty the whole capsule into yogurt, water, or orange juice, mix until dispersed, and take it right away. Do not store the mixture. Chewable tablets must be chewed thoroughly.
Is there a generic Vyvanse?
Yes. Many companies make AB-rated generic lisdexamfetamine capsules, and several make chewable tablets.
Is Vyvanse in shortage?
Lisdexamfetamine is on the FDA shortage list (October 2026), but Takeda lists brand Vyvanse capsules as available. Some generic manufacturers report limited supply.
Vyvanse vs Adderall XR — what’s the difference?
Vyvanse is a prodrug converted to dextroamphetamine in the blood. Adderall XR is mixed amphetamine salts in immediate- and delayed-release beads. They are not interchangeable milligram for milligram.
Is there a liquid Vyvanse?
Yes. Arynta is a lisdexamfetamine oral solution (10 mg/mL) approved in 2025 with the same dosing as Vyvanse.
Is Vyvanse approved for binge eating?
Yes, for moderate to severe binge-eating disorder in adults. It is not approved for weight loss or obesity.
What happens if I miss a dose?
Follow your clinician’s and pharmacist’s instructions. The label advises avoiding afternoon doses because of insomnia, so a missed dose remembered late in the day is usually not taken. Do not double the next dose.
Can Vyvanse be taken with food?
Yes. Take Vyvanse in the morning with or without food (label section 2.2). Food does not change how much medicine is absorbed from the capsule; a high-fat meal delays the peak by about 1 hour (label section 12.3).
Does Vyvanse cause a crash or rebound as it wears off?
The Vyvanse label does not describe a “crash” or rebound effect. In the label’s studies, benefit lasted through 12 hours in one pediatric study and through 14 hours in adults (label section 14). Irritability and anxiety are among the most common side effects (label section 6.1).If ADHD symptoms, irritability or tiredness come back as a dose wears off, tell your prescriber; the timing or dose may need adjusting.
What are the most common side effects of Vyvanse?
In children 6 to 17 and adults with ADHD, the Medication Guide lists loss of appetite, decreased appetite, diarrhea, dry mouth, trouble sleeping, stomach pain, anxiety, weight loss, dizziness, irritability, nausea and vomiting (label section 6.1). These are not all the possible side effects; call your prescriber for advice about side effects that bother you.
Is an ECG (heart tracing) needed before starting?
Usually not. Before prescribing, the clinician should ask about fainting, chest pain, a racing heartbeat, known heart problems, and any family history of sudden death or heart rhythm problems, and do a physical exam. An ECG or a visit to a heart specialist is used when any of these raise concern. UK, Canadian and European guidance does not call for a routine ECG when there are no such warning signs.
Can my child take breaks from the medicine on weekends or over the summer?
Sometimes, but plan it with the prescriber. Breaks can help with appetite, weight gain and sleep, and the label says children who are not growing or gaining weight as expected may need treatment paused. Breaks have not been shown to reliably make children taller, and ADHD symptoms can come back on days off, so it depends on how much your child struggles without the medicine. A break can also show whether the medicine is still needed.
Can I take Vyvanse while pregnant or breastfeeding?
Tell your clinician if you are pregnant or planning a pregnancy. The Vyvanse label reports a higher risk of premature birth and low birth weight with amphetamines in pregnancy and advises watching newborns for withdrawal. Breastfeeding is not recommended during treatment. A pregnancy registry for ADHD medicines can be reached at 1-866-961-2388.
Prescribing guidelines
Amphetamine-class stimulants, like methylphenidates, are first-line pharmacologic options for school-age children, adolescents, and adults with ADHD per major guidelines when medication is indicated.
Resources
Sources
- Takeda Pharmaceuticals America, Inc. Vyvanse (lisdexamfetamine dimesylate) capsules and chewable tablets, CII. Prescribing Information, revised 04/2026. DailyMed (accessed Oct 2026).
- U.S. Food and Drug Administration. Approved Drug Products with Therapeutic Equivalence Evaluations (Orange Book), data files dated October 2026. FDA.
- U.S. Food and Drug Administration. Drug Shortages database: Lisdexamfetamine Dimesylate Capsule and Tablet, Chewable (Currently in Shortage; first posted Jul 14, 2023), accessed Oct 20, 2026. FDA (capsule); FDA (chewable).
- American Society of Health-System Pharmacists. Drug Shortage Detail: Lisdexamfetamine Dimesylate Capsules. Updated Aug 28, 2026. ASHP.
- Wolraich ML, Hagan JF Jr, Allan C, et al.; American Academy of Pediatrics Subcommittee on Children and Adolescents with ADHD. Clinical Practice Guideline for the Diagnosis, Evaluation, and Treatment of Attention-Deficit/Hyperactivity Disorder in Children and Adolescents. Pediatrics. 2019;144(4):e20192528. AAP.
- Centers for Disease Control and Prevention. Clinical Care of ADHD in Children (summary of the AAP guideline; updated Oct 21, 2026). CDC (accessed 2026).
- National Institute for Health and Care Excellence. Attention deficit hyperactivity disorder: diagnosis and management (NG87), 2018, updated 2019; recommendations 1.7.3–1.7.5, 1.7.20–1.7.22, 1.8.6–1.8.7 and 1.10.3. NICE (accessed Oct 2026).
- Pliszka S, AACAP Work Group on Quality Issues. Practice parameter for the assessment and treatment of children and adolescents with attention-deficit/hyperactivity disorder. J Am Acad Child Adolesc Psychiatry. 2007;46(7):894-921. PubMed 17581453.
- Drugs and Lactation Database (LactMed). Lisdexamfetamine. National Institute of Child Health and Human Development; revised Apr 2026. NCBI Bookshelf NBK501741.