
Onyda XR
NONSTIMULANTS · CLONIDINE HYDROCHLORIDE EXTENDED-RELEASE ORAL SUSPENSION
Key facts
- Drug class
- Alpha-2 Adrenergic Agonist · Nonstimulants
- Active ingredient
- clonidine
- FDA-approved ages
- 6 years and older (monotherapy or adjunct to a CNS stimulant)
- Form and strengths
- Extended-release oral suspension; 0.1 mg/mL extended-release oral suspension
- Usual dose and maximum (label)
- Start 0.1 mg (1 mL) at bedtime; maximum 0.4 mg (4 mL) once daily.
- Duration
- Taken once daily at bedtime; the label does not describe hour-by-hour effects.
- DEA schedule
- Not a controlled substance
- Generic
- No generic (see Generic manufacturers)
- Label date
- Prescribing Information revised 04/2025 (DailyMed)
Label last checked: Oct 2026 — Prescribing Information revised 04/2025 (DailyMed) · Last medical review: November 4, 2026
Educational information only, not medical advice. Do not start, stop or change a medication without your prescriber. Medical disclaimer
What it is
Onyda XR is a liquid form of extended-release clonidine. It is measured with the oral syringe that comes in the carton and taken once a day at bedtime. It can be used alone or with a stimulant, and it is not a controlled substance.
Do not stop suddenly: abrupt discontinuation of an alpha-2 agonist can cause rebound hypertension (labels describe headache, tachycardia, nausea, flushing and rapid rises in blood pressure; hypertensive encephalopathy has been reported with guanfacine). Taper as directed, and watch for missed doses during vomiting illnesses.
Clonidine HCl ER oral suspension 0.1 mg/mL (NDA 217645, Tris Pharma; approved May 24, 2024; DailyMed labeler NextWave Pharmaceuticals). Indicated for ADHD as monotherapy or adjunctive therapy to CNS stimulants in pediatric patients 6 years and older; efficacy is based on studies of clonidine ER tablets (ages 6–17). Once-daily bedtime dosing; steady-state AUC ~98% and Cmax,ss ~108% of clonidine ER tablets 0.1 mg twice daily at the same total dose, with Cmin,ss ~26% lower. No boxed warning.
When considering this for a patient
Onyda XR suits children who need clonidine ER but cannot swallow tablets, or families who prefer a single bedtime dose instead of twice-daily tablets. Clinically it is used for the same reasons as clonidine ER tablets (prominent hyperactivity or impulsivity, stimulant intolerance, or add-on to a stimulant); those are practice reasons rather than label-studied subgroups.
Measure heart rate and blood pressure before starting, after dose increases, and periodically. Titrate slowly in patients at risk of hypotension, bradycardia, heart block or syncope. Missed doses during vomiting illnesses raise the risk of rebound hypertension.
Patient profile and niche
Onyda XR may be particularly useful in the following situations:
- Children 6 and older who cannot swallow tablets.
- Families who prefer one bedtime dose rather than morning and bedtime tablets.
- Children who need extra symptom control on top of a stimulant, or who cannot take stimulants.
- Preference for a non-controlled medicine.
Less suited when low blood pressure, slow heart rate or fainting are concerns, or when daytime sleepiness would be a problem.
When it is active
Onyda XR is taken once a day at bedtime. Each dose peaks about 7.5 hours later (range 4–17 hours), and clonidine’s half-life is about 12–16 hours, so levels stay present around the clock once steady state is reached, highest overnight and in the early morning. The label does not describe hour-by-hour effects; doses are raised weekly and the supporting trials (with clonidine ER tablets) measured benefit over weeks.
The chart shows the schematic steady-state blood level across 24 hours for your bedtime dose.
Enter your usual dose time and day. The curve shows the schematic blood level after several days of daily dosing (steady state), across a full 24 hours. It does not show when the medicine ‘works’: for this medicine, benefit is judged over weeks, not hour by hour.
The curve shows relative blood level, not clinical effect. Benefit is judged over weeks of daily dosing and titration.
Everyone is different. This is a schematic based on labeling data, not a prediction for any one person.
How it works
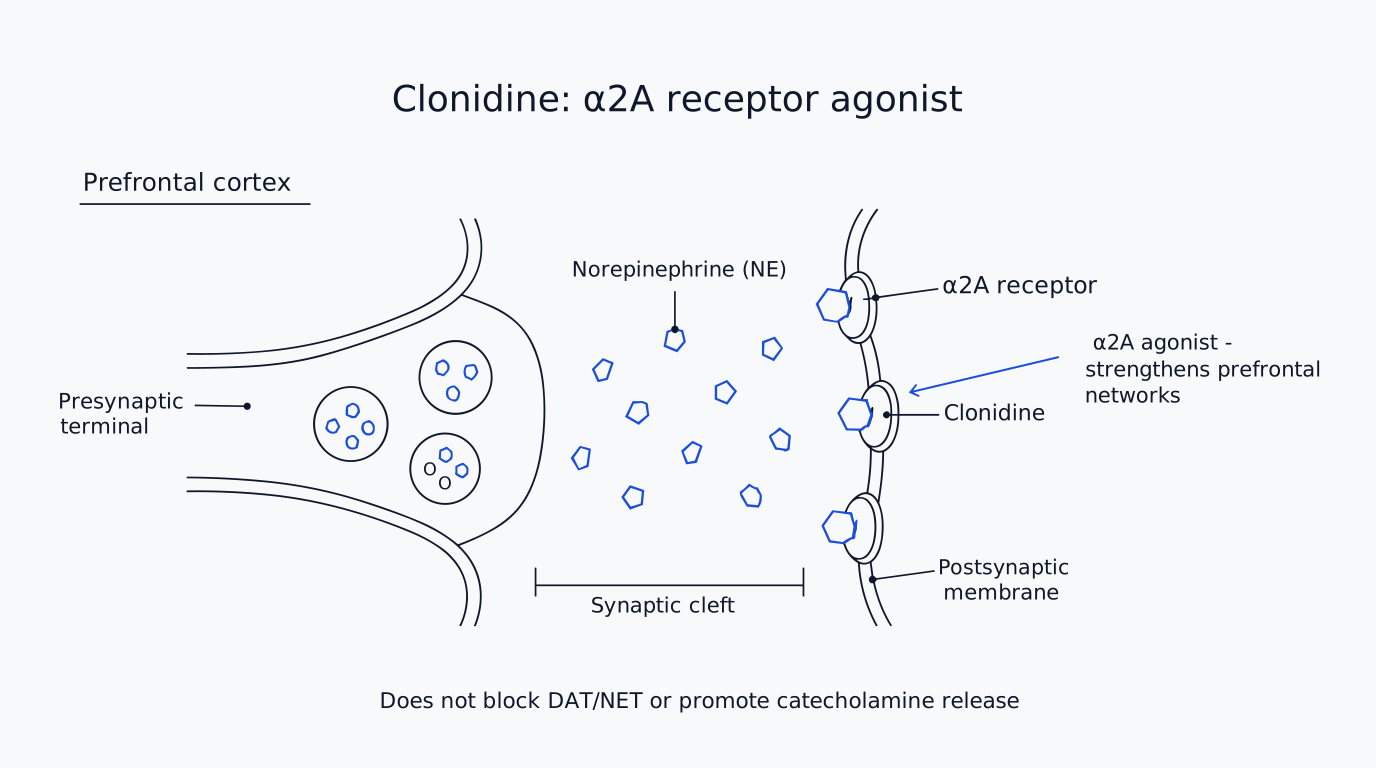
Clonidine stimulates alpha-2 receptors in the brain. It is not a stimulant and does not block dopamine or norepinephrine transporters. The same action lowers blood pressure and heart rate, which is why those are monitored.
Reduces sympathetic outflow
Per labeling, clonidine stimulates alpha-2-adrenergic receptors in the brain, is not a central nervous system stimulant, and its mechanism of action in ADHD is not known. By stimulating alpha-2 receptors in the brain stem it reduces sympathetic outflow, lowering blood pressure and heart rate. About 50% of an absorbed dose is metabolized in the liver; 40–60% is excreted unchanged in urine.
Formulations and duration
Light beige to tan, orange-flavored (per the inactive ingredients) extended-release oral suspension, 0.1 mg clonidine HCl per mL. Each carton contains a bottle, an oral dosing dispenser and a press-in bottle adapter.
| STRENGTH | 0.1 mg/mL extended-release oral suspension |
|---|---|
| APPROVED AGES | 6 years and older (monotherapy or adjunct to a CNS stimulant) |
| DOSING | Once daily at bedtime, with or without food |
| HANDLING | Gently shake up and down for at least 10 seconds before each dose; use only the supplied dispenser |
| STORAGE | Room temperature, protect from light; discard 30 days after opening (30 and 60 mL bottles) or 60 days (120 mL) |
| CONTROLLED STATUS | Not a controlled substance |
Missed dose: skip it and take the next dose as scheduled; do not exceed the prescribed total daily amount in 24 hours. Do not substitute for other clonidine products mg-for-mg.
Appearance
Onyda XR packaging (FDA label):
- 30 mL bottle with one oral dosing dispenser and one bottle adapter (NDC 24478-148-03)
- 60 mL bottle with one dispenser and one adapter (NDC 24478-148-04)
- 120 mL bottle with two dispensers and two adapters (NDC 24478-148-02)
The suspension is light beige to tan and viscous. Keep it in the original bottle.
Official package photos and pill identifiers:
Generic manufacturers
There is no generic clonidine extended-release oral suspension. Generic clonidine ER tablets exist but are not interchangeable mg-for-mg with Onyda XR.
| Product | Notes |
|---|---|
| Onyda XR (Tris Pharma) | NDA 217645; 0.1 mg/mL; reference standard; no TE-rated generic |
| Clonidine ER tablets | Different dosage form (twice daily); see the clonidine ER (Kapvay) page |
Orange Book (October 2026): Onyda XR RX, approved May 24, 2024; no generics.
Common side effects
Do not stop suddenly: abrupt discontinuation of an alpha-2 agonist can cause rebound hypertension (labels describe headache, tachycardia, nausea, flushing and rapid rises in blood pressure; hypertensive encephalopathy has been reported with guanfacine). Taper as directed, and watch for missed doses during vomiting illnesses.
Common side effects include sleepiness, tiredness, irritability, nightmares, trouble sleeping, constipation and dry mouth. When added to a stimulant, sleepiness, tiredness, decreased appetite and dizziness are most common.
| EFFECT | FREQUENCY | NOTES |
|---|---|---|
| Sleepiness / sedation | Common | Caution with driving; often most noticeable early |
| Tiredness | Common | |
| Irritability, nightmares, trouble sleeping | Common | Tell your clinician |
| Constipation, dry mouth | Common | Usually mild |
| Low blood pressure, slow heart rate, fainting | Uncommon | Monitored; avoid dehydration and overheating |
| Rebound high blood pressure if stopped suddenly | Serious | Always taper |
Safety is based on studies of clonidine ER tablets. Most common adverse reactions (≥5% and ≥2× placebo): monotherapy — somnolence, fatigue, irritability, nightmare, insomnia, constipation, dry mouth; adjunct to psychostimulant — somnolence, fatigue, decreased appetite, dizziness. Warnings: hypotension/bradycardia; somnolence/sedation; rebound hypertension (updated 04/2025); allergic reactions; cardiac conduction abnormalities. Avoid use with agents that affect sinus node function or AV conduction (digitalis, calcium channel blockers, beta-blockers); CNS depressants and alcohol add to sedation; tricyclic antidepressants may reduce the hypotensive effect. Contraindication: hypersensitivity to clonidine.
Beta-blockers and stopping clonidine: this label warns of additive bradycardia and AV block with drugs that slow heart rate or AV conduction, including beta-blockers (section 7 table: avoid use), and requires a taper of no more than 0.1 mg every 3–7 days (label 2.4). It does not address sequencing. Other clonidine labeling (Catapres-TTS and immediate-release clonidine tablets, Warnings: Withdrawal) notes that withdrawal reactions appear more likely with continued beta-blockade and advises, when both drugs are being stopped, withdrawing the beta-blocker several days before the gradual clonidine discontinuation.
Dosing considerations
Start with 0.1 mg (1 mL) once at bedtime. The dose can go up by 0.1 mg (1 mL) each week, to a maximum of 0.4 mg (4 mL) once at bedtime.
Doses above 0.4 mg once daily were not evaluated for ADHD and are not recommended. When Onyda XR is added to a CNS stimulant, adjust the stimulant dose based on response. Switching from another clonidine product: stop it and titrate Onyda XR from the start. Renal impairment: base the starting dose on the degree of impairment, monitor carefully, titrate cautiously; no supplemental dose after dialysis. Discontinuation: taper the total daily dose by no more than 0.1 mg every 3–7 days.
| Week | Bedtime dose | Volume (0.1 mg/mL) |
|---|---|---|
| Start | 0.1 mg | 1 mL |
| After 1 week (if needed) | 0.2 mg | 2 mL |
| After 2 weeks (if needed) | 0.3 mg | 3 mL |
| Maximum | 0.4 mg | 4 mL |
Increases are made at weekly intervals depending on clinical response; not every patient needs the maximum.
Pregnancy and breastfeeding
Tell your clinician if you are pregnant, plan to become pregnant, or are breastfeeding. Decades of clonidine use in pregnancy have not shown a higher risk of major birth defects or miscarriage.
Clonidine passes into breast milk. Most breastfed babies have had no problems, but one baby had sleepiness, floppy muscles, and pauses in breathing. If you breastfeed, watch the baby for sleepiness, unusual tiredness, fast breathing, or poor feeding, and decide together with your clinician.
A national pregnancy registry collects information about medicines used during pregnancy. You or your clinician can enroll by calling 1-866-961-2388.
Pregnancy (label 8.1, Onyda XR label): decades of published experience with clonidine in pregnancy (controlled trials, a retrospective cohort study, and case reports) have not identified a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. Animal data: increased resorptions in rats and mice at 10 and 5 times the adolescent MRHD (0.4 mg/day) and in rats dosed continuously from before mating at 1/3 of the MRHD; no developmental effects in rabbits at up to 3 times the MRHD. Registry: National Pregnancy Registry for Psychiatric Medications (as named in the label), 1-866-961-2388.
Lactation (label 8.2): clonidine is present in human milk at relative infant doses of 4.1% to 8.4% of the maternal weight-adjusted dose. Most exposed infants had no reported adverse effects, but there is one case report of sedation, hypotonia, and apnea. Monitor exposed infants for hypotension or bradycardia (sedation, lethargy, tachypnea, poor feeding), weigh the benefits of breastfeeding against the mother’s clinical need, and use caution when giving it to a nursing woman.
Outside the label: LactMed (NCBI Bookshelf, “Clonidine,” revised Nov 2024; NBK501628) notes high blood levels in some breastfed infants, possible infant side effects, and possible negative effects on lactation, and (in the context of blood-pressure treatment) prefers other agents, especially while nursing a newborn or preterm infant. This is LactMed’s summary of published data, not FDA label content.
Availability and shortages
MARKETED Onyda XR is marketed by Tris Pharma (DailyMed labeler NextWave Pharmaceuticals) and is not on the FDA or ASHP shortage lists as of October 20, 2026. It is brand-only, so check insurance coverage.
Generic clonidine ER tablets are a twice-daily alternative; see the clonidine ER (Kapvay) page.
Checked Oct 20, 2026: FDA Drug Shortages database and ASHP current shortage list — no clonidine entries. Orange Book: Onyda XR RX.
How Onyda XR compares to other nonstimulant options
Rows summarize each product’s FDA labeling; they are not head-to-head comparisons. Unlike stimulants, atomoxetine, viloxazine, guanfacine and clonidine are not controlled substances and are taken every day for continuous coverage, with benefit judged over weeks of titration rather than hours after a dose.
| Medication | Class / action (label) | Dosing and time course | Controlled status / boxed warning | Key safety and practical notes |
|---|---|---|---|---|
| Onyda XR (clonidine ER oral suspension) | Centrally acting α2-adrenergic agonist | Once daily at bedtime; +0.1 mg/week; max 0.4 mg | Not controlled · No boxed warning | Rebound hypertension if stopped abruptly (taper ≤0.1 mg every 3–7 days). Liquid 0.1 mg/mL; not mg-for-mg with other clonidine. Ages 6+. |
| Clonidine ER tablets (Kapvay discontinued) | Centrally acting α2-adrenergic agonist | Twice daily (equal or larger bedtime dose); +0.1 mg/week; max 0.4 mg/day | Not controlled · No boxed warning | Rebound hypertension if stopped abruptly (taper ≤0.1 mg every 3–7 days). Ages 6–17. Kapvay brand discontinued; AB1 generics. |
| Intuniv (guanfacine ER tablet) | Central α2A-adrenergic agonist | Once daily (AM or PM); +1 mg/week max; trials up to 15 weeks | Not controlled · No boxed warning | Rebound hypertension if stopped abruptly (taper ≤1 mg every 3–7 days). CYP3A4 dose adjustments. Ages 6–17 studied. AB generics. |
| Atomoxetine (Strattera; generics; Atoncy solution) | Selective norepinephrine reuptake inhibitor | Once daily or split twice daily; titrate after ≥3 days; acute trials up to 18 weeks | Not controlled · Boxed warning: suicidal thoughts (ages 6+) | CYP2D6 poor metabolizers/strong 2D6 inhibitors: 4-week titration interval; label states start, target and maximum unchanged. Liver injury warning. Brand discontinued; AB generics. |
| Qelbree (viloxazine ER capsule) | Selective norepinephrine reuptake inhibitor (also 5-HT2C partial agonist) | Once daily; weekly titration; steady state in 2 days; trials 6–8 weeks | Not controlled · Boxed warning: suicidal thoughts (all ages) | Strong CYP1A2 inhibitor: contraindicated with sensitive/narrow-range CYP1A2 substrates. Sprinkle allowed. Brand only. |
| Simtriyo (centanafadine ER capsule) | Norepinephrine-dopamine-serotonin reuptake inhibitor; labeled a CNS stimulant | Once daily in the morning; fixed weight-/age-based doses; trials 6 weeks | Schedule III (CIII) · Boxed warnings: pediatric suicidality; abuse/misuse | Approved Jul 24, 2026; DEA Schedule III since Oct 30, 2026; now marketable (check pharmacy availability). Moderate CYP1A2 inhibitor. Ages 6+ and ≥20 kg. |
| Stimulants for contrast (e.g. Concerta, Vyvanse) | Methylphenidate or amphetamine: block (and for amphetamines, release) dopamine and norepinephrine | Effects begin within hours of each dose and wear off the same day (timing depends on formulation; see each label) | Schedule II · Boxed warning: abuse, misuse and addiction | Coverage is tied to dosing time each day, unlike the continuous steady-state coverage of atomoxetine, viloxazine and the alpha-2 agonists. |
Other nonstimulant and newer-mechanism pages: Strattera (atomoxetine), Atoncy (atomoxetine solution), Qelbree, Intuniv, Kapvay (clonidine ER), Simtriyo. Stimulant overviews: methylphenidate (Ritalin) and amphetamine (Adderall) family pages.
Clinical evidence from published studies
These findings come from published research, not from the FDA label. The FDA label is the official source for approved uses, doses and warnings. Results from studies may not apply to you. Uses marked off-label are not FDA-approved. Talk with your prescriber before making any change.
Items summarize peer-reviewed publications, checked against the PubMed abstract (or full text where stated); figures are reproduced only where the source states them. The FDA label governs approved indications and dosing. Off-label items are not FDA-approved uses. Industry funding or sponsor affiliation is noted where the PubMed record shows it; absence of a note does not mean no industry involvement.
Studies of this medicine (6 studies)
-
Clonidine ER (Kapvay) monotherapy, 6–17
In 236 children and teens, clonidine extended-release tablets at 0.2 or 0.4 mg/day reduced ADHD symptoms more than placebo, starting as early as week 2. Sleepiness was the most common side effect. These trials studied Kapvay, a twice-daily extended-release tablet.
This trial studied Kapvay (twice-daily clonidine ER tablets), not Onyda XR (once-daily bedtime oral suspension).
RCT, N=236 (placebo 78; 0.2 mg 78; 0.4 mg 80): ADHD-RS-IV improvement significant at week 5 and from week 2. Somnolence most common TEAE; minor ECG changes.
Jain R, Segal S, Kollins SH, et al. (2011). Clonidine extended-release tablets for pediatric patients with attention-deficit/hyperactivity disorder. J Am Acad Child Adolesc Psychiatry 50(2):171-9. DOI · PubMed 21241954
-
Clonidine ER (Kapvay) added to a stimulant
In 198 children and teens with a partial response to a stimulant, adding clonidine extended-release tablets reduced ADHD symptoms more than adding placebo. This trial studied Kapvay, a twice-daily extended-release tablet.
This trial studied Kapvay (twice-daily clonidine ER tablets), not Onyda XR (once-daily bedtime oral suspension).
Adjunctive RCT, 198 randomized (102 CLON-XR, 96 placebo): ADHD-RS-IV difference 95% CI −7.83 to −1.13 (P=.009) at week 5.
Kollins SH, Jain R, Brams M, et al. (2011). Clonidine extended-release tablets as add-on therapy to psychostimulants in children and adolescents with ADHD. Pediatrics 127(6):e1406-13. DOI · PubMed 21555501
-
Once-daily clonidine ER tablets (a different product, studied in China)
In a 6-week Chinese trial (75 children and teens, assigned 2:1), once-daily clonidine extended-release tablets (target 0.2 mg/day) reduced ADHD symptoms more than placebo. This was a different product (a tablet), not Onyda XR (an oral suspension).
Phase 3 RCT, n=75 (6–17 y), 2:1, once-daily CLON-XR target 0.2 mg/day: SNAP-IV −17.5 vs −10.3 (p=0.0039). TEAEs comparable to placebo; dropout 5.3%.
Qian Y, Ke X, Gao F, et al. (2026). Efficacy and Safety of Extended-Release Clonidine Hydrochloride for Attention Deficit Hyperactivity Disorder in Chinese Children and Adolescents: A Multicenter, Randomized, Double-Blind, Placebo-Controlled Trial. J Child Adolesc Psychopharmacol 36(5):278-286. DOI · PubMed 41944053
-
Alpha-2 agonists (clonidine IR/ER, guanfacine ER), youth
A meta-analysis of 12 trials (2,276 youth) found clonidine and guanfacine reduced ADHD symptoms more than placebo, alone or added to a stimulant (smaller effect when added). Tiredness, sedation and sleepiness were more common, and clonidine lowered blood pressure and heart rate.
This review pooled immediate-release and extended-release clonidine with guanfacine; it did not study this product alone.
SR/MA (to May 2013): 12 RCTs, N=2,276. Monotherapy (9 studies, n=1,550): overall ADHD SMD −0.59, hyperactivity/impulsivity −0.56, inattention −0.57, ODD −0.44. Add-on (3 studies, n=726): SMD −0.36. Monotherapy all-cause discontinuation RR 0.70 (NNT 10); fatigue NNH 10, sedation NNH 17, somnolence NNH 4; hypotensive and bradycardic effects with clonidine-IR, QTc prolongation with guanfacine-XR; add-on: hypotension/bradycardia with clonidine-XR and guanfacine-XR.
Hirota T, Schwartz S, Correll CU (2014). Alpha-2 agonists for attention-deficit/hyperactivity disorder in youth: a systematic review and meta-analysis of monotherapy and add-on trials to stimulant therapy. J Am Acad Child Adolesc Psychiatry 53(2):153-73. DOI · PubMed 24472251
-
Clonidine (mostly immediate-release), children and teens
An early meta-analysis of 11 studies found a moderate effect of clonidine on ADHD symptoms, smaller than stimulants, with many side effects. Most included studies used immediate-release clonidine.
This study used immediate-release clonidine taken in divided doses, not Onyda XR (once-daily bedtime clonidine ER suspension).
Meta-analysis (literature 1980–1999: 39 studies, 11 with sufficient data). Weighted effect size 0.58 ± 0.16 (95% CI 0.27–0.89) in children and adolescents with ADHD alone or with conduct disorder, developmental delay or tics. Authors: possible second-tier treatment, effect size below stimulants, many side effects. Pre-dates clonidine ER.
Connor DF, Fletcher KE, Swanson JM (1999). A meta-analysis of clonidine for symptoms of attention-deficit hyperactivity disorder. J Am Acad Child Adolesc Psychiatry 38(12):1551-9. DOI · PubMed 10596256
-
Clonidine (immediate-release) alone or with methylphenidate, children 7–12
In a 16-week trial in 122 children, clonidine did not improve teacher-rated ADHD symptoms, while methylphenidate did. Clonidine did improve parent ratings and overall functioning but caused more sedation. The authors judged methylphenidate the best balance of benefit and tolerability.
This study used immediate-release clonidine taken in divided doses, not Onyda XR (once-daily bedtime clonidine ER suspension).
Randomized, double-blind, placebo-controlled 2×2 factorial (clonidine, MPH, combination, placebo), 16 weeks, n=122, ages 7–12, divided dosing (IR clonidine). Primary (Conners Teacher ASQ): no clonidine effect; MPH significant. Clonidine improved Conners Parent ASQ and CGAS, with more sedation.
Palumbo DR, Sallee FR, Pelham WE Jr, et al. (2008). Clonidine for attention-deficit/hyperactivity disorder: I. Efficacy and tolerability outcomes. J Am Acad Child Adolesc Psychiatry 47(2):180-188. DOI · PubMed 18182963
How ADHD medicines compare (2 studies)
-
ADHD medicines (class)
A large analysis of 133 short-term trials found that every ADHD medicine studied worked better than placebo on clinician ratings in children and teens. Amphetamines had the largest average effect, and methylphenidate was the only medicine also shown to beat placebo on teacher ratings. Amphetamines and guanfacine led to more stopping for side effects than placebo in children. Weighing benefit and side effects, the authors favored methylphenidate first in children and amphetamines first in adults. There was too little data to judge effects beyond about 12 weeks.
Network meta-analysis of 133 double-blind RCTs (efficacy near 12 wk: 10,068 children/adolescents; 8,131 adults). Children, clinician-rated SMD vs placebo: amphetamines −1.02 (95% CI −1.19 to −0.85), methylphenidate −0.78 (−0.93 to −0.62), atomoxetine −0.56 (−0.66 to −0.45). Teacher-rated: only methylphenidate (−0.82, −1.16 to −0.48) and modafinil separated from placebo. Adults, clinician-rated: amphetamines −0.79 (−0.99 to −0.58), methylphenidate −0.49 (−0.64 to −0.35), atomoxetine −0.45 (−0.58 to −0.32). Discontinuation for adverse events vs placebo: amphetamines OR 2.30 (1.36–3.89) in children and 3.26 (1.54–6.92) in adults; guanfacine 2.64 (1.20–5.81) in children; atomoxetine 2.33 (1.28–4.25) and methylphenidate 2.39 (1.40–4.08) in adults only. Head-to-head clinician-rated efficacy favored amphetamines over methylphenidate, atomoxetine and modafinil. Insufficient data at 26 and 52 weeks.
Funding / affiliation: Non-industry (Stichting Eunethydis; UK NIHR Oxford Health BRC).
Cortese S, Adamo N, Del Giovane C, et al. (2018). Comparative efficacy and tolerability of medications for attention-deficit hyperactivity disorder in children, adolescents, and adults: a systematic review and network meta-analysis. Lancet Psychiatry 5(9):727-738. DOI · PubMed 30097390
-
ADHD treatments in children and teens (class)
Across 190 trials in children and teens, methylphenidate, amphetamine, atomoxetine, guanfacine and clonidine all worked better than placebo. Methylphenidate and amphetamine appeared more effective than atomoxetine and guanfacine. Behavioral therapy combined with a stimulant appeared better than either medicine type alone. Most effective medicines also caused harms such as reduced appetite, weight loss and sleep problems.
Bayesian network meta-analyses of 190 RCTs (52 interventions, 26,114 participants; ≥3 weeks follow-up). Medications more efficacious than placebo: methylphenidate, amphetamine, atomoxetine, guanfacine, clonidine. Methylphenidate and amphetamine more efficacious than atomoxetine and guanfacine; methylphenidate and clonidine better accepted (all-cause discontinuation) than placebo and atomoxetine. Behavioural therapy plus stimulants appeared superior to stimulants or nonstimulants alone. Harms included anorexia, weight loss and insomnia. Results expressed as ORs with credible intervals (not reproduced here).
Catalá-López F, Hutton B, Núñez-Beltrán A, et al. (2017). The pharmacological and non-pharmacological treatment of attention deficit hyperactivity disorder in children and adolescents: A systematic review with network meta-analyses of randomised trials. PLoS One 12(7):e0180355. DOI · PubMed 28700715
Heart and blood pressure (2 studies)
-
ADHD medicines (class)
Pooling 102 short-term trials, most ADHD medicines raised blood pressure and pulse modestly, and stimulants did not raise them more than atomoxetine or viloxazine. Guanfacine lowered blood pressure and pulse. The authors advise monitoring blood pressure and pulse with any ADHD medicine, not just stimulants.
NMA of 102 RCTs (13,315 children/adolescents; 9,387 adults; median 7 weeks). Children, mean increase vs placebo: SBP 1.07 (atomoxetine) to 1.81 mm Hg (methylphenidate); DBP 1.93 (amphetamines) to 2.42 (methylphenidate); pulse 2.79 bpm (viloxazine) to 5.58 bpm (atomoxetine). Amphetamines, lisdexamfetamine and methylphenidate not associated with larger increments than atomoxetine or viloxazine. Guanfacine in children: SBP −2.83 (−3.8 to −1.85), DBP −2.08, pulse −4.06. Only four RCTs informed medium-term effects. CINeMA confidence mostly low to moderate in children, very low in adults.
Funding / affiliation: Non-industry (UK NIHR).
Farhat LC, Lannes A, Del Giovane C, et al. (2025). Comparative cardiovascular safety of medications for attention-deficit hyperactivity disorder in children, adolescents, and adults: a systematic review and network meta-analysis. Lancet Psychiatry 12(5):355-365. DOI · PubMed 40203844
-
Clonidine (immediate-release) alone or with methylphenidate, children
In the same 16-week trial, slow heart rate occurred more often with clonidine (18% vs 3%), but there were no other differences in ECG or heart outcomes and no sign that clonidine and methylphenidate together were worse for the heart. Drowsiness was common at first and usually faded by 6 to 8 weeks.
This study used immediate-release clonidine taken in divided doses, not Onyda XR (once-daily bedtime clonidine ER suspension).
Safety report of the CAT trial: clonidine (n=31), MPH (n=29), combination (n=32), placebo (n=30); clonidine up to 0.6 mg/day, MPH up to 60 mg/day, divided doses. Bradycardia 17.5% vs 3.4% (p=.02); no other ECG/cardiovascular group differences; no clonidine–MPH interaction. Moderate/severe AEs 79.4% vs 49.2% (p=.0006) without more early withdrawal. Drowsiness generally resolved by 6–8 weeks.
Daviss WB, Patel NC, Robb AS, et al. (2008). Clonidine for attention-deficit/hyperactivity disorder: II. ECG changes and adverse events analysis. J Am Acad Child Adolesc Psychiatry 47(2):189-198. DOI · PubMed 18182964
ADHD with other conditions (2 studies)
-
ADHD with tic disorders
In children with ADHD and tics (9 trials), methylphenidate, alpha-2 agonists (clonidine, guanfacine) and atomoxetine improved ADHD symptoms. Alpha-2 agonists and atomoxetine also reduced tics, and methylphenidate did not worsen tics in the short term. Very high doses of dextroamphetamine were linked to worse tics.
Meta-analysis, 9 studies, 477 subjects. ADHD efficacy: MPH, α2 agonists, desipramine, ATX. Tic improvement: α2 agonists and ATX. No evidence MPH worsened tics short-term; supratherapeutic dextroamphetamine worsened tics. Authors: MPH gave the greatest and most immediate ADHD improvement.
Bloch MH, Panza KE, Landeros-Weisenberger A, et al. (2009). Meta-analysis: treatment of attention-deficit/hyperactivity disorder in children with comorbid tic disorders. J Am Acad Child Adolesc Psychiatry 48(9):884-893. DOI · PubMed 19625978
-
Clonidine (immediate-release) and/or methylphenidate, children with ADHD and tics
In a 16-week trial in 136 children with ADHD and a chronic tic disorder, clonidine and methylphenidate each improved teacher-rated ADHD symptoms, and the combination helped most. Tics did not worsen more often with methylphenidate than with placebo. Moderate or severe sedation was common with clonidine.
This study used immediate-release clonidine taken in divided doses, not Onyda XR (once-daily bedtime clonidine ER suspension).
Multicenter randomized double-blind 2×2 factorial (clonidine, MPH, combination, placebo), n=136, 16 weeks. Conners ASQ-Teacher: clonidine p<0.002, MPH p<0.003, combination vs placebo p<0.0001. Tic worsening reported: MPH 20%, clonidine 26%, placebo 22%; tic severity lessened in all active groups. Moderate/severe sedation 28% with clonidine; no evident cardiac toxicity.
Tourette's Syndrome Study Group (2002). Treatment of ADHD in children with tics: a randomized controlled trial. Neurology 58(4):527-36. DOI · PubMed 11865128
Frequently asked questions
What is Onyda XR?
An extended-release liquid form of clonidine (0.1 mg per mL) taken once a day at bedtime for ADHD in children 6 and older.
Is Onyda XR a stimulant?
No. Clonidine is a centrally acting alpha-2 adrenergic agonist and is not a controlled substance.
How do I give Onyda XR?
Gently shake the bottle up and down for at least 10 seconds, then measure the dose with the oral dispenser that comes in the carton. Give it at bedtime, with or without food.
Is there a generic version of Onyda XR?
No. There is no generic clonidine extended-release oral suspension. Generic clonidine ER tablets exist but are not interchangeable mg-for-mg with Onyda XR.
How long is an opened bottle good for?
Discard unused medicine 30 days after first opening for 30 mL and 60 mL bottles, or 60 days for the 120 mL bottle.
Is it safe to stop Onyda XR suddenly?
No. Stopping suddenly can cause rebound high blood pressure. The label recommends lowering the dose by no more than 0.1 mg every 3–7 days. If you also take a beta-blocker (a heart or blood pressure medicine such as propranolol) and both are being stopped, ask your prescriber about the order: other clonidine labeling advises stopping the beta-blocker several days before clonidine is slowly lowered.
Can I switch from clonidine tablets to Onyda XR at the same dose?
No. Onyda XR is not interchangeable milligram for milligram with other clonidine products. The old product is stopped and Onyda XR is started at 0.1 mg and titrated.
Can Onyda XR be used with a stimulant?
Yes. It is approved alone or as an add-on to CNS stimulant medicines.
What if a dose is missed?
Skip it and give the next dose at the usual time. Do not double up. Repeated missed doses (for example during vomiting) can raise the risk of rebound high blood pressure.
How is it different from clonidine ER tablets?
Same medicine, different form: Onyda XR is a once-nightly liquid, while clonidine ER tablets are taken twice a day. At the same total dose, overall exposure is similar but the lowest level of the day is about 26% lower with Onyda XR.
Is Onyda XR the same as the clonidine patch?
No. The clonidine skin patch (Catapres-TTS) is a different product, and the Onyda XR label says not to substitute it for other clonidine products milligram for milligram. The patch labeling says to remove the patch before an MRI; that instruction is about the patch, not Onyda XR liquid.
Does Onyda XR work all day?
Onyda XR is taken once a day at bedtime (label section 2.1). The label does not describe hour-by-hour effects; each dose peaks about 7.5 hours later, and clonidine stays in the blood around the clock once it reaches a steady level (label section 12.3). Its support comes from trials of clonidine ER tablets that measured benefit over weeks.
How quickly does Onyda XR start working?
The label does not say how soon Onyda XR starts working. Doses are raised by 0.1 mg at weekly intervals depending on response (label section 2.1), and the supporting clonidine ER trials measured benefit over several weeks.
Can Onyda XR be taken with food?
Yes. Take it at bedtime with or without food (label section 2.1); food had no effect on blood levels (label section 12.3).
What are the most common side effects of Onyda XR?
When used alone, the Medication Guide lists sleepiness and tiredness (which can slow reaction times), nightmares, constipation, irritability, trouble sleeping and dry mouth. When used with other ADHD medicines, it lists sleepiness and tiredness, decreased appetite and dizziness (label section 6.1). These are not all the possible side effects; call your prescriber for advice about side effects that bother you.
Can I take Onyda XR while pregnant or breastfeeding?
Tell your clinician if you are pregnant or planning a pregnancy. The label says decades of clonidine use in pregnancy have not shown a higher risk of major birth defects or miscarriage. Clonidine passes into breast milk, and one breastfed baby had sleepiness, floppy muscles, and pauses in breathing, so watch the baby closely and decide together with your clinician. A pregnancy registry can be reached at 1-866-961-2388.
Prescribing guidelines
Guidelines generally place stimulants first for most school-age children, adolescents and adults when medication is indicated, with atomoxetine, extended-release guanfacine and extended-release clonidine as evidence-based alternatives or (for the alpha-2 agonists) add-on options. Viloxazine and centanafadine were approved after the 2019 AAP guideline, so it does not address them.
Resources
Sources
- Tris Pharma, Inc. (labeler NextWave Pharmaceuticals). Onyda XR (clonidine hydrochloride) extended-release oral suspension. Prescribing Information, revised 04/2025. DailyMed (accessed Oct 2026).
- Ajanta Pharma USA Inc. Clonidine hydrochloride extended-release tablets. Prescribing Information, revised 10/2025. DailyMed (accessed Oct 2026).
- U.S. Food and Drug Administration. Approved Drug Products with Therapeutic Equivalence Evaluations (Orange Book), data files dated October 2026. FDA.
- U.S. Food and Drug Administration. Drug Shortages database, accessed Oct 20, 2026 (no current-shortage entries for atomoxetine, viloxazine, guanfacine, clonidine or centanafadine; guanfacine ER tablets appear only on the discontinuation list). FDA.
- American Society of Health-System Pharmacists. Current Drug Shortage Bulletins list, accessed Oct 20, 2026 (no atomoxetine, viloxazine, guanfacine, clonidine or centanafadine entries). ASHP.
- Wolraich ML, Hagan JF Jr, Allan C, et al.; American Academy of Pediatrics Subcommittee on Children and Adolescents with ADHD. Clinical Practice Guideline for the Diagnosis, Evaluation, and Treatment of Attention-Deficit/Hyperactivity Disorder in Children and Adolescents. Pediatrics. 2019;144(4):e20192528. AAP.
- Centers for Disease Control and Prevention. Clinical Care of ADHD in Children (summary of the AAP guideline; updated Oct 21, 2026). CDC (accessed 2026).
- Drugs and Lactation Database (LactMed). Clonidine. National Institute of Child Health and Human Development; revised Nov 2024. NCBI Bookshelf NBK501628.
- Technomed Inc. Catapres-TTS (clonidine transdermal system) Prescribing Information, revised 03/2023 (Warnings: Withdrawal; Precautions: MRI). DailyMed (accessed Oct 2026).
- Actavis Pharma, Inc. Clonidine hydrochloride tablets, USP, Prescribing Information (Warnings: Withdrawal). DailyMed (accessed Oct 2026).